In the management of _______, the most appropriate initial step for a patient with acute pain and a history of high alcohol intake and a purine-rich diet is to _______.
Gout presents with acute, monoarticular pain, often in the _______ joint, due to the precipitation of _______.
The leukocyte count in synovial fluid during an acute gout episode typically ranges from _______ to _______.
In patients with gout, chronic preventive management should involve xanthine oxidase inhibitors like _______ after initial lifestyle modifications are made.
Colchicine is used for acute gout flares but is not appropriate for long-term management due to risks like _______ and _______.
Patients with gout should avoid high-purine foods and heavy _______ consumption as part of lifestyle changes.
Gout is an acute monoarticular arthropathy resulting from an inflammatory reaction to the precipitation of _______ crystals within the joint space.
Elevated levels of _______ can precipitate gout flares due to increased concentration in plasma volume.
Management for acute gout attacks should include _______, _______, or _______.
Patients should initiate lifestyle modifications, such as reduction of _______ and _______, even without acute symptoms.
Arthrocentesis in gout typically shows a leukocyte count of _______ with _______.
Chronic prevention of gout flares involves medications like _______ such as _______.
Adding a _______ to a patient with gout may increase the frequency of gout flares.
If a gout patient is asymptomatic and has utilized _______, watchful waiting may be appropriate.
In cases of _______, patients may have renal impairment characterized by proteinuria and the presence of _______ in the urine.
The presence of 4+ _______ and _______ in urine is typically associated with _______.
A patient with multiple myeloma often presents with symptoms including _______, kidney dysfunction, and _______.
Nephrotic syndrome in multiple myeloma causes _______ and significant _______ due to overproduction of immunoglobulin.
Patients with multiple myeloma may demonstrate kidney dysfunction due to _______ in the kidneys.
The typical urinary findings for nephrotic syndrome include _______ and the presence of _______.
For patients suspected of having a urinary tract infection, findings may include _______ and _______ in the urine, which is not typical for multiple myeloma.
The presence of _______ and renal tubular epithelial cells suggests acute tubular necrosis, not multiple myeloma.
The clinical presentation of acute kidney injury can include symptoms such as _______, _______, and _______. Such symptoms may indicate a hypersensitivity reaction, particularly to _______.
The presence of _______ and _______ on urinalysis suggests bleeding from the _______, indicating a nephrogenic source, such as _______.
Nephritic syndrome is usually characterized by <3 g/day of urinary protein along with _______. Patients may exhibit signs indicating conditions such as _______ or _______.
In cases of _______, urinalysis typically reveals _______, leading to red or brown urine without the presence of _______.
Common causes of _______ include crush injuries, excessive exertion, and the use of _______ or _______.
Dysmorphic RBCs and mild proteinuria may indicate either _______ or a _______, which can lead to symptoms like _______ and _______.
Multiple myeloma can present with bone pain, kidney dysfunction, and _______, potentially leading to _______ characterized by _______ and _______.
The clinical trial described is primarily designed to assess the _______ of a new drug-eluting coronary artery stent for patients with acute myocardial infarction who are not surgical candidates.
In phase 1 clinical trials, patients with _______ for chronic anticoagulation present ethical dilemmas when seeking treatment options.
Phase 1 clinical trials typically involve a small number of subjects to detect common or _______, but are not powered to detect rare adverse events.
Effectiveness is assessed in _______ clinical trials, which evaluate treatment effects in a general patient population under real-world conditions.
Comparability in drugs refers to their ability to perform _______ when produced under different conditions, especially after manufacturing changes.
Efficacy is typically assessed in _______ clinical trials, where the treatment is tested in hundreds of participants to determine how well it works.
Phase 1 clinical trials are primarily designed to assess the _______ of a treatment and involve _______ of subjects.
Phase 1 trials are not powered to detect rare _______ of treatment due to the small number of participants involved.
Rare adverse effects can typically be detected during phase 2 and phase 3 trials which enroll hundreds of _______.
The benefits of phase 1 trials will primarily accrue to _______ broadly, rather than the individual _______.
Care must be taken to safeguard the _______ of trial _______ in phase 1 trials.
During phase 1 trials, the primary focus is on assessing treatment _______, not _______.
Educational Objective: Phase 1 trials follow prior preclinical _______ or _______ research.
The correct answer to detecting rare adverse effects in drug trials is after conducting a _______.
Phase 1 trials do not enroll enough participants to reliably detect _______.
The most appropriate next step in diagnosis for a patient with bilateral ankle pain and swelling, without signs of osteoarthritis, is the _______.
When evaluating for _______, joint aspiration with Gram stain and culture is warranted if the patient presents with fever and acute onset of symptoms.
In the diagnosis of rheumatoid arthritis, serology testing includes both serum rheumatoid factor and _______.
MRI of the ankles is appropriate for evaluating soft tissue structures but is not the first step in a chronic ankle pain case if there is no _______ history.
Patients with rheumatoid arthritis may present with symptoms such as _______, swelling, and lack of degenerative changes on x-ray.
The presence of more than _______ with infectious agents on joint aspiration would indicate septic arthritis rather than rheumatoid arthritis.
In cases of suspected _______, venous duplex ultrasonography is a reasonable next step. Symptoms of DVT include lower extremity swelling in the affected limb and possible calf pain on _______.
Rheumatoid arthritis is an _______ that causes inflammation in synovial tissues, leading to bilateral joint involvement with synovial hypertrophy. It can also present with _______.
Common manifestations of rheumatoid arthritis include _______, _______, and _______.
For diagnosing rheumatoid arthritis, serology testing includes _______ which is sensitive, and _______ testing, which is specific for the disease.
When evaluating a patient for ankle pain and swelling, it is more likely they have _______ than _______.
In pregnant patients, diagnostic pivots must strongly consider the possibility of conditions such as _______ even with other signs and symptoms.
The best next step in a clinical scenario of a patient with suspected rheumatoid arthritis and joint pain is _______. 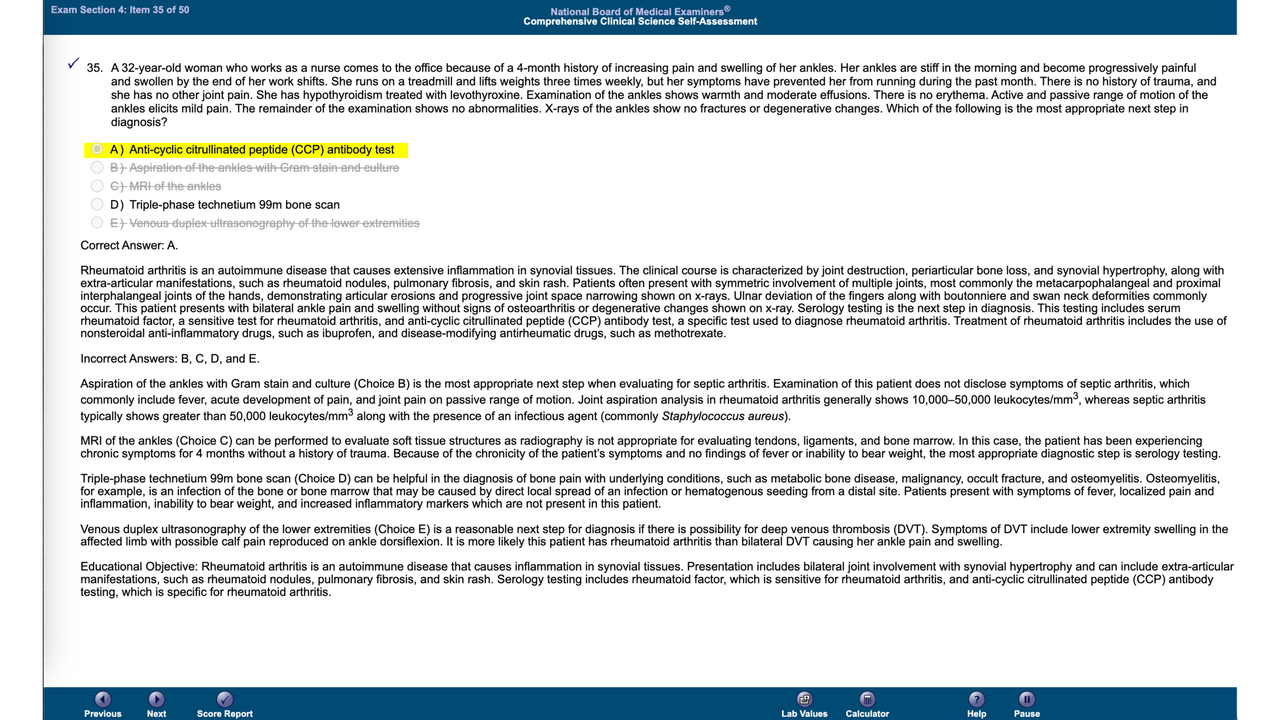
In a patient with increased cholesterol concentration, the most appropriate next step to assess potential hypothyroidism is the measurement of serum _______ concentration.
Hypothyroidism may cause vague symptoms like _______ and unexplained fatigue. It is characterized by low levels of thyroid hormones leading to increased _______.
The mechanism by which hypothyroidism increases serum cholesterol is through decreased activity of _______, affecting cholesterol synthesis and absorption.
In patients with primary hypothyroidism, increased serum _______ and _______ concentrations are typically observed due to feedback from low thyroid hormone levels.
A common presentation of hypothyroidism includes symptoms such as _______, _______, and _______.
When evaluating hypercholesterolemia, it is incorrect to measure serum _______ concentration as it is not a standard test for this condition.
In hypothyroidism, low thyroid hormone levels lead to decreased production of _______ in the liver, increasing serum cholesterol levels.
In the workup of _______, measuring serum follicle-stimulating hormone concentration (FSH) is _______.
Homocystinuria, characterized by increased _______ levels, is associated with symptoms like intellectual disability and lens _______.
Primary biliary cirrhosis (PBC) may present with _______, _______, and hypercholesterolemia.
Hypothyroidism presents with symptoms such as _______, weight gain, and _______.
In hypothyroidism, hypercholesterolemia occurs due to ⬇️ endogenous cholesterol synthesis and decreased _______ production.
The treatment for hypothyroidism includes _______ supplementation and monitoring of serum TSH concentration.
To diagnose _______, an abnormal serum mitochondrial antibody assay is relevant.
In the case of a 2-year-old boy with apnea after surgery, the best next step to prevent recurrence of such an opioid overdose is to conduct a _______ (RCA). RCA identifies core systems-level issues that lead to adverse events.
The multidisciplinary team in an RCA conducts analysis using tools like creating a _______ and surveying controls that may have failed.
Educational interventions that target individual errors, such as reporting a nurse for a morphine overdose, are less effective because most adverse events stem from _______ rather than individual errors.
In root cause analysis, it's crucial to analyze the entire process rather than focus on individual components, which may include verifying the patient's _______ or confirming drug doses, as they often don't address the underlying system issues.
Analyzing opioid toxicity cases emphasizes the importance of systematic procedures over individual assessments, highlighting that lack of _______ can lead to adverse outcomes.
The most likely diagnosis for a 57-year-old man with a history of recurrent pneumonia, coughing up blood, and crackles at lung bases is _______.
In bronchiectasis, patients typically present with frequent cough and _______.
Recurrent necrotizing infections and chronic inflammation lead to _______ bronchi dilatation in bronchiectasis.
Bronchiectasis can be associated with chronic bronchial obstruction and _______.
A CT scan is used to _______ the diagnosis of bronchiectasis.
Management of bronchiectasis includes airway clearance techniques and _______ for acute exacerbations.
Mitral stenosis presents with a _______ over the left intercostal space, not a systolic murmur.
Sarcoidosis commonly presents with _______ and cough, especially in younger patients.
The correct management for the patient with bronchiectasis includes identifying and treating the underlying _______.
Patients with bronchiectasis often have a history of recurrent episodes of pneumonia in _______.
In patients with _______, CT scan of the chest is used for _______ confirmation.
Management of _______ includes airway clearance techniques such as chest physiotherapy and _______.
DDuring acute exacerbations of _______, antibiotics are prescribed to address the _______.
_______ and necrotizing infections may lead to impaired mucociliary clearance in patients with _______.
The most significant imaging finding associated with _______ can be visualized in a CT scan: _______.
For optimal management, recognizing underlying disorders contributing to _______ is crucial in developing a treatment plan.
In diagnosing _______, it’s important to consider conditions that result in impaired _______.
In an 8-year-old boy presenting with severe abdominal pain and fever, the clear clinical diagnosis of _______ indicates that the best next step is _______.
Appendicitis in children often results from obstruction of the appendix due to _______ or _______.
Acute appendicitis typically presents with abdominal pain starting periumbilically and later migrating to the _______.
In a patient diagnosed with appendicitis, the presence of _______ (predominantly neutrophilic) supports the diagnosis.
Measurement of serum _______ is nonspecific and does not confirm appendicitis even if elevated.
In equivocal cases of appendicitis, imaging like _______ or _______ may assist in diagnosis, but should not delay _______ if a clear clinical diagnosis is present.
When evaluating a child for appendicitis, symptoms such as _______ and localized tenderness in the right lower quadrant support a diagnosis requiring surgical intervention.
The clinical diagnosis related to bacterial proliferation in the appendix is called _______. This condition leads to leukocytosis with a predominantly _______ response.
In the treatment of acute appendicitis, the best next step is to administer intravenous _______ and perform an _______.
Bacterial proliferation in the appendix causes a predominantly _______ leukocytosis, which is a key diagnostic marker.
Operative intervention for acute appendicitis is typically performed using a _______ technique.
In a clinical scenario of appendicitis, leukocytosis due to bacterial proliferation is predominantly _______, which helps in diagnosis.
A previously healthy 8-year-old boy with abdominal pain may present with signs of _______.
Acute appendicitis treatment often necessitates the use of _______ prior to surgical intervention.
Acute appendicitis is characterized by bacterial proliferation within the _______ and _______ of the appendix.
In the case of a 47-year-old woman with an itchy rash, the best next step in management for her type I hypersensitivity reaction is _______.
Urticaria is caused by a type _______ hypersensitivity reaction resulting in the release of _______, which causes localized symptoms.
The symptoms of type I hypersensitivity include pruritus, edema, and _______.
In a patient with a known peanut allergy experiencing urticarial reactions, skin testing for peanut allergy is _______ as they already have a diagnosis.
First-generation H1 antihistamines, such as _______, can be used to treat symptoms of urticaria in type I hypersensitivity reactions.
After administering treatment for urticaria, clinicians may consider _______ for other allergens to identify triggers.
In urticaria management, the patient is more likely to benefit from avoidance of the offending allergen and administration of _______.
In the case of an urticarial rash due to a type I hypersensitivity reaction, the appropriate initial treatment is _______.
Systemic lupus erythematosus and rheumatoid arthritis are examples of _______.
Prednisone can be used with antihistamines, but alone is not a first-line treatment for _______.
A skin biopsy with immunofluorescence is typically reserved for a _______ of unexplained etiology.
Type I hypersensitivity reactions are caused by _______ inflammation.
The release of _______, prostaglandins, and leukotrienes is triggered by the cross-linking of IgE on basophils and mast cells.
Management of non-life threatening manifestations like urticaria involves the removal of the allergen and treatment with an _______.
The most likely diagnosis for a 7-year-old boy showing disruptive behavior in reading classes, with a family history of reading difficulties, is _______.
Dyslexia is characterized by a specific learning disability in _______ or reading difficulty, often caused by a _______ in phonologic processing.
Assessment of fluency, decoding, and comprehension is necessary for diagnosing _______.
Common risk factors for dyslexia include a family history of reading difficulty, _______, and neurodevelopmental conditions such as _______.
Treatment for dyslexia often involves _______ to improve literacy and reading comprehension.
In cases where a child acts out, it may be a response to frustration related to their _______ challenges, rather than _______ alone.
In a patient with _______, they typically display anger and defiance towards caretakers. However, in this case, the patient does not have problems at home.
Dyslexia is a learning disability characterized by difficulty in _______ or reading-related tasks due to a cognitive deficit in _______.
School-age patients with dyslexia often exhibit difficulties in classes involving _______, and they may _______ in response to frustration.
A common condition in school-age children that leads to behavioral issues is _______, which necessitates understanding and intervention.
When evaluating a child with learning difficulties, it is important to rule out _______ as a possible cause, especially if they act out in frustration.
The educational objective highlights that dyslexia is linked to a cognitive deficit in _______.
The image shows a case concerning a 7-year-old boy who exhibits behavior concerns at school possibly related to _______. 
The most likely cause of the patient's urinary leakage after her vaginal hysterectomy is a _______ resulting in a _______.
Vesicovaginal fistulas can occur as a consequence of _______, pelvic pathology, or _______.
In patients with vesicovaginal fistula, the main symptom is usually _______ from the vagina, often due to abdominal pressure.
The confirmatory test for a suspected vesicovaginal fistula involves infusing dyed sterile fluid into the bladder to check for _______ in the vagina.
Cystitis typically presents with symptoms like _______, which this patient does not exhibit.
Stress incontinence is characterized by urinary leakage with activities that increase _______, such as laughing or sneezing.
Unlike stress incontinence, this patient’s condition is not associated with increases in intra-abdominal pressure, emphasizing a _______ as the primary concern.
The condition characterized by painless urinary leakage from the bladder into the vagina, often leading to a pool of urine in the vaginal canal, can be indicative of _______.
In a clinical scenario where a patient presents with a loss of clear, yellow vaginal fluid while walking, the best next step in management is to consider _______.
When evaluating a female patient with urinary leakage, it's crucial to assess for _______ due to the anatomical proximity of the bladder and vagina.
In the case of a 42-year-old woman presenting with vaginal fluid leakage, the differential diagnosis should include potential _______.
For a 72-year-old woman with 80% stenosis of the right internal carotid artery, endarterectomy reduces the risk of stroke or death from _______ to _______ at 5 years. The absolute risk reduction (ARR) is _______.
The number needed to treat (NNT) for endarterectomy to prevent one stroke or death is calculated as _______. This is derived from the formula NNT = 1 / ARR, where ARR is _______.
Endarterectomy decreases the absolute risk for stroke or death by 50% is incorrect. This corresponds to _______.
The correct interpretation of endarterectomy effectiveness indicates that endarterectomy prevents _______ of strokes or deaths, which is not the same as the total effect.
When interpreting clinical trial results, it is critical to understand that the number of endarterectomies needed to prevent one stroke or death is _______ based on the observable ARR.
Relative risk (RR) is defined by the formula RR = _______ / _______. In this case, RR = _______.
In clinical decision-making for interventions, the number needed to treat (NNT) is defined as the number of individuals who need to receive an intervention to prevent one negative outcome, calculated by the inverse of the absolute risk reduction (ARR). If the ARR is _______}, then the NNT is _______.
For a clinical intervention with an ARR of _______}, the calculation for NNT follows this formula: NNT = _______.
When considering an asymptomatic 72-year-old woman with _______} stenosis of the right internal carotid artery, the NNT to prevent stroke or death is _______.
The formula for calculating NNT is given by NNT = _______; for an ARR of _______, NNT equals _______.
For a 17-year-old girl experiencing severe cramps starting 3 days before menses lasting 5 days, the most appropriate next step in management for _______ is _______.
Primary dysmenorrhea in patients often manifests as _______ that begins _______ the onset of menses.
In diagnosing primary dysmenorrhea, it is essential to rule out secondary causes such as _______ or _______.
Treatment for primary dysmenorrhea may include _______ and _______.
A CT scan is not the first step for diagnosing primary dysmenorrhea due to the lack of _______ suggested by ultrasonography.
Reassurance is inappropriate in cases of primary dysmenorrhea since symptoms can significantly impact a patient’s _______ and _______.
Laparoscopy is the gold standard used in the diagnosis of _______.
Endometriosis is caused by implantation of ectopic _______ outside of the uterine cavity.
The classic symptoms of endometriosis include _______, _______, and _______.
A pelvic examination may reveal tenderness of the uterine wall and possible _______ due to pelvic adhesions.
Primary dysmenorrhea is defined as pain that accompanies each menstrual cycle without any underlying _______.
The mechanism behind primary dysmenorrhea involves uterine vasoconstriction in response to increased _______ by the endometrium.
The main treatments for primary dysmenorrhea include nonsteroidal anti-inflammatory drugs and _______.
For persistent symptoms of primary dysmenorrhea, options include _______ or a _______.
If a patient has no symptoms outside of her menstrual period, the need for diagnostic _______ is unlikely.
In an elderly patient with progressive confusion, the best next step in diagnosis to screen for _______ is to perform a _______.
Common risk factors for _______ include anticoagulant use, advanced age, and _______.
Elderly patients with a history of minor trauma may present with _______ due to a _______.
The appearance of a _______ on a CT scan is typically a _______ abutting the internal surface of the skull.
The presence of _______ during an examination may indicate an upper motor neuron lesion such as that seen in _______.
A key difference between _______ and subdural hematoma is that stroke typically presents with _______ compared to the gradual progression seen in SDH.
In cases of suspected _______, clinical signs may evolve over time, leading to findings consistent with increased _______.
For an elderly patient with confusion and risk factors, performing a measurement of serum vitamin B12 is inappropriate, as it would not address the concern of _______.
While assessing an elderly patient with confusion, the presence of multiple _______ and _______ can indicate potential underlying injuries such as a subdural hematoma.
To confirm the presence of _______, a clinical diagnosis can often be made without the need for an _______.
In elderly patients, cerebral atrophy can lead to traction on bridging cortical veins, increasing the risk of _______ after minor trauma.
Patients on _______ therapy have an increased risk of developing subdural hematoma due to venous injury.
When evaluating a suspected _______, a _______ of the head is the first step in screening.
On imaging, a subdural hematoma appears as a _______ abutting the internal surface of the skull.
Patients presenting with confusion and neurologic deficits that are progressive rather than episodic likely have _______ rather than episodic epileptic activity.
The presence of acute or gradually progressive focal neurologic deficits and confusion can indicate a potential _______.
In a patient with _______ (pes planus) who exhibits no symptoms or history of trauma, no additional diagnostic studies are indicated. Which of the following would be the best next step? _______.
Flatfoot, also known as _______, can be congenital or acquired from various factors such as trauma or long-standing diabetes mellitus.
In cases of symptomatic _______, initial management includes the use of _______, _______, and _______.
Flexible flatfoot occurs when the loss of the medial longitudinal arch is apparent during _______, returning when the patient is _______.
Imaging studies in flatfoot are not routinely required unless there are symptoms or history of _______. If advanced imaging is necessary, _______ would be preferred over CT.
The most common site for osseous metastases evaluated with a radionuclide bone scan is the _______, not the _______.
In managing _______, the best first-line treatment is typically the use of _______.
For a patient with _______, considering _______ is essential when tailoring a comprehensive management plan.
In the presence of _______, the key diagnostic pivot is the evaluation of _______.
The management of patient activity should be tailored based on the severity of the condition, and modification is essential in cases of _______ or _______.
When prescribing _______, always ensure that patients are informed about the potential risk of _______.
In an elderly patient presenting with _______, immediate treatment with a high-dose corticosteroid such as _______ is essential to prevent irreversible vision loss.
Classic symptoms of _______ include fever, chills, weight loss, headache, and transient vision loss (amaurosis fugax) as well as jaw claudication.
When considering treatment in a patient suspected of having _______, the addition of _______ is primarily as an adjunct to corticosteroids, not as a monotherapy.
In the context of assessing a patient with '{}temporal arteritis_______', elevated inflammatory markers such as an ESR > _______ and possible thrombocytosis can be indicative.
For patients with _______, biopsy of the temporal artery showing _______ is necessary for definitive diagnosis.
In patients with temporal arteritis, immediate high-dose _______ treatment should occur once the diagnosis is suspected, and it does not generally compromise biopsy results if performed within _______.
Temporal arteritis is primarily driven by _______, local tissue macrophages, and _______.
A constellation of symptoms in temporal arteritis includes _______, _______, and _______.
Unlike some systemic vasculitides, _______ is not effective in treating temporal arteritis due to the underlying pathophysiology not being driven by high concentrations of circulating serum autoantibodies.
Carotid stenosis may lead to transient _______ in the setting of ocular ischemic syndrome (OIS).
In the case of carotid artery stenosis, vision loss can occur depending on the degree of _______ between the internal and external carotid vascular systems.
Temporal arteritis can present with symptoms such as _______ and jaw claudication, highlighting its systemic involvement.
The incorrect choice for treating carotid stenosis in the described scenario was _______.
The background inflammatory event in temporal arteritis occurs within the vascular _______.
In a case where a patient has a do-not-attempt resuscitation (DNAR) order and shows signs of _______, the most appropriate next step is to _______.
In patients with a DNAR order, CPR should not be attempted if they show evidence of _______ since it is likely to be _______.
Brain death is defined as the permanent loss of all _______ and is diagnosed through neurologic examination and an _______.
Cardiopulmonary resuscitation (CPR) can only be attempted for patients in cardiac arrest who do not have a _______ order and are not yet _______.
When a patient is categorized as brain dead, they will not respond to _______, and administering pain relief like morphine is _______.
In patients with _______, an ankle brachial index (ABI) less than 0.9 indicates _______.
Patients diagnosed with _______ should be started on an antiplatelet agent, such as _______, for secondary prevention of coronary artery disease.
An ABI of _______ in the presence of absent pedal pulses is consistent with _______.
Despite normal total cholesterol and LDL levels, patients with _______ still need _______ as part of their management plan.
The primary reason for an ankle brachial index (ABI) test in a patient is to assess for _______.
In the assessment of a patient with PVD, the absence of symptoms like pain paired with an _______ indicates that acute limb ischemia is unlikely.
When managing a patient with _______, lifestyle changes such as _______ are crucial.
In patients with _______, cilostazol is effective for symptomatic improvement by inhibiting platelet aggregation and causing _______.
If a patient with PVD is asymptomatic, it is _______ to start treatment with cilostazol or any antiplatelet agents.
Echocardiography can evaluate for a potential _______ source in acute arterial embolus cases presenting with acute limb ischemia, which includes symptoms like severe pain and _______.
An exercise stress test is used for assessing _______, typically presenting with symptoms like exertional chest pressure and _______. It is not recommended for asymptomatic patients.
Hydrochlorothiazide therapy is indicated in patients with _______ or uncontrolled hypertension, and is not necessary in patients whose hypertension is _______.
Metformin is used primarily to manage _______ and works by decreasing hepatic glucose production and improving _______.
In patients with an ABI less than 0.9 who are symptomatic, duplex _______ is useful to define the extent of PVD; however, it is unnecessary in _______ patients.
Patients with _______ often exhibit absent or diminished peripheral pulses and _______ with smooth skin.
All patients with PVD should be started on a _______ and an _______ for management.
The condition characterized by loss of the medial longitudinal arch and heel eversion is called _______ or _______.
In the absence of symptoms and trauma, no additional diagnostic studies are indicated for _______.
Flexible flatfoot occurs when the arch loss only happens during _______, returning when the foot is lifted.
Initial management for symptomatic _______ includes _______, _______, and _______.
Imaging studies like _______ or _______ are not routinely required for diagnosing _______ unless there is trauma or reported symptoms.
A _______ is generally used to evaluate for osteoblastic osseous metastases but is not indicated for _______.
Patients with _______ may be asymptomatic but their condition can alter biomechanics and potentially lead to pain.
In adults, dysfunction of the _______ is often implicated in cases of acquired _______.
In the management of _______, nonsteroidal anti-inflammatory drugs (NSAIDs) are commonly used to alleviate pain during acute attacks.
The best next step for a patient with acute pain and swelling in the big toe is to start _______.
For managing chronic gout, _______ is recommended to reduce flare-ups.
In addition to pharmacotherapy, patients with gout should consider _______ and dietary adjustments to limit triggers.
In the case of an 80-year-old woman with symptoms of _______, the most appropriate next step in management is immediate treatment with _______ to preserve vision.
Symptoms such as transient monocular vision loss, headache, and fatigue in an elderly patient raise suspicion for _______.
The classic symptoms of _______ may include fever, chills, weight loss, jaw claudication, and headaches, as well as _______.
In cases of _______, there is a risk of irreversible vision loss due to _______ from occlusion of the ophthalmic artery.
Laboratory findings in patients with _______ often include increased inflammatory markers such as _______ and _______.
When diagnosing _______, a biopsy of the temporal artery is performed to confirm the presence of _______.
Despite vascular stenosis in an elderly patient, the presence of symptoms such as headaches and proximal extremity weaknesses may indicate the need for quick treatment of _______ with _______ rather than complications of stenosis alone.
For patients diagnosed with _______, immediate high-dose corticosteroid treatment should occur once the diagnosis is suspected.
_______ may lead to transient monocular vision loss in the setting of ocular ischemic syndrome (OIS).
Plasmapheresis is _______ in the treatment of temporal arteritis as the condition is primarily driven by T lymphocytes and local tissue macrophages.
Patients with _______ can present with systemic symptoms, including fatigue, headache, jaw claudication, and proximal muscle stiffness.
Vision loss from ocular ischemic syndrome may occur in the setting of _______.
The primary inflammatory event in temporal arteritis occurs within the vascular _______, which is not driven by circulating serum autoantibodies.
In a patient suspected of _______, the best next step for management is immediate treatment with high-dose _______ such as _______ to prevent vision loss.
Classic symptoms of _______ include headache, jaw claudication, and _______ (transient monocular vision loss).
The diagnosis of _______ is confirmed by biopsy of the temporal artery showing _______.
In the context of _______, elevated inflammatory markers such as ESR can be indicative of the condition, with typical values potentially exceeding _______.
Temporal arteritis can be associated with _______, characterized by stiffness in the proximal muscles.
Given symptoms of fatigue and proximal arm pain in a patient with suspected _______, the presence of vascular stenosis does not explain the symptoms due to the systemic nature of the vasculitis.
Use of _______ is mainly as an adjunct to corticosteroids in managing _______, rather than as a primary treatment.
In cases of suspected _______, a high erythrocyte sedimentation rate confirms significant inflammation and warrants immediate corticosteroid intervention.
For the diagnosis of _______, immediate high-dose corticosteroid treatment should be initiated once the diagnosis is suspected.
Patients with moderate carotid stenosis may experience _______ due to ocular ischemic syndrome (OIS).
Plasmapheresis is ineffective for treating _______ because the condition is primarily driven by _______, local tissue macrophages, and dendritic cells.
Temporal arteritis is characterized by systemic symptoms such as _______, _______, and _______.
In temporal arteritis, vision loss may occur due to vasculitis of the _______, potentially leading to _______.
The primary inflammatory event in temporal arteritis occurs within the _______.
For a patient with a do-not-attempt resuscitation (DNAR) order showing signs of brain death, the best next step is to _______.
If a patient is unresponsive to painful stimuli and has a DNAR order, administering _______ is _______.
In the context of brain death defined by _______, a patient should not receive _______.
Signs of brain death include the absence of _______ and lack of response to _______.
In a cardiac arrest with a patient who has signs of brain death, resuscitation attempts are likely to be _______ based on their advance directive.
The time frame typically leading to brain death following cardiopulmonary collapse is approximately _______.
In elderly patients, new onset of _______ should raise suspicion for _______.
If _______ is suspected, immediate treatment with a high-dose _______ such as _______ is essential to preserve _______.
Classic symptoms of _______ include fever, chills, weight loss, headache, and history of preceding transient vision loss known as _______.
Biopsy of the _______ showing granulomatous vasculitis is necessary for the diagnosis of _______.
Despite the presence of vascular _______, a low-molecular-weight heparin like _______ is not appropriate for patients with _______.
Preceding symptoms in patients with _______ commonly include _______ and _______.
The best first-line treatment for _______ is immediate high-dose _______ therapy, which does not generally compromise biopsy results if performed within 1 to 2 weeks.
In the case of moderate carotid stenosis, vision loss may occur due to _______ and may be associated with symptoms such as fatigue, headache, and proximal limb weakness, more consistent with _______.
Carotid artery stenting is _______ for treating temporal arteritis, as carotid stenosis primarily leads to transient monocular vision loss due to ocular ischemic syndrome.
Plasmapheresis is _______ in treating temporal arteritis since it is primarily driven by T lymphocytes and local tissue macrophages rather than a high concentration of circulating autoantibodies.
Educational objective on _______ highlights its presentation with systemic symptoms, headache, amaurosis fugax, and potentially leading to _______.
In a patient with absent pedal pulses and an ankle brachial index (ABI) of _______, the most appropriate next step in management is _______. This presentation is consistent with _______ (PVD).
The ankle brachial index (ABI) is calculated by dividing the systolic blood pressure in the _______ at the ankle by the systolic blood pressure in the _______ at the level of the _______.
A ratio of less than _______ on the ankle brachial index (ABI) indicates the presence of _______.
Patients with confirmed _______ (PVD) should be started on a _______ and an _______ for secondary prevention of coronary artery disease.
Patients commonly present with diminished peripheral pulses and other signs of _______ (PVD) which includes hairless legs with smooth skin that may ulcerate.
In a patient with absent pedal pulses but asymptomatic for claudication, acute arterial occlusion is unlikely, especially without severe pain, paresthesia, or _______.
The best treatment option for symptomatic patients with peripheral vascular disease (PVD) is _______ due to its effects on platelet aggregation and vasodilation.
An echocardiography can be used to evaluate for a cardiac _______ in patients who may present with acute limb ischemia.
Patients with acute arterial embolus typically present with symptoms such as _______, _______, and _______.
An exercise stress test is not recommended as a screening tool for asymptomatic patients because they do not typically present with _______.
Patients experiencing well-controlled hypertension should not require _______ unless they exhibit volume overload.
Metformin is indicated only for patients who have _______, as it operates by decreasing hepatic glucose production.
Ultrasonography should be performed on patients with an ABI less than 0.9 who are _______.
A common finding in peripheral vascular disease (PVD) includes absent or diminished _______.
In patients with PVD, it is essential to initiate both a _______ and an _______ for comprehensive management.
The most appropriate next step in managing a patient with primary dysmenorrhea is the initiation of _______.
Primary dysmenorrhea is characterized by pain that accompanies each menstrual cycle but is not associated with any underlying _______.
In primary dysmenorrhea, symptoms typically begin during _______ and can interfere with quality of life, such as attending _______.
To diagnose primary dysmenorrhea, causes of _______ must be ruled out, including endometriosis and pelvic inflammatory disease.
The typical findings in ultrasound for primary dysmenorrhea include a {c1::normal uterus} and {c2::normal ovaries}.
Medications such as {c1::nonsteroidal anti-inflammatory drugs} and {c2::topical heat therapy} are commonly used to treat primary dysmenorrhea.
In contrast to primary dysmenorrhea, a CT scan is typically used to evaluate underlying causes of cyclical abdominal pain, such as _______.
Reassurance is not an appropriate management step for a patient with primary dysmenorrhea due to its impact on quality of life and daily _______.
Leuprolide therapy is indicated for conditions like _______ or _______ but is not a first-line treatment for primary dysmenorrhea.
The gold standard for diagnosing _______ is stic laparoscopy.
Endometriosis is caused by the implantation of ectopic _______ outside the uterine cavity.
Symptoms of _______ include dysmenorrhea, dyspareunia, and dyschezia.
Primary dysmenorrhea is defined as pain that accompanies each menstrual cycle but is not associated with any underlying _______.
The cause of primary dysmenorrhea is _______ in response to increased prostaglandin production by the endometrium.
For the treatment of primary dysmenorrhea, nonsteroidal anti-inflammatory drugs and _______ are recommended.
If a patient experiences no symptoms outside of her menstrual period, the need for diagnostic _______ for endometriosis is unnecessary.
Persistent symptoms of primary dysmenorrhea may be treated with _______ or _______.
In an elderly patient presenting with confusion, the best next step in diagnosis to screen for a _______ is a _______.
A crescent-shaped collection on imaging indicative of a _______ will not be bound by _______.
Risk factors for developing a _______ include anticoagulant use, age-related cerebral atrophy, and _______ such as falls.
In cases of _______, the classic neurologic finding of _______ may indicate upper motor neuron lesion.
_______ in elderly patients leads to traction on bridging cortical veins, increasing the risk of _______ after minor head trauma.
Despite the presentation of confusion, assessing serum concentrations of substances like _______ is not the best step in diagnosing a _______.
Confusion combined with focal neurologic deficits in an elderly patient is more suggestive of _______ rather than _______.
In diagnosing confusion, a normal serum _______ concentration is less likely to explain focal neurologic deficits indicative of _______.
To confirm the presence of _______, clinicians rely more on clinical diagnosis rather than EEG results, as EEG does not commonly distinguish the causes of this condition.
In elderly patients, cerebral atrophy can lead to traction on _______, making them susceptible to venous injury and resulting in a _______.
Patients on _______ therapy are at an increased risk for developing a subdural hematoma, particularly after minor trauma.
Common presentations of subdural hematoma include acute or gradually progressive _______ and _______.
The first step in screening for a _______ is a CT scan of the head, which shows a crescent-shaped collection abutting the skull.
On imaging, a subdural hematoma appears as a crescent-shaped collection abutting the internal surface of the skull, and is _______ by suture lines.
Flashcard in questo deck (335)
-
1
In the management of gout, the most appropriate initial step for a patient with acute pain and a history of high alcohol intake and a purine-rich diet is to recommend a low-purine diet.
-
2
Gout presents with acute, monoarticular pain, often in the first metatarsophalangeal joint, due to the precipitation of monosodium urate crystals.
-
3
The leukocyte count in synovial fluid during an acute gout episode typically ranges from 10,000 to 50,000 mm³.
-
4
In patients with gout, chronic preventive management should involve xanthine oxidase inhibitors like allopurinol after initial lifestyle modifications are made.
-
5
Colchicine is used for acute gout flares but is not appropriate for long-term management due to risks like kidney damage and peripheral neuropathy.
-
6
Patients with gout should avoid high-purine foods and heavy alcohol consumption as part of lifestyle changes.
-
7
Gout is an acute monoarticular arthropathy resulting from an inflammatory reaction to the precipitation of monosodium urate crystals within the joint space.
-
8
Elevated levels of monosodium urate can precipitate gout flares due to increased concentration in plasma volume.
-
9
Management for acute gout attacks should include nonsteroidal anti-inflammatory drugs, colchicine, or corticosteroids.
-
10
Patients should initiate lifestyle modifications, such as reduction of purine-rich meals and heavy alcohol use, even without acute symptoms.
-
11
Arthrocentesis in gout typically shows a leukocyte count of 10,000-50,000/mm³ with negatively birefringent, needle-shaped crystals.
-
12
Chronic prevention of gout flares involves medications like xanthine oxidase inhibitors such as allopurinol.
-
13
Adding a diuretic to a patient with gout may increase the frequency of gout flares.
-
14
If a gout patient is asymptomatic and has utilized lifestyle modifications, watchful waiting may be appropriate.
-
15
In cases of multiple myeloma, patients may have renal impairment characterized by proteinuria and the presence of oval fat bodies in the urine.
-
16
The presence of 4+ blood and trace protein in urine is typically associated with multiple myeloma.
-
17
A patient with multiple myeloma often presents with symptoms including bone pain, kidney dysfunction, and monoclonal gammopathy.
-
18
Nephrotic syndrome in multiple myeloma causes hypoalbuminemia and significant edema due to overproduction of immunoglobulin.
-
19
Patients with multiple myeloma may demonstrate kidney dysfunction due to amyloid deposition in the kidneys.
-
20
The typical urinary findings for nephrotic syndrome include proteinuria and the presence of oval fat bodies.
-
21
For patients suspected of having a urinary tract infection, findings may include >50 WBC and WBC clumps in the urine, which is not typical for multiple myeloma.
-
22
The presence of pigmented granular casts and renal tubular epithelial cells suggests acute tubular necrosis, not multiple myeloma.
-
23
The clinical presentation of acute kidney injury can include symptoms such as rash, azotemia, and hematuria. Such symptoms may indicate a hypersensitivity reaction, particularly to medication.
-
24
The presence of red blood cells and red blood cell casts on urinalysis suggests bleeding from the kidney tubules, indicating a nephrogenic source, such as glomerulonephritis.
-
25
Nephritic syndrome is usually characterized by <3 g/day of urinary protein along with hypertension. Patients may exhibit signs indicating conditions such as vasculitis or systemic lupus erythematosus.
-
26
In cases of rhabdomyolysis, urinalysis typically reveals myoglobinuria, leading to red or brown urine without the presence of red blood cells.
-
27
Common causes of rhabdomyolysis include crush injuries, excessive exertion, and the use of alcohol or medications.
-
28
Dysmorphic RBCs and mild proteinuria may indicate either glomerulonephritis or a nephritic syndrome, which can lead to symptoms like hematuria and oliguria.
-
29
Multiple myeloma can present with bone pain, kidney dysfunction, and monoclonal gammopathy, potentially leading to nephrotic syndrome characterized by proteinuria and edema.
-
30
The clinical trial described is primarily designed to assess the safety of a new drug-eluting coronary artery stent for patients with acute myocardial infarction who are not surgical candidates.
-
31
In phase 1 clinical trials, patients with contraindications for chronic anticoagulation present ethical dilemmas when seeking treatment options.
-
32
Phase 1 clinical trials typically involve a small number of subjects to detect common or major safety issues, but are not powered to detect rare adverse events.
-
33
Effectiveness is assessed in phase 3 clinical trials, which evaluate treatment effects in a general patient population under real-world conditions.
-
34
Comparability in drugs refers to their ability to perform similarly when produced under different conditions, especially after manufacturing changes.
-
35
Efficacy is typically assessed in phase 2 clinical trials, where the treatment is tested in hundreds of participants to determine how well it works.
-
36
Phase 1 clinical trials are primarily designed to assess the safety of a treatment and involve small numbers of subjects.
-
37
Phase 1 trials are not powered to detect rare adverse effects of treatment due to the small number of participants involved.
-
38
Rare adverse effects can typically be detected during phase 2 and phase 3 trials which enroll hundreds of participants.
-
39
The benefits of phase 1 trials will primarily accrue to science broadly, rather than the individual patient.
-
40
Care must be taken to safeguard the ethical interests of trial participants in phase 1 trials.
-
41
During phase 1 trials, the primary focus is on assessing treatment safety, not efficacy.
-
42
Educational Objective: Phase 1 trials follow prior preclinical in vitro or animal research.
-
43
The correct answer to detecting rare adverse effects in drug trials is after conducting a post-marketing surveillance.
-
44
Phase 1 trials do not enroll enough participants to reliably detect rare adverse effects.
-
45
The most appropriate next step in diagnosis for a patient with bilateral ankle pain and swelling, without signs of osteoarthritis, is the anti-cyclic citrullinated peptide (CCP) antibody test.
-
46
When evaluating for septic arthritis, joint aspiration with Gram stain and culture is warranted if the patient presents with fever and acute onset of symptoms.
-
47
In the diagnosis of rheumatoid arthritis, serology testing includes both serum rheumatoid factor and anti-cyclic citrullinated peptide (CCP) antibody test.
-
48
MRI of the ankles is appropriate for evaluating soft tissue structures but is not the first step in a chronic ankle pain case if there is no trauma history.
-
49
Patients with rheumatoid arthritis may present with symptoms such as bilateral ankle pain, swelling, and lack of degenerative changes on x-ray.
-
50
The presence of more than 50,000 leukocytes/mm³ with infectious agents on joint aspiration would indicate septic arthritis rather than rheumatoid arthritis.
-
51
In cases of suspected deep venous thrombosis (DVT), venous duplex ultrasonography is a reasonable next step. Symptoms of DVT include lower extremity swelling in the affected limb and possible calf pain on ankle dorsiflexion.
-
52
Rheumatoid arthritis is an autoimmune disease that causes inflammation in synovial tissues, leading to bilateral joint involvement with synovial hypertrophy. It can also present with extra-articular manifestations.
-
53
Common manifestations of rheumatoid arthritis include rheumatoid nodules, pulmonary fibrosis, and skin rash.
-
54
For diagnosing rheumatoid arthritis, serology testing includes rheumatoid factor which is sensitive, and anti-cyclic citrullinated peptide (CCP) antibody testing, which is specific for the disease.
-
55
When evaluating a patient for ankle pain and swelling, it is more likely they have rheumatoid arthritis than bilateral DVT.
-
56
In pregnant patients, diagnostic pivots must strongly consider the possibility of conditions such as deep venous thrombosis (DVT) even with other signs and symptoms.
-
57
The best next step in a clinical scenario of a patient with suspected rheumatoid arthritis and joint pain is anti-cyclic citrullinated peptide (CCP) antibody test.
-
58
In a patient with increased cholesterol concentration, the most appropriate next step to assess potential hypothyroidism is the measurement of serum thyroid-stimulating hormone (TSH) concentration.
-
59
Hypothyroidism may cause vague symptoms like weight gain and unexplained fatigue. It is characterized by low levels of thyroid hormones leading to increased serum cholesterol concentration.
-
60
The mechanism by which hypothyroidism increases serum cholesterol is through decreased activity of HMG-CoA reductase, affecting cholesterol synthesis and absorption.
-
61
In patients with primary hypothyroidism, increased serum thyrotropin-releasing hormone and thyroid-stimulating hormone (TSH) concentrations are typically observed due to feedback from low thyroid hormone levels.
-
62
A common presentation of hypothyroidism includes symptoms such as fatigue, weight gain, and cold intolerance.
-
63
When evaluating hypercholesterolemia, it is incorrect to measure serum C-reactive protein concentration as it is not a standard test for this condition.
-
64
In hypothyroidism, low thyroid hormone levels lead to decreased production of low-density lipoprotein (LDL) receptors in the liver, increasing serum cholesterol levels.
-
65
In the workup of hypercholesterolemia, measuring serum follicle-stimulating hormone concentration (FSH) is not useful.
-
66
Homocystinuria, characterized by increased homocysteine levels, is associated with symptoms like intellectual disability and lens subluxation.
-
67
Primary biliary cirrhosis (PBC) may present with jaundice, pruritus, and hypercholesterolemia.
-
68
Hypothyroidism presents with symptoms such as fatigue, weight gain, and cold intolerance.
-
69
In hypothyroidism, hypercholesterolemia occurs due to ⬇️ endogenous cholesterol synthesis and decreased LDL receptor production.
-
70
The treatment for hypothyroidism includes levothyroxine supplementation and monitoring of serum TSH concentration.
-
71
To diagnose primary biliary cirrhosis, an abnormal serum mitochondrial antibody assay is relevant.
-
72
In the case of a 2-year-old boy with apnea after surgery, the best next step to prevent recurrence of such an opioid overdose is to conduct a root cause analysis (RCA). RCA identifies core systems-level issues that lead to adverse events.
-
73
The multidisciplinary team in an RCA conducts analysis using tools like creating a timeline and surveying controls that may have failed.
-
74
Educational interventions that target individual errors, such as reporting a nurse for a morphine overdose, are less effective because most adverse events stem from systems-level causes rather than individual errors.
-
75
In root cause analysis, it's crucial to analyze the entire process rather than focus on individual components, which may include verifying the patient's weight or confirming drug doses, as they often don't address the underlying system issues.
-
76
Analyzing opioid toxicity cases emphasizes the importance of systematic procedures over individual assessments, highlighting that lack of standardized opioid administration procedures can lead to adverse outcomes.
-
77
The most likely diagnosis for a 57-year-old man with a history of recurrent pneumonia, coughing up blood, and crackles at lung bases is bronchiectasis.
-
78
In bronchiectasis, patients typically present with frequent cough and excessive sputum production.
-
79
Recurrent necrotizing infections and chronic inflammation lead to irreversible bronchi dilatation in bronchiectasis.
-
80
Bronchiectasis can be associated with chronic bronchial obstruction and cystic fibrosis.
-
81
A CT scan is used to confirm the diagnosis of bronchiectasis.
-
82
Management of bronchiectasis includes airway clearance techniques and antibiotics for acute exacerbations.
-
83
Mitral stenosis presents with a diastolic murmur over the left intercostal space, not a systolic murmur.
-
84
Sarcoidosis commonly presents with shortness of breath and cough, especially in younger patients.
-
85
The correct management for the patient with bronchiectasis includes identifying and treating the underlying disorder.
-
86
Patients with bronchiectasis often have a history of recurrent episodes of pneumonia in childhood.
-
87
In patients with bronchiectasis, CT scan of the chest is used for diagnosis confirmation.
-
88
Management of bronchiectasis includes airway clearance techniques such as chest physiotherapy and expectorants.
-
89
DDuring acute exacerbations of bronchiectasis, antibiotics are prescribed to address the infection.
-
90
Chronic inflammation and necrotizing infections may lead to impaired mucociliary clearance in patients with bronchiectasis.
-
91
The most significant imaging finding associated with bronchiectasis can be visualized in a CT scan: focal bronchial dilation.
-
92
For optimal management, recognizing underlying disorders contributing to bronchiectasis is crucial in developing a treatment plan.
-
93
In diagnosing bronchiectasis, it’s important to consider conditions that result in impaired mucociliary clearance.
-
94
In an 8-year-old boy presenting with severe abdominal pain and fever, the clear clinical diagnosis of appendicitis indicates that the best next step is operative intervention.
-
95
Appendicitis in children often results from obstruction of the appendix due to fecalith or lymphoid hyperplasia.
-
96
Acute appendicitis typically presents with abdominal pain starting periumbilically and later migrating to the right lower quadrant.
-
97
In a patient diagnosed with appendicitis, the presence of leukocytosis (predominantly neutrophilic) supports the diagnosis.
-
98
Measurement of serum C-reactive protein is nonspecific and does not confirm appendicitis even if elevated.
-
99
In equivocal cases of appendicitis, imaging like ultrasonography or CT scan may assist in diagnosis, but should not delay operative intervention if a clear clinical diagnosis is present.
-
100
When evaluating a child for appendicitis, symptoms such as fever and localized tenderness in the right lower quadrant support a diagnosis requiring surgical intervention.
-
101
The clinical diagnosis related to bacterial proliferation in the appendix is called acute appendicitis. This condition leads to leukocytosis with a predominantly neutrophilic response.
-
102
In the treatment of acute appendicitis, the best next step is to administer intravenous antibiotics and perform an operative intervention.
-
103
Bacterial proliferation in the appendix causes a predominantly neutrophilic leukocytosis, which is a key diagnostic marker.
-
104
Operative intervention for acute appendicitis is typically performed using a laparoscopic technique.
-
105
In a clinical scenario of appendicitis, leukocytosis due to bacterial proliferation is predominantly neutrophilic, which helps in diagnosis.
-
106
A previously healthy 8-year-old boy with abdominal pain may present with signs of acute appendicitis.
-
107
Acute appendicitis treatment often necessitates the use of intravenous antibiotics prior to surgical intervention.
-
108
Acute appendicitis is characterized by bacterial proliferation within the lumen and wall of the appendix.
-
109
In the case of a 47-year-old woman with an itchy rash, the best next step in management for her type I hypersensitivity reaction is Diphenhydramine therapy.
-
110
Urticaria is caused by a type I hypersensitivity reaction resulting in the release of histamine, which causes localized symptoms.
-
111
The symptoms of type I hypersensitivity include pruritus, edema, and urticaria.
-
112
In a patient with a known peanut allergy experiencing urticarial reactions, skin testing for peanut allergy is not necessary as they already have a diagnosis.
-
113
First-generation H1 antihistamines, such as diphenhydramine, can be used to treat symptoms of urticaria in type I hypersensitivity reactions.
-
114
After administering treatment for urticaria, clinicians may consider skin testing for other allergens to identify triggers.
-
115
In urticaria management, the patient is more likely to benefit from avoidance of the offending allergen and administration of H1 antihistamines.
-
116
In the case of an urticarial rash due to a type I hypersensitivity reaction, the appropriate initial treatment is antihistamine.
-
117
Systemic lupus erythematosus and rheumatoid arthritis are examples of immune disorders.
-
118
Prednisone can be used with antihistamines, but alone is not a first-line treatment for urticaria.
-
119
A skin biopsy with immunofluorescence is typically reserved for a refractory rash of unexplained etiology.
-
120
Type I hypersensitivity reactions are caused by IgE-mediated inflammation.
-
121
The release of histamine, prostaglandins, and leukotrienes is triggered by the cross-linking of IgE on basophils and mast cells.
-
122
Management of non-life threatening manifestations like urticaria involves the removal of the allergen and treatment with an antihistamine.
-
123
The most likely diagnosis for a 7-year-old boy showing disruptive behavior in reading classes, with a family history of reading difficulties, is Dyslexia.
-
124
Dyslexia is characterized by a specific learning disability in reading or reading difficulty, often caused by a cognitive deficit in phonologic processing.
-
125
Assessment of fluency, decoding, and comprehension is necessary for diagnosing dyslexia.
-
126
Common risk factors for dyslexia include a family history of reading difficulty, prematurity, and neurodevelopmental conditions such as attention-deficit/hyperactivity disorder.
-
127
Treatment for dyslexia often involves educational interventions to improve literacy and reading comprehension.
-
128
In cases where a child acts out, it may be a response to frustration related to their reading challenges, rather than behavioral issues alone.
-
129
In a patient with oppositional defiant disorder, they typically display anger and defiance towards caretakers. However, in this case, the patient does not have problems at home.
-
130
Dyslexia is a learning disability characterized by difficulty in reading or reading-related tasks due to a cognitive deficit in phonologic processing.
-
131
School-age patients with dyslexia often exhibit difficulties in classes involving reading, and they may act out in response to frustration.
-
132
A common condition in school-age children that leads to behavioral issues is dyslexia, which necessitates understanding and intervention.
-
133
When evaluating a child with learning difficulties, it is important to rule out dyslexia as a possible cause, especially if they act out in frustration.
-
134
The educational objective highlights that dyslexia is linked to a cognitive deficit in phonologic processing.
-
135
The image shows a case concerning a 7-year-old boy who exhibits behavior concerns at school possibly related to dyslexia.
-
136
The most likely cause of the patient's urinary leakage after her vaginal hysterectomy is a bladder injury resulting in a vesicovaginal fistula.
-
137
Vesicovaginal fistulas can occur as a consequence of gynecologic surgery, pelvic pathology, or radiation therapy.
-
138
In patients with vesicovaginal fistula, the main symptom is usually painless urinary leakage from the vagina, often due to abdominal pressure.
-
139
The confirmatory test for a suspected vesicovaginal fistula involves infusing dyed sterile fluid into the bladder to check for transmitted dye in the vagina.
-
140
Cystitis typically presents with symptoms like urgency, frequency, dysuria, which this patient does not exhibit.
-
141
Stress incontinence is characterized by urinary leakage with activities that increase intra-abdominal pressure, such as laughing or sneezing.
-
142
Unlike stress incontinence, this patient’s condition is not associated with increases in intra-abdominal pressure, emphasizing a bladder injury as the primary concern.
-
143
The condition characterized by painless urinary leakage from the bladder into the vagina, often leading to a pool of urine in the vaginal canal, can be indicative of a bladder injury.
-
144
In a clinical scenario where a patient presents with a loss of clear, yellow vaginal fluid while walking, the best next step in management is to consider bladder injury.
-
145
When evaluating a female patient with urinary leakage, it's crucial to assess for urogenital injuries due to the anatomical proximity of the bladder and vagina.
-
146
In the case of a 42-year-old woman presenting with vaginal fluid leakage, the differential diagnosis should include potential bladder injury.
-
147
For a 72-year-old woman with 80% stenosis of the right internal carotid artery, endarterectomy reduces the risk of stroke or death from 10% to 5% at 5 years. The absolute risk reduction (ARR) is 5%.
-
148
The number needed to treat (NNT) for endarterectomy to prevent one stroke or death is calculated as 20. This is derived from the formula NNT = 1 / ARR, where ARR is 5%.
-
149
Endarterectomy decreases the absolute risk for stroke or death by 50% is incorrect. This corresponds to relative risk reduction (RRR).
-
150
The correct interpretation of endarterectomy effectiveness indicates that endarterectomy prevents 5% of strokes or deaths, which is not the same as the total effect.
-
151
When interpreting clinical trial results, it is critical to understand that the number of endarterectomies needed to prevent one stroke or death is 20 based on the observable ARR.
-
152
Relative risk (RR) is defined by the formula RR = risk in treatment group / risk in control group. In this case, RR = 0.5.
-
153
In clinical decision-making for interventions, the number needed to treat (NNT) is defined as the number of individuals who need to receive an intervention to prevent one negative outcome, calculated by the inverse of the absolute risk reduction (ARR). If the ARR is 5 ext{%}, then the NNT is 20.
-
154
For a clinical intervention with an ARR of 5 ext{%}, the calculation for NNT follows this formula: NNT = 1 / ARR.
-
155
When considering an asymptomatic 72-year-old woman with 80 ext{%} stenosis of the right internal carotid artery, the NNT to prevent stroke or death is 20.
-
156
The formula for calculating NNT is given by NNT = 1 / (absolute risk reduction); for an ARR of 0.05, NNT equals 20.
-
157
For a 17-year-old girl experiencing severe cramps starting 3 days before menses lasting 5 days, the most appropriate next step in management for primary dysmenorrhea is oral contraceptive therapy.
-
158
Primary dysmenorrhea in patients often manifests as lower abdominal or pelvic pain that begins several days prior to the onset of menses.
-
159
In diagnosing primary dysmenorrhea, it is essential to rule out secondary causes such as endometriosis or pelvic inflammatory disease.
-
160
Treatment for primary dysmenorrhea may include nonsteroidal anti-inflammatory drugs and oral contraceptives.
-
161
A CT scan is not the first step for diagnosing primary dysmenorrhea due to the lack of underlying abnormalities suggested by ultrasonography.
-
162
Reassurance is inappropriate in cases of primary dysmenorrhea since symptoms can significantly impact a patient’s quality of life and daily activities.
-
163
Laparoscopy is the gold standard used in the diagnosis of endometriosis.
-
164
Endometriosis is caused by implantation of ectopic endometrial tissue outside of the uterine cavity.
-
165
The classic symptoms of endometriosis include dysmenorrhea, dyspareunia, and dyschezia.
-
166
A pelvic examination may reveal tenderness of the uterine wall and possible uterine immobility due to pelvic adhesions.
-
167
Primary dysmenorrhea is defined as pain that accompanies each menstrual cycle without any underlying pathology.
-
168
The mechanism behind primary dysmenorrhea involves uterine vasoconstriction in response to increased prostaglandin production by the endometrium.
-
169
The main treatments for primary dysmenorrhea include nonsteroidal anti-inflammatory drugs and topical heat therapy.
-
170
For persistent symptoms of primary dysmenorrhea, options include oral contraceptive therapy or a progestin IUD.
-
171
If a patient has no symptoms outside of her menstrual period, the need for diagnostic laparoscopy is unlikely.
-
172
In an elderly patient with progressive confusion, the best next step in diagnosis to screen for subdural hematoma (SDH) is to perform a CT scan of the head.
-
173
Common risk factors for subdural hematoma (SDH) include anticoagulant use, advanced age, and cerebral atrophy.
-
174
Elderly patients with a history of minor trauma may present with progressive neurologic deficits due to a subdural hematoma.
-
175
The appearance of a subdural hematoma (SDH) on a CT scan is typically a crescent-shaped collection abutting the internal surface of the skull.
-
176
The presence of pronator drift during an examination may indicate an upper motor neuron lesion such as that seen in subdural hematoma.
-
177
A key difference between stroke and subdural hematoma is that stroke typically presents with acute neurologic deficits compared to the gradual progression seen in SDH.
-
178
In cases of suspected subdural hematoma (SDH), clinical signs may evolve over time, leading to findings consistent with increased intracranial pressure.
-
179
For an elderly patient with confusion and risk factors, performing a measurement of serum vitamin B12 is inappropriate, as it would not address the concern of subdural hematoma (SDH).
-
180
While assessing an elderly patient with confusion, the presence of multiple small abrasions and ecchymoses can indicate potential underlying injuries such as a subdural hematoma.
-
181
To confirm the presence of encephalopathy, a clinical diagnosis can often be made without the need for an EEG.
-
182
In elderly patients, cerebral atrophy can lead to traction on bridging cortical veins, increasing the risk of subdural hematoma after minor trauma.
-
183
Patients on anticoagulation therapy have an increased risk of developing subdural hematoma due to venous injury.
-
184
When evaluating a suspected subdural hematoma, a CT scan of the head is the first step in screening.
-
185
On imaging, a subdural hematoma appears as a crescent-shaped collection abutting the internal surface of the skull.
-
186
Patients presenting with confusion and neurologic deficits that are progressive rather than episodic likely have encephalopathy rather than episodic epileptic activity.
-
187
The presence of acute or gradually progressive focal neurologic deficits and confusion can indicate a potential subdural hematoma.
-
188
In a patient with flatfoot (pes planus) who exhibits no symptoms or history of trauma, no additional diagnostic studies are indicated. Which of the following would be the best next step? No additional diagnostic studies are indicated.
-
189
Flatfoot, also known as pes planus, can be congenital or acquired from various factors such as trauma or long-standing diabetes mellitus.
-
190
In cases of symptomatic flatfoot, initial management includes the use of orthotics, nonsteroidal anti-inflammatory drugs, and activity modification.
-
191
Flexible flatfoot occurs when the loss of the medial longitudinal arch is apparent during standing, returning when the patient is off their feet.
-
192
Imaging studies in flatfoot are not routinely required unless there are symptoms or history of trauma. If advanced imaging is necessary, MRI would be preferred over CT.
-
193
The most common site for osseous metastases evaluated with a radionuclide bone scan is the hip and femur, not the foot or ankle.
-
194
In managing gout, the best first-line treatment is typically the use of nonsteroidal anti-inflammatory drugs (NSAIDs).
-
195
For a patient with rheumatoid arthritis, considering activity modification is essential when tailoring a comprehensive management plan.
-
196
In the presence of multiple myeloma, the key diagnostic pivot is the evaluation of serum protein electrophoresis.
-
197
The management of patient activity should be tailored based on the severity of the condition, and modification is essential in cases of chronic pain or inflammatory disorders.
-
198
When prescribing nonsteroidal anti-inflammatory drugs, always ensure that patients are informed about the potential risk of gastrointestinal bleeding.
-
199
In an elderly patient presenting with temporal arteritis, immediate treatment with a high-dose corticosteroid such as prednisone is essential to prevent irreversible vision loss.
-
200
Classic symptoms of temporal arteritis include fever, chills, weight loss, headache, and transient vision loss (amaurosis fugax) as well as jaw claudication.
-
201
When considering treatment in a patient suspected of having temporal arteritis, the addition of methotrexate is primarily as an adjunct to corticosteroids, not as a monotherapy.
-
202
In the context of assessing a patient with '{}temporal arteritis'', elevated inflammatory markers such as an ESR > 40 mm/h and possible thrombocytosis can be indicative.
-
203
For patients with temporal arteritis, biopsy of the temporal artery showing granulomatous vasculitis is necessary for definitive diagnosis.
-
204
In patients with temporal arteritis, immediate high-dose corticosteroid treatment should occur once the diagnosis is suspected, and it does not generally compromise biopsy results if performed within 1 to 2 weeks.
-
205
Temporal arteritis is primarily driven by T lymphocytes, local tissue macrophages, and dendritic cells.
-
206
A constellation of symptoms in temporal arteritis includes fatigue, headache, and proximal limb weakness.
-
207
Unlike some systemic vasculitides, plasmapheresis is not effective in treating temporal arteritis due to the underlying pathophysiology not being driven by high concentrations of circulating serum autoantibodies.
-
208
Carotid stenosis may lead to transient monocular vision loss in the setting of ocular ischemic syndrome (OIS).
-
209
In the case of carotid artery stenosis, vision loss can occur depending on the degree of collateralization between the internal and external carotid vascular systems.
-
210
Temporal arteritis can present with symptoms such as amaurosis fugax and jaw claudication, highlighting its systemic involvement.
-
211
The incorrect choice for treating carotid stenosis in the described scenario was placing a carotid artery stent.
-
212
The background inflammatory event in temporal arteritis occurs within the vascular adventitia.
-
213
In a case where a patient has a do-not-attempt resuscitation (DNAR) order and shows signs of brain death, the most appropriate next step is to inform the patient's family that he has died.
-
214
In patients with a DNAR order, CPR should not be attempted if they show evidence of brain death since it is likely to be futile.
-
215
Brain death is defined as the permanent loss of all brainstem functions and is diagnosed through neurologic examination and an apnea test.
-
216
Cardiopulmonary resuscitation (CPR) can only be attempted for patients in cardiac arrest who do not have a do-not-attempt resuscitation order and are not yet brain dead.
-
217
When a patient is categorized as brain dead, they will not respond to painful stimuli, and administering pain relief like morphine is unnecessary.
-
218
In patients with peripheral vascular disease (PVD), an ankle brachial index (ABI) less than 0.9 indicates occlusive arterial vascular disease.
-
219
Patients diagnosed with PVD should be started on an antiplatelet agent, such as aspirin, for secondary prevention of coronary artery disease.
-
220
An ABI of 0.8 in the presence of absent pedal pulses is consistent with peripheral vascular disease.
-
221
Despite normal total cholesterol and LDL levels, patients with PVD still need aspirin therapy as part of their management plan.
-
222
The primary reason for an ankle brachial index (ABI) test in a patient is to assess for peripheral vascular disease (PVD).
-
223
In the assessment of a patient with PVD, the absence of symptoms like pain paired with an ABI of 0.8 indicates that acute limb ischemia is unlikely.
-
224
When managing a patient with PVD, lifestyle changes such as smoking cessation are crucial.
-
225
In patients with peripheral vascular disease (PVD), cilostazol is effective for symptomatic improvement by inhibiting platelet aggregation and causing vasodilation.
-
226
If a patient with PVD is asymptomatic, it is premature to start treatment with cilostazol or any antiplatelet agents.
-
227
Echocardiography can evaluate for a potential cardiac thrombus source in acute arterial embolus cases presenting with acute limb ischemia, which includes symptoms like severe pain and pallor.
-
228
An exercise stress test is used for assessing ischemic cardiac disease, typically presenting with symptoms like exertional chest pressure and dyspnea. It is not recommended for asymptomatic patients.
-
229
Hydrochlorothiazide therapy is indicated in patients with volume overload or uncontrolled hypertension, and is not necessary in patients whose hypertension is well-controlled.
-
230
Metformin is used primarily to manage diabetes mellitus and works by decreasing hepatic glucose production and improving insulin sensitivity.
-
231
In patients with an ABI less than 0.9 who are symptomatic, duplex ultrasonography is useful to define the extent of PVD; however, it is unnecessary in asymptomatic patients.
-
232
Patients with peripheral vascular disease (PVD) often exhibit absent or diminished peripheral pulses and hairless legs with smooth skin.
-
233
All patients with PVD should be started on a statin and an antiplatelet agent for management.
-
234
The condition characterized by loss of the medial longitudinal arch and heel eversion is called flatfoot or pes planus.
-
235
In the absence of symptoms and trauma, no additional diagnostic studies are indicated for flatfoot.
-
236
Flexible flatfoot occurs when the arch loss only happens during standing, returning when the foot is lifted.
-
237
Initial management for symptomatic flatfoot includes orthotics, nonsteroidal anti-inflammatory drugs, and activity modification.
-
238
Imaging studies like CT scan or MRI are not routinely required for diagnosing flatfoot unless there is trauma or reported symptoms.
-
239
A radionuclide bone scan is generally used to evaluate for osteoblastic osseous metastases but is not indicated for flatfoot.
-
240
Patients with flatfoot may be asymptomatic but their condition can alter biomechanics and potentially lead to pain.
-
241
In adults, dysfunction of the posterior tibial tendon is often implicated in cases of acquired flatfoot.
-
242
In the management of gout, nonsteroidal anti-inflammatory drugs (NSAIDs) are commonly used to alleviate pain during acute attacks.
-
243
The best next step for a patient with acute pain and swelling in the big toe is to start NSAIDs.
-
244
For managing chronic gout, activity modification is recommended to reduce flare-ups.
-
245
In addition to pharmacotherapy, patients with gout should consider activity modification and dietary adjustments to limit triggers.
-
246
In the case of an 80-year-old woman with symptoms of temporal arteritis, the most appropriate next step in management is immediate treatment with prednisone to preserve vision.
-
247
Symptoms such as transient monocular vision loss, headache, and fatigue in an elderly patient raise suspicion for temporal arteritis.
-
248
The classic symptoms of temporal arteritis may include fever, chills, weight loss, jaw claudication, and headaches, as well as amaurosis fugax.
-
249
In cases of temporal arteritis, there is a risk of irreversible vision loss due to ischemic damage from occlusion of the ophthalmic artery.
-
250
Laboratory findings in patients with temporal arteritis often include increased inflammatory markers such as ESR and C-reactive protein.
-
251
When diagnosing temporal arteritis, a biopsy of the temporal artery is performed to confirm the presence of granulomatous vasculitis.
-
252
Despite vascular stenosis in an elderly patient, the presence of symptoms such as headaches and proximal extremity weaknesses may indicate the need for quick treatment of temporal arteritis with corticosteroids rather than complications of stenosis alone.
-
253
For patients diagnosed with temporal arteritis, immediate high-dose corticosteroid treatment should occur once the diagnosis is suspected.
-
254
Carotid stenosis may lead to transient monocular vision loss in the setting of ocular ischemic syndrome (OIS).
-
255
Plasmapheresis is not effective in the treatment of temporal arteritis as the condition is primarily driven by T lymphocytes and local tissue macrophages.
-
256
Patients with temporal arteritis can present with systemic symptoms, including fatigue, headache, jaw claudication, and proximal muscle stiffness.
-
257
Vision loss from ocular ischemic syndrome may occur in the setting of moderate or severe carotid stenosis.
-
258
The primary inflammatory event in temporal arteritis occurs within the vascular adventitia, which is not driven by circulating serum autoantibodies.
-
259
In a patient suspected of temporal arteritis, the best next step for management is immediate treatment with high-dose corticosteroids such as prednisone to prevent vision loss.
-
260
Classic symptoms of temporal arteritis include headache, jaw claudication, and amaurosis fugax (transient monocular vision loss).
-
261
The diagnosis of temporal arteritis is confirmed by biopsy of the temporal artery showing granulomatous vasculitis.
-
262
In the context of temporal arteritis, elevated inflammatory markers such as ESR can be indicative of the condition, with typical values potentially exceeding 40 mm/h.
-
263
Temporal arteritis can be associated with polymyalgia rheumatica, characterized by stiffness in the proximal muscles.
-
264
Given symptoms of fatigue and proximal arm pain in a patient with suspected temporal arteritis, the presence of vascular stenosis does not explain the symptoms due to the systemic nature of the vasculitis.
-
265
Use of methotrexate is mainly as an adjunct to corticosteroids in managing temporal arteritis, rather than as a primary treatment.
-
266
In cases of suspected temporal arteritis, a high erythrocyte sedimentation rate confirms significant inflammation and warrants immediate corticosteroid intervention.
-
267
For the diagnosis of temporal arteritis, immediate high-dose corticosteroid treatment should be initiated once the diagnosis is suspected.
-
268
Patients with moderate carotid stenosis may experience transient monocular vision loss due to ocular ischemic syndrome (OIS).
-
269
Plasmapheresis is ineffective for treating temporal arteritis because the condition is primarily driven by T lymphocytes, local tissue macrophages, and dendritic cells.
-
270
Temporal arteritis is characterized by systemic symptoms such as headache, amaurosis fugax, and proximal muscle stiffness.
-
271
In temporal arteritis, vision loss may occur due to vasculitis of the ophthalmic artery, potentially leading to blindness.
-
272
The primary inflammatory event in temporal arteritis occurs within the vascular adventitia.
-
273
For a patient with a do-not-attempt resuscitation (DNAR) order showing signs of brain death, the best next step is to inform the patient's family that he has died.
-
274
If a patient is unresponsive to painful stimuli and has a DNAR order, administering CPR is not appropriate.
-
275
In the context of brain death defined by permanent loss of all brainstem functions, a patient should not receive CPR.
-
276
Signs of brain death include the absence of cranial nerve reflexes and lack of response to painful stimuli.
-
277
In a cardiac arrest with a patient who has signs of brain death, resuscitation attempts are likely to be futile based on their advance directive.
-
278
The time frame typically leading to brain death following cardiopulmonary collapse is approximately 5 minutes.
-
279
In elderly patients, new onset of headaches should raise suspicion for temporal arteritis.
-
280
If temporal arteritis is suspected, immediate treatment with a high-dose corticosteroid such as prednisone is essential to preserve vision.
-
281
Classic symptoms of temporal arteritis include fever, chills, weight loss, headache, and history of preceding transient vision loss known as amaurosis fugax.
-
282
Biopsy of the temporal artery showing granulomatous vasculitis is necessary for the diagnosis of temporal arteritis.
-
283
Despite the presence of vascular stenosis, a low-molecular-weight heparin like dalteparin is not appropriate for patients with temporal arteritis.
-
284
Preceding symptoms in patients with temporal arteritis commonly include proximal extremity weakness and fatigue.
-
285
The best first-line treatment for temporal arteritis is immediate high-dose corticosteroid therapy, which does not generally compromise biopsy results if performed within 1 to 2 weeks.
-
286
In the case of moderate carotid stenosis, vision loss may occur due to ocular ischemic syndrome (OIS) and may be associated with symptoms such as fatigue, headache, and proximal limb weakness, more consistent with temporal arteritis.
-
287
Carotid artery stenting is incorrect for treating temporal arteritis, as carotid stenosis primarily leads to transient monocular vision loss due to ocular ischemic syndrome.
-
288
Plasmapheresis is not effective in treating temporal arteritis since it is primarily driven by T lymphocytes and local tissue macrophages rather than a high concentration of circulating autoantibodies.
-
289
Educational objective on temporal arteritis highlights its presentation with systemic symptoms, headache, amaurosis fugax, and potentially leading to blindness.
-
290
In a patient with absent pedal pulses and an ankle brachial index (ABI) of 0.8, the most appropriate next step in management is aspirin therapy. This presentation is consistent with peripheral vascular disease (PVD).
-
291
The ankle brachial index (ABI) is calculated by dividing the systolic blood pressure in the lower extremity at the ankle by the systolic blood pressure in the arm at the level of the brachial artery.
-
292
A ratio of less than 0.9 on the ankle brachial index (ABI) indicates the presence of occlusive arterial vascular disease.
-
293
Patients with confirmed peripheral vascular disease (PVD) should be started on a statin and an antiplatelet agent for secondary prevention of coronary artery disease.
-
294
Patients commonly present with diminished peripheral pulses and other signs of peripheral vascular disease (PVD) which includes hairless legs with smooth skin that may ulcerate.
-
295
In a patient with absent pedal pulses but asymptomatic for claudication, acute arterial occlusion is unlikely, especially without severe pain, paresthesia, or pulselessness.
-
296
The best treatment option for symptomatic patients with peripheral vascular disease (PVD) is cilostazol due to its effects on platelet aggregation and vasodilation.
-
297
An echocardiography can be used to evaluate for a cardiac thrombus in patients who may present with acute limb ischemia.
-
298
Patients with acute arterial embolus typically present with symptoms such as severe pain, pallor, and pulselessness.
-
299
An exercise stress test is not recommended as a screening tool for asymptomatic patients because they do not typically present with exertional chest pressure.
-
300
Patients experiencing well-controlled hypertension should not require hydrochlorothiazide unless they exhibit volume overload.
-
301
Metformin is indicated only for patients who have diabetes mellitus, as it operates by decreasing hepatic glucose production.
-
302
Ultrasonography should be performed on patients with an ABI less than 0.9 who are symptomatic.
-
303
A common finding in peripheral vascular disease (PVD) includes absent or diminished peripheral pulses.
-
304
In patients with PVD, it is essential to initiate both a statin and an antiplatelet agent for comprehensive management.
-
305
The most appropriate next step in managing a patient with primary dysmenorrhea is the initiation of oral contraceptive therapy.
-
306
Primary dysmenorrhea is characterized by pain that accompanies each menstrual cycle but is not associated with any underlying pathology.
-
307
In primary dysmenorrhea, symptoms typically begin during adolescence and can interfere with quality of life, such as attending school.
-
308
To diagnose primary dysmenorrhea, causes of secondary dysmenorrhea must be ruled out, including endometriosis and pelvic inflammatory disease.
-
309
The typical findings in ultrasound for primary dysmenorrhea include a {c1::normal uterus} and {c2::normal ovaries}.
-
310
Medications such as {c1::nonsteroidal anti-inflammatory drugs} and {c2::topical heat therapy} are commonly used to treat primary dysmenorrhea.
-
311
In contrast to primary dysmenorrhea, a CT scan is typically used to evaluate underlying causes of cyclical abdominal pain, such as leiomyomata uteri.
-
312
Reassurance is not an appropriate management step for a patient with primary dysmenorrhea due to its impact on quality of life and daily activities.
-
313
Leuprolide therapy is indicated for conditions like menorrhagia or endometriosis but is not a first-line treatment for primary dysmenorrhea.
-
314
The gold standard for diagnosing endometriosis is stic laparoscopy.
-
315
Endometriosis is caused by the implantation of ectopic endometrial tissue outside the uterine cavity.
-
316
Symptoms of endometriosis include dysmenorrhea, dyspareunia, and dyschezia.
-
317
Primary dysmenorrhea is defined as pain that accompanies each menstrual cycle but is not associated with any underlying pathology.
-
318
The cause of primary dysmenorrhea is uterine vasoconstriction in response to increased prostaglandin production by the endometrium.
-
319
For the treatment of primary dysmenorrhea, nonsteroidal anti-inflammatory drugs and topical heat therapy are recommended.
-
320
If a patient experiences no symptoms outside of her menstrual period, the need for diagnostic laparoscopy for endometriosis is unnecessary.
-
321
Persistent symptoms of primary dysmenorrhea may be treated with oral contraceptive therapy or progestin IUD.
-
322
In an elderly patient presenting with confusion, the best next step in diagnosis to screen for a subdural hematoma (SDH) is a CT scan of the head.
-
323
A crescent-shaped collection on imaging indicative of a subdural hematoma (SDH) will not be bound by suture lines.
-
324
Risk factors for developing a subdural hematoma (SDH) include anticoagulant use, age-related cerebral atrophy, and minor trauma such as falls.
-
325
In cases of subdural hematoma (SDH), the classic neurologic finding of pronator drift may indicate upper motor neuron lesion.
-
326
Cerebral atrophy in elderly patients leads to traction on bridging cortical veins, increasing the risk of subdural hematoma (SDH) after minor head trauma.
-
327
Despite the presentation of confusion, assessing serum concentrations of substances like lipoprotein(a) is not the best step in diagnosing a subdural hematoma (SDH).
-
328
Confusion combined with focal neurologic deficits in an elderly patient is more suggestive of subdural hematoma (SDH) rather than stroke.
-
329
In diagnosing confusion, a normal serum thyroid-stimulating hormone concentration is less likely to explain focal neurologic deficits indicative of subdural hematoma (SDH).
-
330
To confirm the presence of encephalopathy, clinicians rely more on clinical diagnosis rather than EEG results, as EEG does not commonly distinguish the causes of this condition.
-
331
In elderly patients, cerebral atrophy can lead to traction on bridging cortical veins, making them susceptible to venous injury and resulting in a subdural hematoma.
-
332
Patients on anticoagulation therapy are at an increased risk for developing a subdural hematoma, particularly after minor trauma.
-
333
Common presentations of subdural hematoma include acute or gradually progressive focal neurologic deficits and confusion.
-
334
The first step in screening for a subdural hematoma is a CT scan of the head, which shows a crescent-shaped collection abutting the skull.
-
335
On imaging, a subdural hematoma appears as a crescent-shaped collection abutting the internal surface of the skull, and is not bound by suture lines.
Gout Management
Case Summary
A 56-year-old man presents after a severe attack of right great toe pain, which resolved with naproxen. He has a history of hyperlipidemia and consumes alcohol frequently.
Key Points
- Diagnosis: Gout - caused by monosodium urate crystal precipitation in joints.
- Symptoms: Acute monoarticular pain, especially in the first metatarsophalangeal joint.
- Management Goal: Prevent future attacks and manage underlying causes.
Next Steps in Management
- Lifestyle Modifications:
- Decrease alcohol intake.
- Recommend a low-purine diet (answer C).
- Medications: Avoid colchicine as long-term therapy due to adverse effects.
- Allopurinol can be considered for chronic management after dietary changes.
Incorrect Options Explained
- A) Colchicine is used for acute episodes, not for long-term management.
- B) Allopurinol is for chronic use; start dietary mod first.
- D) Switching antihypertensive medications does not directly address gout.
- E) No additional steps are necessary for newly diagnosed gout.
Multiple Myeloma
Case Overview
A 62-year-old man with back pain, numbness, and facial swelling. Lab shows monoclonal gammopathy.
Key Points
- Diagnosis: Multiple Myeloma - neoplastic proliferation of plasma cells.
- Symptoms: Bone pain, fatigue, renal dysfunction, and possible hypercalcemia.
Urinalysis Findings
- Expected Results: Trace proteins, 4+ blood, and oval fat bodies (answer B).
Management Considerations
- Evaluate Symptoms: Identify underlying causes.
- Manage Complications: Address hyperviscosity syndrome, renal impairment, and skeletal issues.
Clinical Trial Fundamentals
Overview
A study evaluates a new stent requiring no antiplatelet therapy for myocardial infarction patients with contraindications.
Key Concepts
- Objective: Assess safety of new interventions in a Phase 1 trial.
- Correct Answer: Safety (answer E) - primary focus in early trials.
- Importance of Informed Consent: Discuss trial risks and expectations with participants.
Rheumatoid Arthritis Diagnosis
Case Overview
A 32-year-old woman experiences ankle pain and swelling, no trauma history.
Key Points
- Diagnosis Workup: Initial step should be anti-CCP antibody test (answer A).
- Understanding RA: Characterized by symmetric joint involvement, early detection aids better management.
Exclusion of Other Conditions
- Joint aspiration is more appropriate if septic arthritis is suspected or in acute scenarios.
Hypercholesterolemia Assessment
Case Summary
A 57-year-old woman presents for a routine exam; labs show increased cholesterol.
Key Points
- Diagnosis: Consider hypothyroidism as a potential cause (answer E).
- Testing: TSH measurement can help evaluate thyroid function.
Incorrect Choices Explained
- Other tests (hormones, inflammatory markers) unlikely to be relevant at this stage.
Root Cause Analysis in Healthcare
Incident Overview
A 2-year-old boy developed apnea post-surgery due to excessive morphine.
Key Concepts
- Importance: Identifying system-level issues through root cause analysis (answer A).
- Focus on Systems: Avoid blaming individuals; assess overall protocols and practices.
Diagnosing Bronchiectasis
Case Summary
A 57-year-old man reports chronic cough and blood in sputum.
Key Points
- Diagnosis: Likely bronchiectasis (answer B) due to infectious history.
- Management: Clinical evaluation with CT scan to confirm.
Appendicitis Treatment Protocol
Patient Overview
An 8-year-old boy with worsening abdominal pain.
Key Points
- Diagnosis: Clear signs of appendicitis indicating need for surgical intervention (answer C).
- Management: Initiate IV fluids and antibiotics, prepare for appendectomy.
Management of Urticaria
Patient Overview
A 47-year-old woman presents with an itchy rash after returning from vacation.
Key Points
- Diagnosis: Likely allergic urticaria; treat with antihistamine (answer E).
- Follow-up Care: Consider identifying triggers for long-term management.
Identifying Dyslexia
Case Overview
A 7-year-old boy shows disruptive behavior linked to reading difficulties.
Key Points
- Diagnosis: Dyslexia confirmed as learning disability (answer C).
- Management: Educational interventions essential for improving literacy skills.
Vesicovaginal Fistula Diagnosis
Patient Overview
A 42-year-old woman presents with urinary leakage following surgery.
Key Points
- Diagnosis: Likely bladder injury (answer A).
- Management Plan: Surgical correction; assess for urine in the vaginal canal.
Calculating NNT
Overview
A 72-year-old woman found to have carotid stenosis.
Key Points
- NNT: 20 (answer D); calculate using absolute risk reduction.
- Importance: Understand this measure to evaluate intervention effectiveness.
Primary Dysmenorrhea Treatment
Patient Overview
A 17-year-old girl with severe menstrual cramps.
Key Points
- Diagnosis: Primary dysmenorrhea confirmed; initiate oral contraceptive therapy (answer D).
- Management: Address symptoms with NSAIDs and lifestyle adjustments.
Subdural Hematoma Investigation
Patient Overview
An 87-year-old man with confusion and bruising.
Key Points
- Diagnosis: Suspected subdural hematoma; first step is a CT scan (answer D).
- Management: Address possible interventions to relieve intracranial pressure.
Evaluation of Flatfoot
Patient Overview
A 52-year-old woman shows signs of pes planus.
Key Points
- Diagnosis: Flexible flatfoot observed; no immediate further investigation needed (answer E).
- Management: Use of orthotics as primary intervention.
Temporal Arteritis Management
Patient Overview
An 80-year-old woman with transient vision loss and headaches.
Key Points
- Diagnosis: Temporal arteritis; start prednisone immediately (answer E).
- Management: Monitor for complications; urgency in treatment to prevent vision loss.
End-of-Life Decision-Making
Patient Overview
A 91-year-old man in asystole who has a DNI order.
Key Points
- Approach: Inform family about the patient’s circumstances (answer A).
- Legal and Ethical Considerations: Follow advance directives; CPR not indicated.
Peripheral Vascular Disease Management
Case Overview
A 57-year-old man with absent pulses and ABI indicating PVD.
Key Points
- Management: Start aspirin therapy for prevention (answer B).
- Secondary Prevention: Importance of smoking cessation and statin therapy.