In a clinical scenario of a 17-year-old female with loss of consciousness during exercise, excessive heat can lead to _______ characterized by symptoms such as exercise intolerance and increased core body temperature.
Heat exhaustion can occur under conditions of high ambient temperature and _______, especially during strenuous exercise, particularly in individuals with _______.
When managing heat-related illnesses such as heat exhaustion, the primary treatment involves _______ and initiating cooling measures like immersion in cool water.
In diagnosing heat exhaustion versus heat stroke, note that heat stroke presents with _______ and hyperthermia, while heat exhaustion does not typically present with neurologic disturbances.
Laboratory findings in heat-related illnesses may include _______, _______, and _______, along with increased serum creatinine and blood urea nitrogen.
An important anchor in this clinical scenario is the presence of _______ leading to potential heat-related illnesses in adolescents.
In young patients presenting with symptoms following exercise in hot conditions, consider _______ before diagnosing conditions like syncope or drug use.
Heat exhaustion can occur during strenuous exercise in _______ and increased _______.
Symptoms of heat exhaustion include _______, increased core body temperature, and the absence of _______.
Heat stroke is characterized by _______, altered mental status, and _______.
The management of heat-related illness involves _______ the individual from the heat and initiating _______.
Laboratory studies in heat-related illnesses may show _______, _______, and _______.
Congestive heart failure is unlikely in a previously healthy teenager and would present with signs such as _______ and _______.
Vasovagal syncope is characterized by a decrease in _______, preload, and cardiac output, resulting in an abrupt drop in _______.
Illicit drug use can present with symptoms like _______ and increased body temperature, especially with sympathomimetics.
Heat exhaustion is more likely in patients who present with a history of _______ in hot conditions compared to sepsis, which would have _______.
Heat-related illness management includes _______ in cool water or _______.
The signs and symptoms of rapidly progressive dementia and ataxia are consistent with a diagnosis of _______ (CJD).
In Creutzfeldt-Jakob disease, a key symptom includes _______.
Patients with Creutzfeldt-Jakob disease present with neuropsychiatric symptoms including _______, _______, and _______.
A probable diagnosis of Creutzfeldt-Jakob disease can be made through clinical evaluation and _______.
Confirmatory diagnosis of Creutzfeldt-Jakob disease is achieved through _______ showing spongiform degeneration.
The expected prognosis for patients with Creutzfeldt-Jakob disease typically leads to death within _______.
Management for Creutzfeldt-Jakob disease is primarily _______, including hospice evaluation and education.
The clinical scenario of a 72-year-old man with forgetfulness, jerking movements, and failure to recognize his wife might suggest a rapid dementia diagnosis like _______.
The presence of both neuropsychiatric symptoms and ataxia in a 72-year-old patient is indicative of _______.
The signs and symptoms consistent with _______ include rapidly progressive dementia and ataxia.
CJD is a human prion disease where prion proteins cause neurotoxicity, leading to cognitive issues such as _______, _______, and _______.
A probable diagnosis of CJD can be made through clinical observation and _______.
The _______ for CJD is mostly supportive, focusing on hospice evaluation and managing symptoms like myoclonus.
In Alzheimer's type dementia, cognitive decline begins with _______ and progresses to diverse cognitive deficits over several years.
Frontotemporal dementia is characterized by atrophy of the _______ and temporal lobes, affecting social behavior and personality.
Dementia with Lewy bodies is associated with cognitive fluctuations and _______.
Subdural hematoma (SDH) may present with symptoms like _______ and _______, along with upper motoneuron findings.
Rapidly progressive dementia alongside myoclonus is indicative of _______ rather than other types of dementia.
In severe cases, a subdural hematoma can compress the brain, leading to _______ and signs of increased intracranial pressure.
The diagnosis of _______ is confirmed by showing spongiform degeneration of the cortex, and treatment is supportive (e.g., hospice evaluation).
Dementia, _______, starts with short-term memory impairment and progresses to decline in visuospatial abilities and apraxia over years.
Dementia, _______ type is characterized by atrophy of the frontal and temporal lobes and causes deficits in social behavior or personality.
Dementia, _______ type is associated with cognitive fluctuations, visual hallucinations, and REM sleep behavior disorder, with cognitive deficits developing over years.
In a _______, symptoms may include headaches, vomiting, and evidence of upper motoneuron findings, while myoclonus is atypical.
Wernicke-Korsakoff syndrome, linked to chronic _______ use disorder, displays altered mental status, ophthalmoplegia, and ataxia, but myoclonus is uncommon.
The clinical finding of _______ is typical of Creutzfeldt-Jakob disease and atypical in other dementia types listed.
Rapidly progressive dementia and neuropsychiatric symptoms are indicative of _______.
In cases of thalamic glioma, _______ and rapidly progressive dementia would be atypical findings.
_______ in dementia should be expected to develop over years, contrary to the rapid progression seen in prion diseases.
Clinical decisions regarding dementia diagnosis should consider the absence of _______ and myoclonus in typical presentations.
In the context of a positive Chlamydia trachomatis test result for a 37-year-old woman, the concept of _______ (PPV) refers to the probability that the patient actually has the infection given a positive test result.
Positive predictive value (PPV) is calculated as _______.
The prevalence of a disease impacts its _______; as prevalence increases, PPV _______.
If the prevalence of Chlamydia trachomatis infection in the patient's age group is less than 1%, this might lead to a higher probability of a _______ result.
The patient’s partner’s fidelity and a mutually monogamous relationship can contribute to a clinical judgment regarding the result being a _______.
The definitions of positive predictive value and negative predictive value highlight that PPV varies _______ with disease prevalence, while NPV varies _______.
Given the woman's positive test result, the physician’s response focused on _______, which provides an explanation of her test results in this context.
In a clinical scenario, if test sensitivity is 80% and specificity is 97%, one must consider these values when assessing the _______ of the Chlamydia trachomatis test.
The quality of a diagnostic test is assessed by its _______.
Positive predictive value (PPV) is defined as _______.
Negative predictive value (NPV) is defined as _______.
The positive predictive value (PPV) varies _______ with disease prevalence, while negative predictive value (NPV) varies _______ with prevalence.
To interpret the PPV of a diagnostic test, one must know the _______ of the disease.
The probability of a patient having the disease given a positive test result is measured by _______.
Accuracy of a test is the proportion of all test results that are correct, calculated as _______.
The ratio of false negatives to true negatives is known as the _______.
Positive likelihood ratio is calculated as the ratio of _______ to _______.
The likelihood ratio of >1 indicates that a positive result is more likely to be a _______ than a _______.
Despite a low pretest probability, a patient may still have a high likelihood of a _______ result on a test.
A clinical decision requiring interpretation of test outcomes must utilize PPV when a patient receives a _______.
The measure of probability that a patient does not have the disease given a negative test is the _______.
The importance of _______ in tests helps to clarify the clinical decision-making process.
In evaluating a diagnostic test, knowing the _______ is critical to interpret the results appropriately.
In the management of a pediatric patient with symptomatic narrow complex _______, the best next step is _______.
Symptoms of _______ in infants may include rapid breathing, sweating, pallor, and increased fussiness.
In children with SVT, if _______ fails, the next treatment option is _______.
The normal heart rate for infants under 1 year is typically above _______ beats per minute.
For rapid heart rates like in SVT, pediatric patients may also benefit from _______ to induce AV nodal blockade.
A prolonged _______ in infants with SVT may indicate potential hemodynamic instability.
In managing _______, the first-line treatment is _______.
Supraventricular tachycardia is characterized by _______ of rapid, narrow-complex tachycardia, often occurring in _______ and _______.
In SVT, AV nodal blockade via adenosine leads to cellular _______ and reduced transmission of _______.
If _______ fails in SVT management, the next step may be _______.
Vagal maneuvers like placing an _______ over the eyes can help induce AV nodal blockade in children with SVT.
Echocardiography is not the immediate management step for patients with _______; it is used to evaluate structural heart disease after acute management.
Intravenous _______ is not appropriate for the treatment of supraventricular tachycardia; it is used for _______ and _______.
The incorrect choice for treating SVT with interventions includes options like 24-hour _______ which is not suitable for already-diagnosed patients.
If vagal maneuvers and adenosine fail, one can use _______ as a second-line agent to abort the tachyarrhythmia.
Intravenous adenosine acts on the _______, which is a G protein-coupled receptor that signals through _______.
Symptoms and acute management considerations for _______ should be understood for effective patient care in pediatrics.
The drug most likely causing the blurred vision in the 67-year-old woman is _______. It can lead to optic neuropathy, which presents as blurred vision and color vision changes.
In patients treated for _______, the adverse effect of blurred vision can indicate the presence of ocular toxicity from a first-line agent.
When treating _______, using Ethambutol is important but requires careful monitoring for complications like _______.
Symptoms such as decreased visual acuity and red-green color blindness indicate adverse effects of _______. Discontinuation of the drug is necessary.
For a patient with tuberculosis, it is critical to monitor for _______ when prescribing Ethambutol to avoid permanent vision changes.
Adverse effects of Ethambutol include optic neuropathy, which can manifest as blurred vision and decreased _______.
The primary organism that causes tuberculosis is _______. Infection occurs through inhalation of aerosol droplets containing the bacteria.
Tuberculosis can present as primary disease or _______ with risk for reactivation.
Effective treatment for tuberculosis requires a _______ due to high rates of resistance.
Ethambutol, used in tuberculosis treatment, primarily acts by inhibiting _______.
Major adverse effects of ethambutol include _______, _______, and _______.
Optic neuropathy from ethambutol may present with decreased visual acuity or _______.
Isoniazid, a first-line drug for tuberculosis, acts by inhibiting synthesis of _______ in cell walls of acid-fast bacteria.
Primary adverse effects of isoniazid include _______, _______, and _______.
Pyrazinamide, another first-line agent for tuberculosis, has an _______.
Rifampin increases the activity of _______ in the liver and may cause bodily fluids to exhibit an _______.
Discontinuation of ethambutol is indicated if there is the presence of _______.
Corticosteroids like prednisone may be used in treating _______ to reduce cerebral inflammation.
Major adverse effects of corticosteroids include _______ and _______.
The presence of hepatic toxicity and hyperuricemia may be associated with the use of _______ in tuberculosis treatment.
The adverse effects of isoniazid necessitate concurrent administration of _______ to prevent peripheral neuropathy.
Ethambutol is a first-line antimycobacterial agent commonly used in treatment regimens for _______. Major toxicities include optic neuropathy.
Correct Answer: A. Managing tuberculosis effectively includes understanding the role of _______ and recognizing potential toxicities.
In the context of alcoholic cirrhosis, the most appropriate screening test for portal hypertension is _______.
Patients with liver cirrhosis should be screened for esophageal varices via _______ due to risks of rapid and life-threatening bleeding.
Portal hypertension is a common complication of liver cirrhosis resulting from increased resistance due to _______ of hepatic sinusoids.
The portal vein is formed at the confluence of the _______, _______, and _______.
Manifestations of portal hypertension may include _______, _______, and _______.
Routine screening with colonoscopy for colorectal cancer typically begins at age _______ unless additional risk factors are present.
In patients with cirrhosis, the screening for varices should not be replaced by _______, as it is not appropriate in this context.
Portal hypertension (PH) is a common complication of _______. It results from increased resistance to blood flow through the _______ due to obliteration of hepatic sinusoids.
The portal vein begins at the confluence of the _______, _______, and _______.
Manifestations of portal hypertension include _______, _______, _______, _______, _______, and _______.
Esophageal varices can erode through the mucosa causing _______.
Routine screening for varices with _______ is recommended for patients with cirrhosis due to the risk of _______.
Screening for colorectal cancer is typically started at age _______ unless risk factors exist, such as _______ or _______.
Increased serum ammonia concentration is useful for diagnosing _______ but is not routine for alcoholic cirrhosis.
Measuring serum ferritin is essential for diagnosing _______ but is not necessary without it in cirrhosis patients.
The serum CA 19-9 assay is primarily used for diagnosing and monitoring treatment in _______ such as _______.
Cirrhosis increases the risk of developing _______, the most common primary liver cancer.
Portal hypertension can lead to _______ that may cause esophageal and gastric varices.
Cirrhosis can cause complications such as _______ and _______ as a result of portal hypertension.
In a case of a 19-year-old unrestrained driver involved in a motor vehicle collision with signs of shortness of breath, the most likely diagnosis is _______.
Signs of _______ include tachycardia, hypotension, hypoxia, jugular venous distension, and tracheal deviation.
The immediate management for acute tension pneumothorax involves _______ followed by _______.
Pneumothorax can result from air entering the intrapleural space due to either external sources like rib fractures or internal sources such as _______.
In the context of a motor vehicle collision, hypoxia and shortness of breath with _______ is more indicative of pneumothorax than aortic dissection.
The clinical symptoms of pneumothorax include _______, _______ to percussion, and respiratory distress.
In the event of a pneumothorax, _______ is the best immediate step to relieve pressure before performing further interventions.
Pneumothorax results from air entering the intrapleural space from either an external (e.g., stab wound) or internal source (e.g., _______).
Signs of tension pneumothorax include _______, _______, and _______.
In cases of acute tension pneumothorax, _______ followed by _______ is the management strategy.
Hypoxia and shortness of breath are more consistent with _______ than aortic dissection, which may show a _______ on chest x-ray.
Aortic dissection presents with _______, _______, and _______.
Clavicular fractures can occur in blunt trauma but do not cause _______ unless accompanied by pneumothorax.
Esophageal rupture, often due to trauma, can present with _______ and _______.
Pericardial hemorrhage is more likely after penetrating chest trauma and can progress to _______.
_______ occurs when air enters and is trapped in the pleural space, leading to lung collapse and mediastinal mass effect.
Management of tension pneumothorax involves _______ to relieve pressure before _______.
Signs of aortic dissection include _______, _______, and _______.
Patients with atypical presentation of chest trauma can show _______ due to underlying _______.
In the clinical scenario involving a 67-year-old woman with severe upper abdominal pain, the most likely diagnosis following trauma is _______.
For a patient presenting with acute abdominal pain after blunt trauma, elevated serum levels of _______ and _______ are indicative of _______.
When evaluating abdominal pain after trauma, if bowel sounds are _______, consider the possibility of _______ such as _______.
In the context of an unstable trauma patient with abdominal tenderness, a high pulse rate of _______ may indicate severe _______ or internal bleeding leading to _______.
In trauma cases, the initial assessment of a patient's vital signs, including _______ of 150/60 mm Hg, is crucial to determining the extent of _______.
An elderly woman with abdominal trauma and elevated amylase levels should be evaluated for potential _______, specifically _______.
Increased serum _______ and _______ activity is commonly seen in acute pancreatitis.
Acute pancreatitis presents with severe _______ that radiates to the _______.
Acute pancreatitis can be complicated by _______, _______, _______, or the formation of _______.
Treatment of uncomplicated acute pancreatitis includes _______, _______, and _______.
Gallstone impaction may cause acute pancreatitis but requires a history of _______ for diagnosis, making _______ more likely in this scenario.
Intestinal contusion is difficult to diagnose as it often does not cause any laboratory abnormalities and is typically _______ on a CT scan.
Liver or splenic laceration can present with abdominal pain and _______ but typically shows localized tenderness in the _______ or _______ upper quadrant.
The educational objective regarding acute pancreatitis is that it can be caused by _______ and typically presents with _______, nausea, and vomiting.
Laboratory studies commonly show increased serum _______ and _______ concentrations in patients with acute pancreatitis.
In evaluating the association between cigarette smoking and cardiovascular disease, researchers identified a _______. This means that as the number of cigarettes smoked daily increases, so does the _______.
Observational studies can demonstrate correlation but cannot establish _______. Only _______ can verify causation.
The Bradford Hill criteria for causality include _______, _______, _______, _______, and _______.
In the context of smoking and cardiovascular disease, the number of cigarettes smoked is the _______ and the resulting risk for cardiovascular disease is considered the _______.
If an association can be explained by a known biologic pathway, it has _______. This is crucial in determining causality.
Which of the following is best represented by the correlation between daily cigarette smoking and cardiovascular disease? _______.
In observational studies, the strength of the association can suggest causality, especially when combined with other criteria like _______.
The presence of a _______ in a study suggests a correlation between two variables, such as the number of _______ daily and the increased risk for _______.
When assessing causality, a correlation is more likely to represent causation if there is increased _______ and a _______.
In observational studies, the _______ implies a one-to-one relationship between exposure and outcome, but in this study, it cannot be determined because _______ is associated with multiple diseases.
If an observed association can be explained by a known _______, it is said to have _______.
A correlation coefficient r indicates the strength of an association, with _______ showing no correlation, and _______ indicating a perfectly positive correlation.
A _______ exists if the exposure precedes the outcome, which in this case is uncertain for _______ and _______.
Despite the presence of a dose-response relationship, true _______ cannot be determined solely by an _______.
An example of increased _______ for cardiovascular disease is seen when correlating the number of _______ smoked daily with the likelihood of developing the disease.
In research, the _______ increases the likelihood that correlation represents causation, particularly in the case of smoking and cardiovascular disease.
In adults, a PPD skin test is considered positive at _______ of induration under general guidelines.
Latent tuberculosis infection (LTBI) is indicated by a positive PPD skin test or IGRA in the absence of _______ with Mycobacterium tuberculosis.
The most appropriate next step in management for a patient with a PPD induration of _______ is _______.
Patients exposed to high-risk situations may have a positive PPD at indurations of _______ or greater.
Prior BCG vaccination can cause a false-positive PPD, but this effect typically wanes within _______.
Chest x-ray is used to _______ before initiating therapy for latent tuberculosis infection.
Common regimens for LTBI treatment include _______ of isoniazid therapy.
For patients with a 15 mm induration on a PPD skin test, the best next step in management is _______.
Latent tuberculosis infection (LTBI) is defined as a positive PPD skin test or interferon gamma release assay (IGRA) in the absence of _______ with Mycobacterium tuberculosis (MTB).
Patients with HIV have a positive PPD skin test if the induration is at or above _______; while the general population is positive if the induration is _______ or greater.
Health care workers are often considered to have a positive PPD skin test at an induration of _______.
Before initiating therapy for LTBI, it is essential to exclude active infection with a _______.
In cases of LTBI, a common treatment regimen is _______.
Repeat PPD skin test for a patient with a positive result is _______ and delays treatment.
Patients diagnosed with LTBI should be treated even if they received the _______, as immunity wanes after about 5 years.
Sputum cultures for acid-fast bacilli are indicated for patients suspected of having _______.
A 76-year-old woman with pneumonia develops a parapneumonic effusion. The most appropriate next step in management is _______.
In the treatment of empyema, the diagnosis usually requires _______ to sample the pleural fluid.
Empyema is defined by bacterial infection of the _______.
When treating empyema, fluid with a glucose concentration less than 40 mg/dL or a pH of less than _______ supports the diagnosis.
In patients with empyema, injecting _______ and recombinant DNase through the chest tube can aid resolution of the infection.
In the management of empyema following community-acquired pneumonia, the best next step is the placement of a _______ for drainage.
Empyema is defined as a _______ of the pleural space that can develop as a complication of pneumonia.
The diagnosis of empyema typically requires _______ to sample pleural fluid.
Pleural fluid in empyema often shows _______, an increased leukocyte count, decreased glucose concentration, and a pH of less than 7.2.
For the treatment of empyema, a chest tube is preferred, and therapy is optimized with intravenous _______ targeting the implicated organism.
If chest tube insertion fails to resolve empyema, _______ may be required for drainage.
A CT scan of the chest is typically _______ to diagnose empyema and may delay necessary interventions.
Intravenous _______ is indicated for hypervolemia and pulmonary edema, but not for empyema management.
Intubation and mechanical ventilation are reserved for patients with respiratory failure, not typically needed for those who are _______ and stable.
Pleurodesis is reserved for patients with _______ or pneumothoraces, not empyema.
An empyema's clinical management emphasizes drainage through _______ due to the ineffectiveness of antibiotics alone.
In a patient with _______, the most appropriate next step in management is _______.
Carpal tunnel syndrome results from compression of the _______ within the carpal tunnel and presents with pain, weakness, and _______.
Positive provocative test maneuvers for carpal tunnel syndrome include the _______ test and the _______ test.
In the case of carpal tunnel syndrome, patients with mild symptoms can be treated conservatively with _______ and ergonomic changes.
When symptoms of carpal tunnel syndrome are severe or persistent, the patient may require _______.
A _______ Spurling test suggests that the patient's shoulder examination is normal and her neurological complaints localize to the carpal tunnel.
In the case scenario, the patient is a _______ with type 2 diabetes mellitus presenting with pain and swelling in her _______.
Patients with carpal tunnel syndrome who type for long periods may benefit from ergonomic changes, such as _______.
Carpal tunnel syndrome results from _______ of the _______ within the carpal tunnel and presents with signs and symptoms including _______, _______, and _______ of the first three digits.
The most appropriate next step in management for a patient with mild carpal tunnel syndrome is the use of a computer keyboard with a _______.
Patients with mild carpal tunnel syndrome may be treated conservatively with wrist splinting and _______.
The Tinel and Phalen tests are _______ used to diagnose carpal tunnel syndrome.
For carpal tunnel syndrome, if symptoms persist or are severe, surgical _______ of the carpal tunnel may be required.
MRI of the right shoulder is unlikely to provide meaningful diagnostic information because the patient's symptoms localize to the _______.
Oral hydrocodone is unnecessary for carpal tunnel syndrome because opiates are generally _______ and potentially _______.
In the case of the patient with severe right-sided chest pain, shortness of breath, and dizziness, the strongest predisposing risk factor for in-hospital mortality is _______.
Pulmonary embolism (PE) can be diagnosed definitively with a _______ that uses intravenous contrast to opacify the _______.
Risk factors for the development of a pulmonary embolism include the presence of a _______ and factors such as being _______ or recently undergoing _______.
In assessing in-hospital mortality risk, advanced age is noted as a major factor while _______ is another significant risk factor to consider.
A positive _______ during left calf examination suggests the presence of a _______.
Treatment of deep vein thrombosis or pulmonary embolism typically involves systemic _______.
In evaluating a patient with signs of DVT, clinical findings like calf tenderness and positive _______ are important for diagnosis.
In patients who have recently traveled in _______ or cars for an extended period of time, the risk of developing a _______ increases significantly.
The patient's BMI of _______ classifies her as underweight, which can be a component of evaluating overall health status in hospital settings.
In-hospital mortality risk for patients with signs of _______ and _______ is significantly increased by _______.
Pulmonary embolism can be definitively diagnosed with a _______ timed to opacify the _______.
Risk factors for the development of PE include the presence of a _______ and factors like _______ and the use of _______.
Treatment for DVT or PE involves the use of _______.
While _______ can indicate health status, it is not definitive for evaluating mortality in patients showing signs of obstructive shock when compared to _______.
A positive _______ and calf tenderness are indicators that can help diagnose _______, but they are not prognostic.
Patients with lower extremity swelling suggestive of DVT may also experience _______; however, it is not necessarily indicative of the severity of their illness.
Elderly patients with DVT or PE may have a _______ as a potentially positive prognostic indicator despite being at risk for _______.
Risk factors for in-hospital mortality include _______ and _______.
Common symptoms of _______ include _______, _______, and _______.
The core concept in managing DVT/PE includes understanding the importance of _______ and appropriate use of _______.
In evaluating a pediatric patient with hypertension, the next best step is _______.
Secondary hypertension in pediatrics can be caused by conditions such as _______ and _______.
Typical initial tests for evaluating secondary hypertension in children include _______ and _______ levels.
Primary hypertension is more common in _______ who are overweight or obese, but less common in _______.
If adults are on three or more antihypertensives including a diuretic, they should be assessed for _______.
The assessment of blood flow velocity in the renal arteries is critical for diagnosing _______.
In pediatric patients, the next most appropriate step for evaluating hypertension is _______. This is important for detecting _______ caused by underlying conditions.
Secondary hypertension can result from various conditions, including _______, _______, and _______.
Typical initial tests for evaluating secondary hypertension in children include measuring _______ and _______ levels.
In pediatric patients, hypertension evaluation should focus on potential underlying causes rather than just being assumed as _______.
Adult patients on three or more antihypertensive medications should be evaluated for _______, just as pediatric patients should.
Renovascular hypertension is diagnosed by assessing the _______ through the renal arteries using Doppler imaging.
Treatment options for renal artery stenosis may include _______.
Measurement of _______ is typically not relevant for diagnosing hypertension in children.
Polysomnography is not commonly used in pediatric patients for hypertension unless there's an indication of _______ related to anatomical abnormalities.
Thyroid function tests are not the first line for hypertension evaluation, though _______ can be related to increased blood pressure.
The educational objective emphasizes that renal artery stenosis can cause secondary hypertension and is diagnosed via renal ultrasonography with Doppler to assess _______.
Opioid intoxication can cause a decreased level of consciousness due to its effects as a _______. It may lead to sedation, bradycardia, depressed respiratory drive, and _______.
In cases of suspected opioid intoxication, the patient's vital signs may show _______ and respiratory rates as low as _______.
The typical pupil response in opioid intoxication is _______, which is less common in other neurologic conditions.
When assessing a 57-year-old woman with a history of chronic back pain and diabetes who is unresponsive, consider _______ as a primary cause of altered mental status.
Opioids interact with several neurotransmitter systems in the CNS, leading to effects such as altered mental status, sedation, and _______.
In the context of increased opioid use, consider the patient's medication history, including long-term use of _______ and _______.
The Glasgow Coma Scale score may decrease significantly during _______, suggesting severe CNS depression.
Regular use of analgesics like ketorolac may inadvertently lead to decreased kidney function, worsening symptoms in cases of opioid toxicity, such as in the patient's case with _______.
Opioid intoxication leads to symptoms such as _______, _______, and _______. This patient's condition shows decreased purposefulness and may lead to _______.
A distinctive finding of opioid intoxication is _______, caused by direct opioid receptor activity in brain areas responsible for pupillary control.
In cases of acute opioid intoxication, the best next step in management is to administer _______, a short-acting opioid antagonist.
Chronic subdural hematoma commonly presents with _______ and _______, particularly in elderly patients.
The symptoms of Conversion disorder include neurologic symptoms such as _______ that are not explained by objective findings. This is in contrast to the signs seen in opioid intoxication.
Hypertensive encephalopathy may present with symptoms such as headache, but would not typically include _______ or _______ seen in opioid intoxication.
In cases of hypoglycemia, symptoms can include _______ and _______, contrasting with the _______ associated with opioid intoxication.
Opioids act throughout the CNS and peripheral nervous system, leading to effects such as reduced gut motility and thus causing _______.
A patient with decreased kidney function may experience _______ due to reduced clearance of opioids.
Direct opioid receptor activity in brain areas responsible for pupillary control typically causes _______, which is distinctive in opioid intoxication.
The key management step in acute poisoning from opioids is the administration of _______, which can prevent _______.
Opioid intoxication causes symptoms of CNS depression, including _______, _______, _______, and _______. Miosis differentiates opioid intoxication from other neurologic conditions.
In the case of acute opioid intoxication, the best next step is administering _______, a short-acting opioid antagonist, to prevent respiratory collapse.
_______ refers to gradual blood accumulation between the dura and arachnoid membranes, commonly in elderly patients.
_______ involves neurologic symptoms not fully explained by objective findings on examination or imaging, such as sensory or motor dysfunction.
Hypertensive encephalopathy may lead to symptoms like headache, vomiting, and altered mental status when blood pressure is greater than _______.
Patients with _______ may show symptoms such as tremors, palpitations, and cognitive impairment, while bradypnea and miosis are atypical.
A _______ leads to subarachnoid hemorrhage, presenting with severe headache, nausea, vomiting, and potentially coma.
Status epilepticus is defined as continuous epileptic activity for at least _______ or at least two seizures with incomplete recovery of consciousness.
In a patient on total parenteral nutrition (TPN) with new onset fever and leukocytosis, the most appropriate next step in management is to obtain _______.
Patients on TPN through a central line are at increased risk for _______ leading to sepsis, known as _______.
In the scenario of a 51-year-old man with a proximal jejunal enterocutaneous fistula, his clinical status shows a temperature of _______ and a leukocyte count of _______.
The presence of a long-term intravenous catheter substantially increases the risk for _______ in TPN patients following _______.
When evaluating for sepsis, it is essential to draw anaerobic and aerobic _______ from two different sites, including at least one from the _______.
Following blood cultures in suspected sepsis, the next step is to start _______.
In the management of TPN-related infections, it is often recommended to _______ unless there are rare exceptions.
In a patient with new onset fever and leukocytosis on total parenteral nutrition (TPN) through a central line, the best next step in management is to obtain _______ from the _______.
The risk for _______ leading to sepsis is significantly increased in patients with a _______.
When evaluating for sepsis in patients with a central venous catheter, blood cultures should be drawn from _______, with at least one set from the _______.
In patients receiving TPN, _______ should be suspected if they present with persistent fever, especially after recent _______.
Empiric _______ should be initiated following the collection of blood cultures in a patient suspected of sepsis.
A _______ is typically performed as part of the workup for sepsis, but in the context of a central venous catheter, priority should be given to obtaining _______.
A _______ is indicated if the patient develops worsening abdominal pain or is suspected of a new _______.
Removal of the central venous catheter is recommended in almost all instances of _______, unless there are rare circumstances where it may remain in place.
If fungal elements are identified in the blood cultures of a TPN patient, initiation of _______ should be considered.
In patients on total parenteral nutrition (TPN) with a central line and new onset fever, the most appropriate next step in management is obtaining _______ from the catheter site due to the risk for _______.
Patients on TPN require evaluation for _______ and _______ when they develop new fevers and leukocytosis, especially following recent _______.
When evaluating for sepsis in a patient with a central venous catheter, at least one set of blood cultures should be obtained from the _______ and an _______.
The recommendation is to remove the _______ in almost all circumstances when a patient develops symptoms indicative of sepsis.
Following blood cultures for suspected CLABSI, the next step is to initiate _______.
If a patient on TPN has persistent fevers despite broad-spectrum antibiotic therapy, consider starting _______.
Catheter-related bloodstream infections should be suspected if a patient with a central venous catheter develops _______ and _______ without obvious alternative infection signs.
The longer a central venous catheter remains in place, the higher the risk for _______.
If a patient's abdominal examination is benign and they develop a fever while on TPN, a _______ is not indicated unless they show signs of new intra-abdominal infection.
An exploratory laparotomy for resection of a fistula would only be indicated if there was clear evidence of peritonitis, which is not present in this patient's examination due to _______.
The study investigating patients with type 2 diabetes mellitus used discussions led by moderators to examine attitudes. This design is best described as _______. 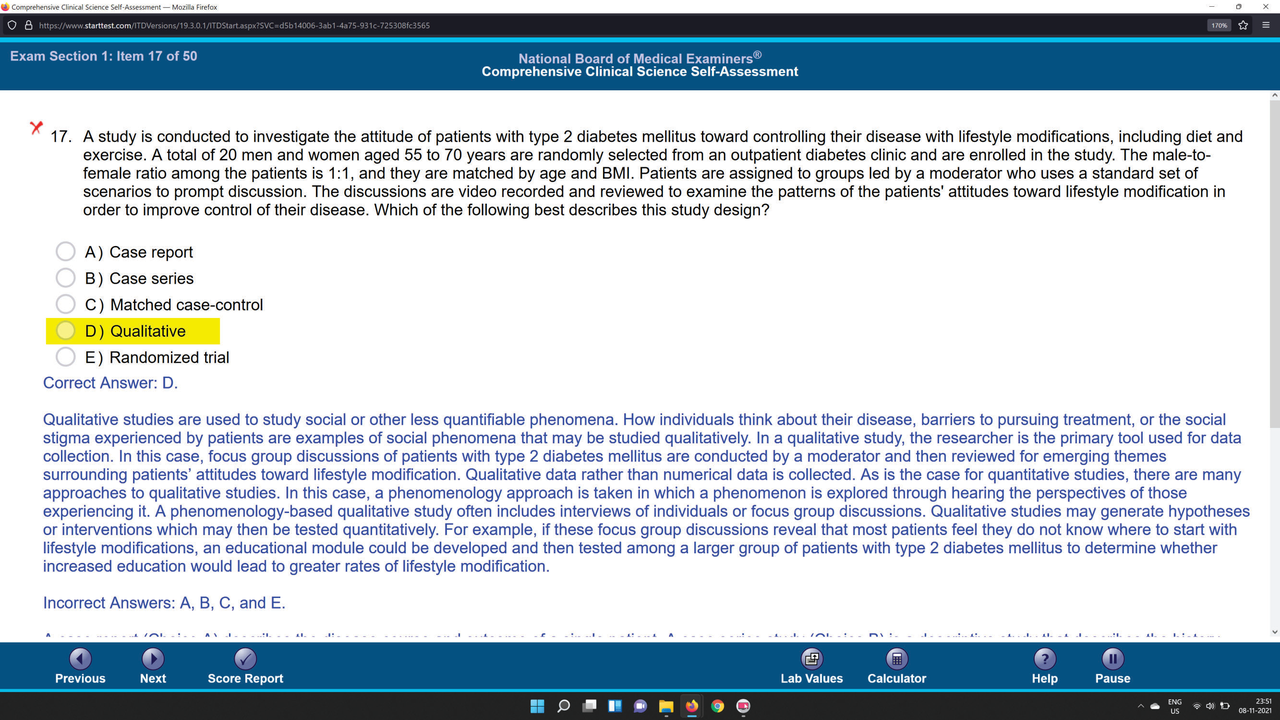
In the study, qualitative data was collected through _______ of patients with type 2 diabetes mellitus, revealing their attitudes toward lifestyle modification.
Qualitative studies, like the one on diabetes management, explore social phenomena, such as _______ and _______.
The phenomenology approach in qualitative research, used in this diabetes study, focuses on understanding perspectives through _______ or _______.
If focus group discussions reveal that patients with diabetes feel lost regarding lifestyle modifications, what could be developed to assist them? An _______ could be created and tested quantitatively.
Qualitative studies are used to study social phenomena such as how individuals think about their _______, barriers to pursuing treatment, or the _______ experienced by patients.
In qualitative studies, _______ and interviews are often used to gather data about patients' attitudes toward _______.
The _______ approach in qualitative studies explores a phenomenon by hearing the perspectives of those experiencing it, often through _______.
If focus group discussions reveal that patients don't know where to start with lifestyle modifications, an educational module could be developed and tested among patients with _______.
A case report describes the disease course and outcome of a _______, while a case series study talks about a group of patients with a similar _______.
Matched case-control studies compare a group of patients with an outcome ({c1::cases}}) to a second matched group without that outcome (_______) to identify associated exposures.
A _______ is a prospective interventional study where patients are randomly assigned to receive an intervention compared to _______ or standard therapy.
Qualitative studies may generate _______ or interventions that can then be tested _______.
Educational Objective: Qualitative studies explore phenomena such as how individuals think about their disease, barriers to treatment, and _______ experienced by patients.

In unstable trauma patients with signs of hypotension, tachycardia, and distant heart sounds, the most appropriate next step in management is _______.
A patient with penetrating chest trauma presenting with hypotension may be experiencing _______.
Characteristic findings on echocardiography for pericardial tamponade include collapse of the _______ and _______ during diastole.
In cases of hypotensive trauma, it is crucial to establish _______ and begin resuscitation before diagnostic imaging.
The patient in this scenario consumed six 12-oz beers and used cocaine, which may contribute to their _______ and hemodynamic instability.
The vital signs of a patient with pericardial tamponade often include _______ and _______.
The appropriate management for suspected cardiac tamponade includes _______ or creating a _______.
The stab wound is located _______ in this case of traumatic chest injury.
In unstable trauma patients presenting with hypotension and distant heart sounds, the most appropriate next step in diagnosis is _______.
Characteristic findings on echocardiography for cardiac tamponade include _______, _______, and _______.
During cardiac tamponade, the patient may experience _______, decreased _______, and decreased _______.
In hypotensive trauma patients, a _______ is useful to evaluate for cardiac tamponade as well as _______, _______, and _______.
It is critical to establish _______ and provide immediate _______ before any diagnostics in unstable patients.
In patients with tension pneumothorax, placement of a right chest tube is most appropriate when presenting with _______, _______, and _______.
When managing a hypotensive patient with serious traumatic injuries, it is essential to stabilize before performing _______.
A schematic representation of the presentation of cardiac tamponade includes symptoms like _______, _______, and _______ to aid recognition of the condition.
In a 37-year-old man with a blood pressure of 175/97 mm Hg after dental extraction, what is the most appropriate next step in evaluation? Consider the family history of myocardial infarction at age _______ years and current smoker status. The answer is _______.
Why should lipid studies be performed in this patient? The presence of hypertension and a family history of _______ at an early age raises concern for increased cardiovascular risk.
What are considered other risk factors for _______? These include hypertension, type 2 diabetes, a positive family history, and _______.
In men aged over 35, the USPSTF recommends screening for _______ if they are at increased risk for coronary vascular disease.
What is the first-line pharmacotherapy for patients with _______? The answer is _______.
When should hemoglobin A1c be assessed? It should be checked but is less likely useful in a patient with a _______ like this 37-year-old.
What lifestyle modification can reduce risk for coronary vascular disease? Optimizing serum lipids through _______ and lifestyle changes is essential.
このデッキ内のフラッシュカード (353 枚)
-
1
In a clinical scenario of a 17-year-old female with loss of consciousness during exercise, excessive heat can lead to heat exhaustion characterized by symptoms such as exercise intolerance and increased core body temperature.
-
2
Heat exhaustion can occur under conditions of high ambient temperature and high humidity, especially during strenuous exercise, particularly in individuals with obesity.
-
3
When managing heat-related illnesses such as heat exhaustion, the primary treatment involves removing the individual from the heat and initiating cooling measures like immersion in cool water.
-
4
In diagnosing heat exhaustion versus heat stroke, note that heat stroke presents with altered mental status and hyperthermia, while heat exhaustion does not typically present with neurologic disturbances.
-
5
Laboratory findings in heat-related illnesses may include hypernatremia, hyperchloremia, and hyperkalemia, along with increased serum creatinine and blood urea nitrogen.
-
6
An important anchor in this clinical scenario is the presence of strenuous exercise leading to potential heat-related illnesses in adolescents.
-
7
In young patients presenting with symptoms following exercise in hot conditions, consider heat-related illness before diagnosing conditions like syncope or drug use.
-
8
Heat exhaustion can occur during strenuous exercise in hot temperatures and increased humidity.
-
9
Symptoms of heat exhaustion include exercise intolerance, increased core body temperature, and the absence of neurologic disturbances.
-
10
Heat stroke is characterized by hyperthermia, altered mental status, and neurologic deficits.
-
11
The management of heat-related illness involves removing the individual from the heat and initiating cooling measures.
-
12
Laboratory studies in heat-related illnesses may show hypernatremia, hyperchloremia, and hyperkalemia.
-
13
Congestive heart failure is unlikely in a previously healthy teenager and would present with signs such as cool extremities and pulmonary edema.
-
14
Vasovagal syncope is characterized by a decrease in venous return, preload, and cardiac output, resulting in an abrupt drop in mean arterial pressure.
-
15
Illicit drug use can present with symptoms like tachycardia and increased body temperature, especially with sympathomimetics.
-
16
Heat exhaustion is more likely in patients who present with a history of exertion in hot conditions compared to sepsis, which would have focal signs of infection.
-
17
Heat-related illness management includes immersion in cool water or evaporative cooling.
-
18
The signs and symptoms of rapidly progressive dementia and ataxia are consistent with a diagnosis of Creutzfeldt-Jakob disease (CJD).
-
19
In Creutzfeldt-Jakob disease, a key symptom includes spontaneous myoclonus.
-
20
Patients with Creutzfeldt-Jakob disease present with neuropsychiatric symptoms including dementia, anxiety, and behavioral disturbances.
-
21
A probable diagnosis of Creutzfeldt-Jakob disease can be made through clinical evaluation and cerebrospinal fluid analysis.
-
22
Confirmatory diagnosis of Creutzfeldt-Jakob disease is achieved through autopsy showing spongiform degeneration.
-
23
The expected prognosis for patients with Creutzfeldt-Jakob disease typically leads to death within one year.
-
24
Management for Creutzfeldt-Jakob disease is primarily supportive, including hospice evaluation and education.
-
25
The clinical scenario of a 72-year-old man with forgetfulness, jerking movements, and failure to recognize his wife might suggest a rapid dementia diagnosis like Creutzfeldt-Jakob disease.
-
26
The presence of both neuropsychiatric symptoms and ataxia in a 72-year-old patient is indicative of Creutzfeldt-Jakob disease.
-
27
The signs and symptoms consistent with Creutzfeldt-Jakob disease (CJD) include rapidly progressive dementia and ataxia.
-
28
CJD is a human prion disease where prion proteins cause neurotoxicity, leading to cognitive issues such as dementia, anxiety, and behavioral disturbances.
-
29
A probable diagnosis of CJD can be made through clinical observation and cerebrospinal fluid analysis.
-
30
The treatment for CJD is mostly supportive, focusing on hospice evaluation and managing symptoms like myoclonus.
-
31
In Alzheimer's type dementia, cognitive decline begins with short-term memory impairment and progresses to diverse cognitive deficits over several years.
-
32
Frontotemporal dementia is characterized by atrophy of the frontal and temporal lobes, affecting social behavior and personality.
-
33
Dementia with Lewy bodies is associated with cognitive fluctuations and visual hallucinations.
-
34
Subdural hematoma (SDH) may present with symptoms like headaches and vomiting, along with upper motoneuron findings.
-
35
Rapidly progressive dementia alongside myoclonus is indicative of Creutzfeldt-Jakob disease (CJD) rather than other types of dementia.
-
36
In severe cases, a subdural hematoma can compress the brain, leading to altered mental status and signs of increased intracranial pressure.
-
37
The diagnosis of Creutzfeldt-Jakob disease is confirmed by showing spongiform degeneration of the cortex, and treatment is supportive (e.g., hospice evaluation).
-
38
Dementia, Alzheimer type, starts with short-term memory impairment and progresses to decline in visuospatial abilities and apraxia over years.
-
39
Dementia, frontotemporal type is characterized by atrophy of the frontal and temporal lobes and causes deficits in social behavior or personality.
-
40
Dementia, Lewy body type is associated with cognitive fluctuations, visual hallucinations, and REM sleep behavior disorder, with cognitive deficits developing over years.
-
41
In a subdural hematoma, symptoms may include headaches, vomiting, and evidence of upper motoneuron findings, while myoclonus is atypical.
-
42
Wernicke-Korsakoff syndrome, linked to chronic alcohol use disorder, displays altered mental status, ophthalmoplegia, and ataxia, but myoclonus is uncommon.
-
43
The clinical finding of myoclonus is typical of Creutzfeldt-Jakob disease and atypical in other dementia types listed.
-
44
Rapidly progressive dementia and neuropsychiatric symptoms are indicative of Creutzfeldt-Jakob disease.
-
45
In cases of thalamic glioma, myoclonus and rapidly progressive dementia would be atypical findings.
-
46
Cognitive deficits in dementia should be expected to develop over years, contrary to the rapid progression seen in prion diseases.
-
47
Clinical decisions regarding dementia diagnosis should consider the absence of seizures and myoclonus in typical presentations.
-
48
In the context of a positive Chlamydia trachomatis test result for a 37-year-old woman, the concept of positive predictive value (PPV) refers to the probability that the patient actually has the infection given a positive test result.
-
49
Positive predictive value (PPV) is calculated as (true positives (TP)) / (TP + false positives (FP)).
-
50
The prevalence of a disease impacts its positive predictive value; as prevalence increases, PPV increases.
-
51
If the prevalence of Chlamydia trachomatis infection in the patient's age group is less than 1%, this might lead to a higher probability of a false positive result.
-
52
The patient’s partner’s fidelity and a mutually monogamous relationship can contribute to a clinical judgment regarding the result being a false positive.
-
53
The definitions of positive predictive value and negative predictive value highlight that PPV varies directly with disease prevalence, while NPV varies inversely.
-
54
Given the woman's positive test result, the physician’s response focused on positive predictive value, which provides an explanation of her test results in this context.
-
55
In a clinical scenario, if test sensitivity is 80% and specificity is 97%, one must consider these values when assessing the accuracy of the Chlamydia trachomatis test.
-
56
The quality of a diagnostic test is assessed by its sensitivity, specificity, positive predictive value, and negative predictive value.
-
57
Positive predictive value (PPV) is defined as (true positives (TP)) / (TP + false positives (FP)).
-
58
Negative predictive value (NPV) is defined as (true negatives (TN)) / (TN + false negatives (FN)).
-
59
The positive predictive value (PPV) varies directly with disease prevalence, while negative predictive value (NPV) varies inversely with prevalence.
-
60
To interpret the PPV of a diagnostic test, one must know the prevalence of the disease.
-
61
The probability of a patient having the disease given a positive test result is measured by positive predictive value (PPV).
-
62
Accuracy of a test is the proportion of all test results that are correct, calculated as (TP + TN) / total number of tests.
-
63
The ratio of false negatives to true negatives is known as the negative likelihood ratio.
-
64
Positive likelihood ratio is calculated as the ratio of TP to FP.
-
65
The likelihood ratio of >1 indicates that a positive result is more likely to be a true positive than a false positive.
-
66
Despite a low pretest probability, a patient may still have a high likelihood of a false positive result on a test.
-
67
A clinical decision requiring interpretation of test outcomes must utilize PPV when a patient receives a positive test.
-
68
The measure of probability that a patient does not have the disease given a negative test is the negative predictive value (NPV).
-
69
The importance of predictive values in tests helps to clarify the clinical decision-making process.
-
70
In evaluating a diagnostic test, knowing the prevalence is critical to interpret the results appropriately.
-
71
In the management of a pediatric patient with symptomatic narrow complex supraventricular tachycardia (SVT), the best next step is intravenous adenosine therapy.
-
72
Symptoms of supraventricular tachycardia (SVT) in infants may include rapid breathing, sweating, pallor, and increased fussiness.
-
73
In children with SVT, if adenosine fails, the next treatment option is synchronized cardioversion.
-
74
The normal heart rate for infants under 1 year is typically above 180 beats per minute.
-
75
For rapid heart rates like in SVT, pediatric patients may also benefit from vagal maneuvers to induce AV nodal blockade.
-
76
A prolonged capillary refill time in infants with SVT may indicate potential hemodynamic instability.
-
77
In managing supraventricular tachycardia (SVT), the first-line treatment is intravenous adenosine therapy.
-
78
Supraventricular tachycardia is characterized by paroxysmal episodes of rapid, narrow-complex tachycardia, often occurring in children and infants.
-
79
In SVT, AV nodal blockade via adenosine leads to cellular hyperpolarization and reduced transmission of supraventricular action potentials.
-
80
If adenosine fails in SVT management, the next step may be synchronized cardioversion.
-
81
Vagal maneuvers like placing an ice bag over the eyes can help induce AV nodal blockade in children with SVT.
-
82
Echocardiography is not the immediate management step for patients with symptomatic supraventricular tachycardia; it is used to evaluate structural heart disease after acute management.
-
83
Intravenous digoxin therapy is not appropriate for the treatment of supraventricular tachycardia; it is used for congestive heart failure and atrial fibrillation.
-
84
The incorrect choice for treating SVT with interventions includes options like 24-hour ambulatory ECG monitoring which is not suitable for already-diagnosed patients.
-
85
If vagal maneuvers and adenosine fail, one can use intravenous propranolol therapy as a second-line agent to abort the tachyarrhythmia.
-
86
Intravenous adenosine acts on the adenosine A₁ receptor, which is a G protein-coupled receptor that signals through adenylate cyclase.
-
87
Symptoms and acute management considerations for supraventricular tachycardia should be understood for effective patient care in pediatrics.
-
88
The drug most likely causing the blurred vision in the 67-year-old woman is Ethambutol. It can lead to optic neuropathy, which presents as blurred vision and color vision changes.
-
89
In patients treated for tuberculosis, the adverse effect of blurred vision can indicate the presence of ocular toxicity from a first-line agent.
-
90
When treating tuberculosis, using Ethambutol is important but requires careful monitoring for complications like optic neuropathy.
-
91
Symptoms such as decreased visual acuity and red-green color blindness indicate adverse effects of Ethambutol. Discontinuation of the drug is necessary.
-
92
For a patient with tuberculosis, it is critical to monitor for ocular toxicity when prescribing Ethambutol to avoid permanent vision changes.
-
93
Adverse effects of Ethambutol include optic neuropathy, which can manifest as blurred vision and decreased color vision.
-
94
The primary organism that causes tuberculosis is Mycobacterium tuberculosis. Infection occurs through inhalation of aerosol droplets containing the bacteria.
-
95
Tuberculosis can present as primary disease or latent infection with risk for reactivation.
-
96
Effective treatment for tuberculosis requires a multi-agent antimycobacterial regimen due to high rates of resistance.
-
97
Ethambutol, used in tuberculosis treatment, primarily acts by inhibiting mycobacterial cell wall synthesis.
-
98
Major adverse effects of ethambutol include optic neuropathy, neutropenia, and thrombocytopenia.
-
99
Optic neuropathy from ethambutol may present with decreased visual acuity or red-green color blindness.
-
100
Isoniazid, a first-line drug for tuberculosis, acts by inhibiting synthesis of mycolic acids in cell walls of acid-fast bacteria.
-
101
Primary adverse effects of isoniazid include hepatotoxicity, neurotoxicity, and vitamin B6 deficiency.
-
102
Pyrazinamide, another first-line agent for tuberculosis, has an unknown mechanism of action.
-
103
Rifampin increases the activity of cytochrome P450 enzymes in the liver and may cause bodily fluids to exhibit an orange tint.
-
104
Discontinuation of ethambutol is indicated if there is the presence of ocular toxicity.
-
105
Corticosteroids like prednisone may be used in treating tuberculous meningitis to reduce cerebral inflammation.
-
106
Major adverse effects of corticosteroids include psychosis and accelerated bone loss.
-
107
The presence of hepatic toxicity and hyperuricemia may be associated with the use of pyrazinamide in tuberculosis treatment.
-
108
The adverse effects of isoniazid necessitate concurrent administration of pyridoxine to prevent peripheral neuropathy.
-
109
Ethambutol is a first-line antimycobacterial agent commonly used in treatment regimens for tuberculosis. Major toxicities include optic neuropathy.
-
110
Correct Answer: A. Managing tuberculosis effectively includes understanding the role of multi-agent therapy and recognizing potential toxicities.
-
111
In the context of alcoholic cirrhosis, the most appropriate screening test for portal hypertension is esophagogastroduodenoscopy (EGD).
-
112
Patients with liver cirrhosis should be screened for esophageal varices via esophagogastroduodenoscopy due to risks of rapid and life-threatening bleeding.
-
113
Portal hypertension is a common complication of liver cirrhosis resulting from increased resistance due to fibrosis of hepatic sinusoids.
-
114
The portal vein is formed at the confluence of the left gastric, splenic, and superior mesenteric veins.
-
115
Manifestations of portal hypertension may include esophageal varices, splenomegaly, and ascites.
-
116
Routine screening with colonoscopy for colorectal cancer typically begins at age 50 unless additional risk factors are present.
-
117
In patients with cirrhosis, the screening for varices should not be replaced by colonoscopy, as it is not appropriate in this context.
-
118
Portal hypertension (PH) is a common complication of liver cirrhosis. It results from increased resistance to blood flow through the portal venous system due to obliteration of hepatic sinusoids.
-
119
The portal vein begins at the confluence of the left gastric, splenic, and superior mesenteric veins.
-
120
Manifestations of portal hypertension include esophageal varices, gastric varices, caput medusae, hemorrhoids, splenomegaly, and ascites.
-
121
Esophageal varices can erode through the mucosa causing rapid, life-threatening bleeding.
-
122
Routine screening for varices with esophagogastroduodenoscopy (EGD) is recommended for patients with cirrhosis due to the risk of sudden, life-threatening bleeding.
-
123
Screening for colorectal cancer is typically started at age 50 unless risk factors exist, such as family history or genetic syndromes.
-
124
Increased serum ammonia concentration is useful for diagnosing hepatic encephalopathy but is not routine for alcoholic cirrhosis.
-
125
Measuring serum ferritin is essential for diagnosing hemochromatosis but is not necessary without it in cirrhosis patients.
-
126
The serum CA 19-9 assay is primarily used for diagnosing and monitoring treatment in gastrointestinal malignancies such as pancreatic cancer.
-
127
Cirrhosis increases the risk of developing hepatocellular carcinoma, the most common primary liver cancer.
-
128
Portal hypertension can lead to portosystemic shunts that may cause esophageal and gastric varices.
-
129
Cirrhosis can cause complications such as splenomegaly and ascites as a result of portal hypertension.
-
130
In a case of a 19-year-old unrestrained driver involved in a motor vehicle collision with signs of shortness of breath, the most likely diagnosis is pneumothorax.
-
131
Signs of tension pneumothorax include tachycardia, hypotension, hypoxia, jugular venous distension, and tracheal deviation.
-
132
The immediate management for acute tension pneumothorax involves needle decompression followed by tube thoracostomy.
-
133
Pneumothorax can result from air entering the intrapleural space due to either external sources like rib fractures or internal sources such as bronchopleural fistula.
-
134
In the context of a motor vehicle collision, hypoxia and shortness of breath with supraclavicular fossal distention is more indicative of pneumothorax than aortic dissection.
-
135
The clinical symptoms of pneumothorax include reduced breath sounds, hyperresonance to percussion, and respiratory distress.
-
136
In the event of a pneumothorax, needle decompression is the best immediate step to relieve pressure before performing further interventions.
-
137
Pneumothorax results from air entering the intrapleural space from either an external (e.g., stab wound) or internal source (e.g., ruptured bleb).
-
138
Signs of tension pneumothorax include tachycardia, hypotension, and jugular venous distension.
-
139
In cases of acute tension pneumothorax, needle decompression followed by tube thoracostomy is the management strategy.
-
140
Hypoxia and shortness of breath are more consistent with pneumothorax than aortic dissection, which may show a widened mediastinum on chest x-ray.
-
141
Aortic dissection presents with chest pain, hypotension, and tachycardia.
-
142
Clavicular fractures can occur in blunt trauma but do not cause hypoxia unless accompanied by pneumothorax.
-
143
Esophageal rupture, often due to trauma, can present with dysphagia and sharp chest pain.
-
144
Pericardial hemorrhage is more likely after penetrating chest trauma and can progress to cardiac tamponade.
-
145
Pneumothorax occurs when air enters and is trapped in the pleural space, leading to lung collapse and mediastinal mass effect.
-
146
Management of tension pneumothorax involves needle decompression to relieve pressure before tube thoracostomy.
-
147
Signs of aortic dissection include hypotension, widened mediastinum, and tachycardia.
-
148
Patients with atypical presentation of chest trauma can show hypoxia due to underlying pneumothorax.
-
149
In the clinical scenario involving a 67-year-old woman with severe upper abdominal pain, the most likely diagnosis following trauma is traumatic pancreatitis.
-
150
For a patient presenting with acute abdominal pain after blunt trauma, elevated serum levels of amylase and lipase are indicative of traumatic pancreatitis.
-
151
When evaluating abdominal pain after trauma, if bowel sounds are decreased, consider the possibility of internal injury such as traumatic pancreatitis.
-
152
In the context of an unstable trauma patient with abdominal tenderness, a high pulse rate of 110/min may indicate severe pain or internal bleeding leading to shock.
-
153
In trauma cases, the initial assessment of a patient's vital signs, including blood pressure of 150/60 mm Hg, is crucial to determining the extent of internal injury.
-
154
An elderly woman with abdominal trauma and elevated amylase levels should be evaluated for potential pancreatic injuries, specifically traumatic pancreatitis.
-
155
Increased serum amylase and lipase activity is commonly seen in acute pancreatitis.
-
156
Acute pancreatitis presents with severe epigastric abdominal pain that radiates to the back.
-
157
Acute pancreatitis can be complicated by necrosis, hemorrhage, abscess, or the formation of pseudocysts.
-
158
Treatment of uncomplicated acute pancreatitis includes intravenous fluids, bowel rest, and pain control.
-
159
Gallstone impaction may cause acute pancreatitis but requires a history of biliary colic for diagnosis, making traumatic pancreatitis more likely in this scenario.
-
160
Intestinal contusion is difficult to diagnose as it often does not cause any laboratory abnormalities and is typically inconspicuous on a CT scan.
-
161
Liver or splenic laceration can present with abdominal pain and peritonitis but typically shows localized tenderness in the right or left upper quadrant.
-
162
The educational objective regarding acute pancreatitis is that it can be caused by trauma and typically presents with epigastric abdominal pain, nausea, and vomiting.
-
163
Laboratory studies commonly show increased serum amylase and lipase concentrations in patients with acute pancreatitis.
-
164
In evaluating the association between cigarette smoking and cardiovascular disease, researchers identified a dose-response relationship. This means that as the number of cigarettes smoked daily increases, so does the risk for cardiovascular disease.
-
165
Observational studies can demonstrate correlation but cannot establish causation. Only prospective studies can verify causation.
-
166
The Bradford Hill criteria for causality include biologic plausibility, dose-response relationship, specificity, strength of association, and temporal relationship.
-
167
In the context of smoking and cardiovascular disease, the number of cigarettes smoked is the dose and the resulting risk for cardiovascular disease is considered the response.
-
168
If an association can be explained by a known biologic pathway, it has biologic plausibility. This is crucial in determining causality.
-
169
Which of the following is best represented by the correlation between daily cigarette smoking and cardiovascular disease? Dose-response relationship.
-
170
In observational studies, the strength of the association can suggest causality, especially when combined with other criteria like dose-response.
-
171
The presence of a dose-response relationship in a study suggests a correlation between two variables, such as the number of cigarettes smoked daily and the increased risk for cardiovascular disease.
-
172
When assessing causality, a correlation is more likely to represent causation if there is increased strength of association and a temporal relationship.
-
173
In observational studies, the specificity of association implies a one-to-one relationship between exposure and outcome, but in this study, it cannot be determined because cigarette smoking is associated with multiple diseases.
-
174
If an observed association can be explained by a known biologic pathway, it is said to have biologic plausibility.
-
175
A correlation coefficient r indicates the strength of an association, with r = 0 showing no correlation, and r = 1 indicating a perfectly positive correlation.
-
176
A temporal relationship exists if the exposure precedes the outcome, which in this case is uncertain for cigarettes and cardiovascular disease.
-
177
Despite the presence of a dose-response relationship, true causality cannot be determined solely by an observational study.
-
178
An example of increased risk for cardiovascular disease is seen when correlating the number of cigarettes smoked daily with the likelihood of developing the disease.
-
179
In research, the strength of association increases the likelihood that correlation represents causation, particularly in the case of smoking and cardiovascular disease.
-
180
In adults, a PPD skin test is considered positive at 15 mm of induration under general guidelines.
-
181
Latent tuberculosis infection (LTBI) is indicated by a positive PPD skin test or IGRA in the absence of active pulmonary or disseminated infection with Mycobacterium tuberculosis.
-
182
The most appropriate next step in management for a patient with a PPD induration of 15 mm is isoniazid therapy.
-
183
Patients exposed to high-risk situations may have a positive PPD at indurations of 10 mm or greater.
-
184
Prior BCG vaccination can cause a false-positive PPD, but this effect typically wanes within 5 years.
-
185
Chest x-ray is used to exclude active infection before initiating therapy for latent tuberculosis infection.
-
186
Common regimens for LTBI treatment include 9 months of isoniazid therapy.
-
187
For patients with a 15 mm induration on a PPD skin test, the best next step in management is isoniazid therapy.
-
188
Latent tuberculosis infection (LTBI) is defined as a positive PPD skin test or interferon gamma release assay (IGRA) in the absence of active pulmonary or disseminated infection with Mycobacterium tuberculosis (MTB).
-
189
Patients with HIV have a positive PPD skin test if the induration is at or above 5 mm; while the general population is positive if the induration is 15 mm or greater.
-
190
Health care workers are often considered to have a positive PPD skin test at an induration of 10 mm.
-
191
Before initiating therapy for LTBI, it is essential to exclude active infection with a chest x-ray.
-
192
In cases of LTBI, a common treatment regimen is 9 months of isoniazid therapy.
-
193
Repeat PPD skin test for a patient with a positive result is unnecessary and delays treatment.
-
194
Patients diagnosed with LTBI should be treated even if they received the BCG vaccine, as immunity wanes after about 5 years.
-
195
Sputum cultures for acid-fast bacilli are indicated for patients suspected of having pulmonary tuberculosis.
-
196
A 76-year-old woman with pneumonia develops a parapneumonic effusion. The most appropriate next step in management is Placement of a chest tube.
-
197
In the treatment of empyema, the diagnosis usually requires thoracentesis to sample the pleural fluid.
-
198
Empyema is defined by bacterial infection of the pleural space.
-
199
When treating empyema, fluid with a glucose concentration less than 40 mg/dL or a pH of less than 7.2 supports the diagnosis.
-
200
In patients with empyema, injecting tissue plasminogen activator and recombinant DNase through the chest tube can aid resolution of the infection.
-
201
In the management of empyema following community-acquired pneumonia, the best next step is the placement of a chest tube for drainage.
-
202
Empyema is defined as a bacterial infection of the pleural space that can develop as a complication of pneumonia.
-
203
The diagnosis of empyema typically requires thoracentesis to sample pleural fluid.
-
204
Pleural fluid in empyema often shows frank pus, an increased leukocyte count, decreased glucose concentration, and a pH of less than 7.2.
-
205
For the treatment of empyema, a chest tube is preferred, and therapy is optimized with intravenous antibiotics targeting the implicated organism.
-
206
If chest tube insertion fails to resolve empyema, video-assisted thoracoscopic surgery may be required for drainage.
-
207
A CT scan of the chest is typically not required to diagnose empyema and may delay necessary interventions.
-
208
Intravenous furosemide is indicated for hypervolemia and pulmonary edema, but not for empyema management.
-
209
Intubation and mechanical ventilation are reserved for patients with respiratory failure, not typically needed for those who are alert and stable.
-
210
Pleurodesis is reserved for patients with recurrent malignant pleural effusions or pneumothoraces, not empyema.
-
211
An empyema's clinical management emphasizes drainage through chest tubes due to the ineffectiveness of antibiotics alone.
-
212
In a patient with mild carpal tunnel syndrome, the most appropriate next step in management is use of a computer keyboard with a wrist pad.
-
213
Carpal tunnel syndrome results from compression of the median nerve within the carpal tunnel and presents with pain, weakness, and paresthesia.
-
214
Positive provocative test maneuvers for carpal tunnel syndrome include the Tinel test and the Phalen test.
-
215
In the case of carpal tunnel syndrome, patients with mild symptoms can be treated conservatively with wrist splinting and ergonomic changes.
-
216
When symptoms of carpal tunnel syndrome are severe or persistent, the patient may require surgical decompression.
-
217
A negative Spurling test suggests that the patient's shoulder examination is normal and her neurological complaints localize to the carpal tunnel.
-
218
In the case scenario, the patient is a 45-year-old woman with type 2 diabetes mellitus presenting with pain and swelling in her right hand.
-
219
Patients with carpal tunnel syndrome who type for long periods may benefit from ergonomic changes, such as using wrist support devices.
-
220
Carpal tunnel syndrome results from compression of the median nerve within the carpal tunnel and presents with signs and symptoms including pain, weakness, and paresthesia of the first three digits.
-
221
The most appropriate next step in management for a patient with mild carpal tunnel syndrome is the use of a computer keyboard with a wrist pad.
-
222
Patients with mild carpal tunnel syndrome may be treated conservatively with wrist splinting and ergonomic changes.
-
223
The Tinel and Phalen tests are positive provocative tests used to diagnose carpal tunnel syndrome.
-
224
For carpal tunnel syndrome, if symptoms persist or are severe, surgical decompression of the carpal tunnel may be required.
-
225
MRI of the right shoulder is unlikely to provide meaningful diagnostic information because the patient's symptoms localize to the carpal tunnel.
-
226
Oral hydrocodone is unnecessary for carpal tunnel syndrome because opiates are generally ineffective and potentially addictive.
-
227
In the case of the patient with severe right-sided chest pain, shortness of breath, and dizziness, the strongest predisposing risk factor for in-hospital mortality is advanced age.
-
228
Pulmonary embolism (PE) can be diagnosed definitively with a CT scan that uses intravenous contrast to opacify the pulmonary arteries.
-
229
Risk factors for the development of a pulmonary embolism include the presence of a deep vein thrombosis (DVT) and factors such as being obese or recently undergoing surgery.
-
230
In assessing in-hospital mortality risk, advanced age is noted as a major factor while obstructive shock is another significant risk factor to consider.
-
231
A positive Homans sign during left calf examination suggests the presence of a deep vein thrombosis (DVT).
-
232
Treatment of deep vein thrombosis or pulmonary embolism typically involves systemic anticoagulants.
-
233
In evaluating a patient with signs of DVT, clinical findings like calf tenderness and positive Homans sign are important for diagnosis.
-
234
In patients who have recently traveled in airplanes or cars for an extended period of time, the risk of developing a DVT increases significantly.
-
235
The patient's BMI of 17 kg/m² classifies her as underweight, which can be a component of evaluating overall health status in hospital settings.
-
236
In-hospital mortality risk for patients with signs of deep vein thrombosis (DVT) and pulmonary embolism (PE) is significantly increased by advanced age.
-
237
Pulmonary embolism can be definitively diagnosed with a CT scan timed to opacify the pulmonary arteries.
-
238
Risk factors for the development of PE include the presence of a DVT and factors like obesity and the use of hormonal birth control.
-
239
Treatment for DVT or PE involves the use of systemic anticoagulants.
-
240
While blood pressure can indicate health status, it is not definitive for evaluating mortality in patients showing signs of obstructive shock when compared to advanced age.
-
241
A positive Homans sign and calf tenderness are indicators that can help diagnose DVT, but they are not prognostic.
-
242
Patients with lower extremity swelling suggestive of DVT may also experience hemoptysis; however, it is not necessarily indicative of the severity of their illness.
-
243
Elderly patients with DVT or PE may have a lower body mass index (BMI) as a potentially positive prognostic indicator despite being at risk for DVT.
-
244
Risk factors for in-hospital mortality include obstructive shock and advanced age.
-
245
Common symptoms of pulmonary embolism (PE) include chest pain, tachycardia, and hypoxemia.
-
246
The core concept in managing DVT/PE includes understanding the importance of risk factors and appropriate use of anticoagulants.
-
247
In evaluating a pediatric patient with hypertension, the next best step is Renal Doppler ultrasonography.
-
248
Secondary hypertension in pediatrics can be caused by conditions such as renal artery stenosis and pheochromocytoma.
-
249
Typical initial tests for evaluating secondary hypertension in children include serum renin and aldosterone levels.
-
250
Primary hypertension is more common in school-age children who are overweight or obese, but less common in very young patients.
-
251
If adults are on three or more antihypertensives including a diuretic, they should be assessed for secondary hypertension.
-
252
The assessment of blood flow velocity in the renal arteries is critical for diagnosing renal artery stenosis.
-
253
In pediatric patients, the next most appropriate step for evaluating hypertension is renal Doppler ultrasonography. This is important for detecting secondary hypertension caused by underlying conditions.
-
254
Secondary hypertension can result from various conditions, including renal artery stenosis, glomerulonephritis, and Cushing disease.
-
255
Typical initial tests for evaluating secondary hypertension in children include measuring serum renin and aldosterone levels.
-
256
In pediatric patients, hypertension evaluation should focus on potential underlying causes rather than just being assumed as primary hypertension.
-
257
Adult patients on three or more antihypertensive medications should be evaluated for secondary hypertension, just as pediatric patients should.
-
258
Renovascular hypertension is diagnosed by assessing the velocity of blood flow through the renal arteries using Doppler imaging.
-
259
Treatment options for renal artery stenosis may include renal artery stenting.
-
260
Measurement of serum B-type natriuretic peptide is typically not relevant for diagnosing hypertension in children.
-
261
Polysomnography is not commonly used in pediatric patients for hypertension unless there's an indication of obstructive sleep apnea related to anatomical abnormalities.
-
262
Thyroid function tests are not the first line for hypertension evaluation, though hypothyroidism can be related to increased blood pressure.
-
263
The educational objective emphasizes that renal artery stenosis can cause secondary hypertension and is diagnosed via renal ultrasonography with Doppler to assess blood flow velocity.
-
264
Opioid intoxication can cause a decreased level of consciousness due to its effects as a CNS depressant. It may lead to sedation, bradycardia, depressed respiratory drive, and miosis.
-
265
In cases of suspected opioid intoxication, the patient's vital signs may show bradycardia and respiratory rates as low as 6/min.
-
266
The typical pupil response in opioid intoxication is miosis, which is less common in other neurologic conditions.
-
267
When assessing a 57-year-old woman with a history of chronic back pain and diabetes who is unresponsive, consider opioid intoxication as a primary cause of altered mental status.
-
268
Opioids interact with several neurotransmitter systems in the CNS, leading to effects such as altered mental status, sedation, and euphoria.
-
269
In the context of increased opioid use, consider the patient's medication history, including long-term use of oxycodone and carbamazepine.
-
270
The Glasgow Coma Scale score may decrease significantly during opioid intoxication, suggesting severe CNS depression.
-
271
Regular use of analgesics like ketorolac may inadvertently lead to decreased kidney function, worsening symptoms in cases of opioid toxicity, such as in the patient's case with chronic kidney issues.
-
272
Opioid intoxication leads to symptoms such as euphoria, altered mental status, and sedation. This patient's condition shows decreased purposefulness and may lead to respiratory depression.
-
273
A distinctive finding of opioid intoxication is miosis, caused by direct opioid receptor activity in brain areas responsible for pupillary control.
-
274
In cases of acute opioid intoxication, the best next step in management is to administer naloxone, a short-acting opioid antagonist.
-
275
Chronic subdural hematoma commonly presents with headache and cognitive impairment, particularly in elderly patients.
-
276
The symptoms of Conversion disorder include neurologic symptoms such as sensory dysfunction that are not explained by objective findings. This is in contrast to the signs seen in opioid intoxication.
-
277
Hypertensive encephalopathy may present with symptoms such as headache, but would not typically include bradypnea or miosis seen in opioid intoxication.
-
278
In cases of hypoglycemia, symptoms can include tachypnea and diaphoresis, contrasting with the bradypnea associated with opioid intoxication.
-
279
Opioids act throughout the CNS and peripheral nervous system, leading to effects such as reduced gut motility and thus causing constipation.
-
280
A patient with decreased kidney function may experience increased serum oxycodone due to reduced clearance of opioids.
-
281
Direct opioid receptor activity in brain areas responsible for pupillary control typically causes miosis, which is distinctive in opioid intoxication.
-
282
The key management step in acute poisoning from opioids is the administration of naloxone, which can prevent respiratory collapse.
-
283
Opioid intoxication causes symptoms of CNS depression, including sedation, respiratory depression, bradycardia, and hypotension. Miosis differentiates opioid intoxication from other neurologic conditions.
-
284
In the case of acute opioid intoxication, the best next step is administering naloxone, a short-acting opioid antagonist, to prevent respiratory collapse.
-
285
Chronic subdural hematoma refers to gradual blood accumulation between the dura and arachnoid membranes, commonly in elderly patients.
-
286
Conversion disorder involves neurologic symptoms not fully explained by objective findings on examination or imaging, such as sensory or motor dysfunction.
-
287
Hypertensive encephalopathy may lead to symptoms like headache, vomiting, and altered mental status when blood pressure is greater than 180/120.
-
288
Patients with hypoglycemia may show symptoms such as tremors, palpitations, and cognitive impairment, while bradypnea and miosis are atypical.
-
289
A ruptured saccular aneurysm leads to subarachnoid hemorrhage, presenting with severe headache, nausea, vomiting, and potentially coma.
-
290
Status epilepticus is defined as continuous epileptic activity for at least 5 minutes or at least two seizures with incomplete recovery of consciousness.
-
291
In a patient on total parenteral nutrition (TPN) with new onset fever and leukocytosis, the most appropriate next step in management is to obtain blood cultures from the catheter site.
-
292
Patients on TPN through a central line are at increased risk for bacteremia leading to sepsis, known as catheter-associated blood stream infection (CLABSI).
-
293
In the scenario of a 51-year-old man with a proximal jejunal enterocutaneous fistula, his clinical status shows a temperature of 38.4°C (101.1°F) and a leukocyte count of 14,000/mm3.
-
294
The presence of a long-term intravenous catheter substantially increases the risk for fungemia in TPN patients following abdominal surgeries.
-
295
When evaluating for sepsis, it is essential to draw anaerobic and aerobic blood cultures from two different sites, including at least one from the central line.
-
296
Following blood cultures in suspected sepsis, the next step is to start empiric antibiotics.
-
297
In the management of TPN-related infections, it is often recommended to remove the central venous catheter unless there are rare exceptions.
-
298
In a patient with new onset fever and leukocytosis on total parenteral nutrition (TPN) through a central line, the best next step in management is to obtain blood cultures from the catheter site.
-
299
The risk for bacteremia leading to sepsis is significantly increased in patients with a long-term intravenous catheter.
-
300
When evaluating for sepsis in patients with a central venous catheter, blood cultures should be drawn from two different sites, with at least one set from the central line.
-
301
In patients receiving TPN, fungemia should be suspected if they present with persistent fever, especially after recent abdominal surgeries.
-
302
Empiric antibiotics should be initiated following the collection of blood cultures in a patient suspected of sepsis.
-
303
A chest x-ray is typically performed as part of the workup for sepsis, but in the context of a central venous catheter, priority should be given to obtaining blood cultures.
-
304
A CT scan of the abdomen is indicated if the patient develops worsening abdominal pain or is suspected of a new intra-abdominal infection.
-
305
Removal of the central venous catheter is recommended in almost all instances of bloodstream infections, unless there are rare circumstances where it may remain in place.
-
306
If fungal elements are identified in the blood cultures of a TPN patient, initiation of intravenous antifungal therapy should be considered.
-
307
In patients on total parenteral nutrition (TPN) with a central line and new onset fever, the most appropriate next step in management is obtaining blood cultures from the catheter site due to the risk for catheter-associated blood stream infection (CLABSI).
-
308
Patients on TPN require evaluation for bacteremia and fungemia when they develop new fevers and leukocytosis, especially following recent abdominal surgeries.
-
309
When evaluating for sepsis in a patient with a central venous catheter, at least one set of blood cultures should be obtained from the central line and an alternative site.
-
310
The recommendation is to remove the central venous catheter in almost all circumstances when a patient develops symptoms indicative of sepsis.
-
311
Following blood cultures for suspected CLABSI, the next step is to initiate empiric antibiotics.
-
312
If a patient on TPN has persistent fevers despite broad-spectrum antibiotic therapy, consider starting intravenous antifungal therapy.
-
313
Catheter-related bloodstream infections should be suspected if a patient with a central venous catheter develops fevers and leukocytosis without obvious alternative infection signs.
-
314
The longer a central venous catheter remains in place, the higher the risk for infection.
-
315
If a patient's abdominal examination is benign and they develop a fever while on TPN, a CT scan of the abdomen is not indicated unless they show signs of new intra-abdominal infection.
-
316
An exploratory laparotomy for resection of a fistula would only be indicated if there was clear evidence of peritonitis, which is not present in this patient's examination due to absence of significant changes.
-
317
The study investigating patients with type 2 diabetes mellitus used discussions led by moderators to examine attitudes. This design is best described as Qualitative.
-
318
In the study, qualitative data was collected through focus group discussions of patients with type 2 diabetes mellitus, revealing their attitudes toward lifestyle modification.
-
319
Qualitative studies, like the one on diabetes management, explore social phenomena, such as barriers to treatment and social stigma.
-
320
The phenomenology approach in qualitative research, used in this diabetes study, focuses on understanding perspectives through individual interviews or group discussions.
-
321
If focus group discussions reveal that patients with diabetes feel lost regarding lifestyle modifications, what could be developed to assist them? An educational module could be created and tested quantitatively.
-
322
Qualitative studies are used to study social phenomena such as how individuals think about their disease, barriers to pursuing treatment, or the social stigma experienced by patients.
-
323
In qualitative studies, focus group discussions and interviews are often used to gather data about patients' attitudes toward lifestyle modification.
-
324
The phenomenology approach in qualitative studies explores a phenomenon by hearing the perspectives of those experiencing it, often through interviews.
-
325
If focus group discussions reveal that patients don't know where to start with lifestyle modifications, an educational module could be developed and tested among patients with type 2 diabetes mellitus.
-
326
A case report describes the disease course and outcome of a single patient, while a case series study talks about a group of patients with a similar diagnosis.
-
327
Matched case-control studies compare a group of patients with an outcome ({c1::cases}}) to a second matched group without that outcome (controls) to identify associated exposures.
-
328
A randomized trial is a prospective interventional study where patients are randomly assigned to receive an intervention compared to placebo therapy or standard therapy.
-
329
Qualitative studies may generate hypotheses or interventions that can then be tested quantitatively.
-
330
Educational Objective: Qualitative studies explore phenomena such as how individuals think about their disease, barriers to treatment, and social stigma experienced by patients.
-
331
In unstable trauma patients with signs of hypotension, tachycardia, and distant heart sounds, the most appropriate next step in management is focused assessment with sonography for trauma (FAST).
-
332
A patient with penetrating chest trauma presenting with hypotension may be experiencing pericardial tamponade.
-
333
Characteristic findings on echocardiography for pericardial tamponade include collapse of the right atrium and right ventricle during diastole.
-
334
In cases of hypotensive trauma, it is crucial to establish large bore intravenous access and begin resuscitation before diagnostic imaging.
-
335
The patient in this scenario consumed six 12-oz beers and used cocaine, which may contribute to their anxiety and hemodynamic instability.
-
336
The vital signs of a patient with pericardial tamponade often include hypotension and tachycardia.
-
337
The appropriate management for suspected cardiac tamponade includes pericardiocentesis or creating a pericardial window.
-
338
The stab wound is located 3 cm below the right nipple in this case of traumatic chest injury.
-
339
In unstable trauma patients presenting with hypotension and distant heart sounds, the most appropriate next step in diagnosis is bedside ultrasonography.
-
340
Characteristic findings on echocardiography for cardiac tamponade include pericardial effusion, collapse of the right atrium at end of diastole, and collapse of the right ventricle in early diastole.
-
341
During cardiac tamponade, the patient may experience jugular venous distention, decreased preload, and decreased cardiac output.
-
342
In hypotensive trauma patients, a focused assessment with sonography for trauma (FAST) is useful to evaluate for cardiac tamponade as well as pneumothorax, hemothorax, and hemoperitoneum.
-
343
It is critical to establish large bore intravenous access and provide immediate resuscitation with crystalloid before any diagnostics in unstable patients.
-
344
In patients with tension pneumothorax, placement of a right chest tube is most appropriate when presenting with decreased breath sounds, tracheal deviation, and hyperresonance.
-
345
When managing a hypotensive patient with serious traumatic injuries, it is essential to stabilize before performing endotracheal intubation.
-
346
A schematic representation of the presentation of cardiac tamponade includes symptoms like hypotension, distant heart sounds, and jugular venous distention to aid recognition of the condition.
-
347
In a 37-year-old man with a blood pressure of 175/97 mm Hg after dental extraction, what is the most appropriate next step in evaluation? Consider the family history of myocardial infarction at age 45 years and current smoker status. The answer is serum lipid studies.
-
348
Why should lipid studies be performed in this patient? The presence of hypertension and a family history of coronary vascular disease at an early age raises concern for increased cardiovascular risk.
-
349
What are considered other risk factors for coronary vascular disease? These include hypertension, type 2 diabetes, a positive family history, and smoking.
-
350
In men aged over 35, the USPSTF recommends screening for hyperlipidemia if they are at increased risk for coronary vascular disease.
-
351
What is the first-line pharmacotherapy for patients with hyperlipidemia? The answer is statins.
-
352
When should hemoglobin A1c be assessed? It should be checked but is less likely useful in a patient with a low-risk BMI like this 37-year-old.
-
353
What lifestyle modification can reduce risk for coronary vascular disease? Optimizing serum lipids through pharmacologic treatment and lifestyle changes is essential.
Heat Exhaustion in Adolescents
Case Study
A 17-year-old girl lost consciousness during a run. - Father's summary: Good grades; trying to lose weight while exercising. - Symptoms: Somnolent but responsive; elevated temperature (39°C), tachycardia (140/min), and hyperventilation (40/min). - Background: BMI is 30 kg/m² and she has been running 2-3 miles daily.
Diagnosis
Most likely diagnosis: Heat exhaustion (B). - Heat-related illnesses arise from strenuous exercise in hot, humid conditions. - Risk factors: Obesity, dehydration, poor fitness.
Heat Exhaustion vs. Heat Stroke
- Heat Exhaustion: Intolerance to exercise, increased core temperature without neurologic disturbances.
- Heat Stroke: Hyperthermia with altered mental status.
Management
- Immediate actions: Remove from heat, cool the body (immersion/cooling measures).
- Lab tests: May show hypernatremia, hyperkalemia and increased creatinine or BUN.
Dementia and Its Variants
Case Study
A 72-year-old man presents after a seizure and shows signs of forgetfulness and jerking movements.
Diagnosis
Most likely diagnosis: Creutzfeldt-Jakob Disease (CJD) (A). - Rapidly progressive dementia and ataxia are hallmarks. - Symptoms: Neuropsychiatric symptoms, myoclonus, and cognitive deficits.
Comparison of Related Conditions
- Alzheimer's: Gradual memory loss, no seizures.
- Frontotemporal Dementia: Personality changes, gradual onset.
- Lewy Body Dementia: Cognitive fluctuations, visual hallucinatory episodes.
- Wernicke-Korsakoff Syndrome: Memory deficits due to alcohol misuse.
Chlamydia Testing Implications
Patient Overview
A 37-year-old woman questions a positive Chlamydia test after a stable relationship for 7 years.
Diagnostic Evaluation
Correct answer: Positive predictive value (E). - Important for interpreting diagnostic tests. - Sensitivity: Likelihood of a true positive. - Specificity: Likelihood of a true negative.
Understanding Predictive Values
- PPV:
- High when the probability of disease is high.
- Affected by test specificity and population prevalence.
Management of Supraventricular Tachycardia
Case Study
A 7-month-old girl has rapid breathing and distress.
Diagnosis
Most appropriate next step: Intravenous adenosine therapy (C). - SVT in children requires immediate management. - Treatment: Adenosine to block AV node conduction.
Incorrect Choices
- Ambulatory Monitoring (A): Not acute situation.
- Echocardiography (B): Not necessary in acute SVT case.
Ethambutol and Visual Impairment
Patient Report
A 67-year-old woman reports blurred vision.
Diagnosis
Most likely cause: Ethambutol toxicity (A). - Symptoms: Optic neuropathy presenting with decreased visual acuity. - Adverse Effects: Red-green color blindness.
Medication Overview
- Understanding other TB medications and their adverse effects:
- Isoniazid: Hepatotoxicity, peripheral neuropathy risk.
- Pyrazinamide: Hepatotoxicity, hypersensitivity.
- Rifampin: Liver enzyme interactions.
Testing for Hypertension in Non-obese Adult
Patient Background
A 37-year-old man exhibited elevated blood pressure post-dental extraction.
Immediate Actions
Most appropriate next step: Serum lipid studies (D). - Important due to family history of coronary disease. - Assess cardiovascular risk factors.
Clinical Implication
- Understanding the implications of lifestyle changes and pharmacotherapy in controlling hypertension.
- Guidelines: Screen for lipids in patients with additional risk factors.