Salve seu deck antes que desapareça
Esses flashcards ainda não foram salvos — eles desaparecerão quando você sair. Crie uma conta gratuita para mantê‑los e desbloquear tudo abaixo.
- Salve este deck em sua conta
- Estude com spaced repetition
- Exportar para Anki (.apkg) ou PDF
- Processe documentos com até 100 páginas
- Imagens extraídas dos seus PDFs
- Extração de texto mais nítida e um modelo de IA mais avançado
What is the primary definition of the AANA Code of Ethics?
In the context of clinical practice, what are Standards of Care?
How are Standards of Care determined?
By individual hospital policies
By patient preference
By government decree only
By consensus and approval of recognized authoritative body
When can Standards of Care be modified?
What is the fundamental difference between Standards of Care and Practice Guidelines?
AANA Standard 1 focuses on _______, emphasizing the respect for the patient's _______.
AANA Standard 2 pertains to _______, which involves documenting the patient's general health, _______.
What documentation is required under Standard 4 regarding informed consent?
What is the frequency for documenting blood pressure, heart rate, and respiration during all anesthetics?
According to Standard 6, how should anesthesia equipment be managed prior to each use?
For patient ventilation, confirm intubation of the trachea or placement of airway devices by _______, _______, and _______.
What safety measures should be taken regarding physiological monitoring device alarms?
What is the primary responsibility of a CRNA when transitioning patient care to another professional?
What is the main goal of operating anesthesia equipment as described in Standard 6?
To maximize anesthesia output
To minimize the risk of fire, explosion, electrical shock, and equipment malfunction
To expedite patient recovery time
To reduce equipment maintenance costs
What is the ethical principle of Beneficence?
Define negligence in the context of professional practice.
What are the four required elements of proof for a plaintiff in a negligence case?
The _______ doctrine translates to _______, where the _______ shifts from the plaintiff to the defendant.
When should a patient be informed of a medical risk?
Only when the risk is low and severity is great
Only when the severity is minor
Only when the patient specifically asks for details
When the risk is statistically high
What are the two types of Advanced Directives?
What is the function of a Medical Durable Power of Attorney?


What is the classification for a Level 5 surgical urgency?
What is an elective surgical procedure?
What does a patient's physical and history assessment allow for during anesthesia planning?
Which herbal supplement use is noted as often overlooked?
What are three examples of patient-related anesthetic history complications?
What condition might explain a prolonged duration of muscle relaxant effect in a patient?
For NPO status, it is important to document the _______ and the _______.
When assessing airway requirements, what does the airway assessment allow for?
Planning for masking, intubation, or alternate airway modalities
Determining the patient's ASA physical status
Calculating the required dosage of muscle relaxants
Scheduling the procedure urgency level
What is the minimum fasting period required before surgery for clear liquids, such as water, black coffee, or pulp-free fruit juice?
How long should a patient fast before surgery after consuming breast milk?
What is the required minimum fasting period for nonhuman milk, such as infant formula?
What is the required minimum fasting period for a light meal containing toast and clear liquids?
What is the minimum fasting period for a regular or heavy meal, including fried or fatty food?
In the ASA Physical Status Classification system, what does the addition of an 'E' denote?
According to the ASA Physical Status Classification, how is an 'ASA 1' patient described?
Healthy patients
Declared brain-dead patient
Severe disease process
Moribund patient
Which ASA classification level describes a patient who is moribund and not expected to survive 24 hours with or without an operation?
ASA 6
ASA 5
ASA 3
ASA 4
An emergency surgery is defined as existing when delay in treatment would lead to a significant increase in the _______.
What is the clinical significance of an inability to achieve 4 METs?
What is the formal definition of 1 MET?
Which six independent risk factors are included in the Revised Cardiac Risk Index (RCRI)?
What is the Revised Cardiac Risk Index (RCRI) primarily used for?
To assess metabolic equivalents
To measure long-term mortality
To assign perioperative cardiac risk
To diagnose coronary artery disease
Chronic hypertension affects autoregulation curves by causing a _______ and a _______.
What are the common symptoms of unstable cardiac disease that require further evaluation?
What activities require an energy expenditure of 4 METs according to the estimation table?
What are the common symptoms of aortic stenosis (AS) or its disease progression?
What is the recommended interval for interrogating a patient's pacemaker?
What is the recommended interval for interrogating a patient's ICD?
For patients with coronary artery stents, the delay for elective surgery should be _______ days for bare metal stents (BMS) and _______ days for drug-eluting stents (DES).
What happens when a magnet is placed over an implanted cardioverter-defibrillator (ICD)?
How many risk factors for CAD indicate an intermediate risk level for pre-operative testing?
0-1
2
3
4
What does a systolic murmur in the right second intercostal space indicate?
According to AHA/ACC guidelines, preoperative echocardiography is required for moderate to severe valvular stenosis or regurgitation if no studies have been performed within _______ or if there is worsening clinical status.
What are the components of the STOP-Bang screening tool for obstructive sleep apnea?
What is considered a high-risk score on the STOP-Bang screening tool?
4+
2+
0-3
5+
What happens to the body 24-48 hours after smoking cessation?
What improvements occur 6-8 weeks after smoking cessation?
Long-term benefits of smoking cessation include an addition of _______ life expectancy and a reduced risk of _______ and _______.
What are three common GI and hepatic conditions assessed in a preoperative history?
What conditions are commonly noted in a renal assessment?
What are three blood-related conditions relevant to a hematologic assessment?
What is the normal measurement for the interincisor gap (IIG) during a preoperative airway exam?
What is the normal thyromental distance (TMD) measurement?
For the airway exam, _______ extension is necessary to align the axes and visualize the _______.
During an airway exam, the presence of ridges from the patient's teeth on the tongue is a sign that the _______ does not have much room.
What does the upper lip bite test signify during an airway exam?
Difficult intubation
Macroglossia
Reduced neck extension
Good mobility
Why is macroglossia problematic during intubation?
The preoperative physical exam includes assessing _______, _______, _______, and _______.
What structures are visible in a Mallampati Class 1 airway? 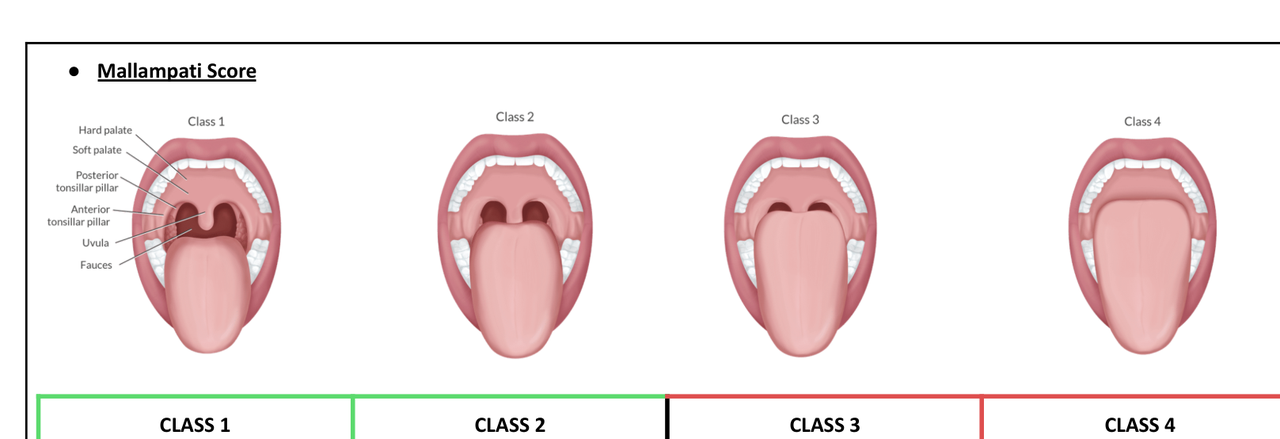
Which Mallampati class is characterized by the soft palate and upper portion of the uvula being visible?
What is the visibility expectation for a Mallampati Class 3 airway?
What structure is visible in a Mallampati Class 4 airway?
Predictors of difficult intubation include an interincisor distance of less than _______.
A patient with a 'thick neck' is a predictor of difficult intubation if the circumference is greater than _______ in males or _______ in females.
Which of the following is considered a predictor of difficult mask ventilation?
Long neck
Young age
Obesity
High range of motion of C-spine
Besides obesity and male gender, what is another anatomical predictor of difficult mask ventilation related to the face?
According to the 2012 ASA Practice Advisory, how should pre-op tests be ordered for asymptomatic patients?
What are the clinical indications for ordering a preoperative CBC?
What factors should the decision to order T&S (Type and Screen) or T&C (Type and Crossmatch) be based on?
For preoperative blood conservation, strategies should be considered to minimize the use of _______.
How long prior to the date of surgery (DOS) should NSAIDs be held?
How long prior to the date of surgery (DOS) should Coumadin be held?
Which of the following medications should be continued before surgery?
GLP-1 Agonists
Statins
Diuretics
NSAIDs
What is the recommended pre-operative hold time for St. John's Wort?
What is the recommended pre-operative hold time for Enbrel?
How should high-risk antiplatelet therapy be managed before surgery?
What is the upper limit for glucose control in Type 1 diabetic patients undergoing surgery?
When should antibiotics be administered in relation to the incision?
What is the recommended antibiotic strategy if a procedure is prolonged beyond two half-lives?
What dosage adjustment is required for morbidly obese patients receiving antibiotic prophylaxis?
Which antibiotics should be used for surgical prophylaxis in patients with a penicillin allergy?
What criteria define Mendelson's syndrome?
What is the most significant ranked risk factor for pulmonary aspiration?
Obesity
Emergency surgery
GERD
Opioid use
Routine pharmacologic prophylaxis for aspiration is _______ in otherwise healthy patients with no risk factors undergoing elective procedures.
What is the primary clinical benefit of administering Sodium Citrate prior to anesthesia?
Why should Metoclopramide be avoided in patients with a suspected bowel obstruction?
Which type of antacid is contraindicated for use due to the risk of serious pulmonary sequelae if aspirated?
Nonparticulate antacids (e.g., Sodium Citrate)
Histamine-2 receptor antagonists
Proton pump inhibitors
Particulate antacids (e.g., Tums, Rolaids)
How do Histamine-2 receptor antagonists affect gastric secretions?
Among H2 receptor antagonists, _______ has the longest duration of action, typically lasting _______ hours.
What is the primary mechanism of action for Proton Pump Inhibitors (PPIs)?
List three primary goals of administering pre-operative medication.

Extreme caution should be used with pre-op sedation in patients with _______, _______, or _______.
What is the primary action of Dexmedetomidine as an alpha-2 agonist?
What is a characteristic side effect of opioid administration regarding gastrointestinal function?
Which anticholinergic medication listed is known to be more potent than Atropine for antisialagogue effects?
Which drug is categorized as a Quaternary Amine anticholinergic that does not easily cross the blood-brain barrier?
Glycopyrrolate
Atropine
Midazolam
Scopolamine
According to the table comparing anticholinergics, which agent has the strongest sedative and amnesic effects?
The most common benzodiazepine used in anesthetic practice is _______, which is valued for its _______.
Why is the routine use of anticholinergics considered uncommon?
What are the five main risk factors for PONV in adults? 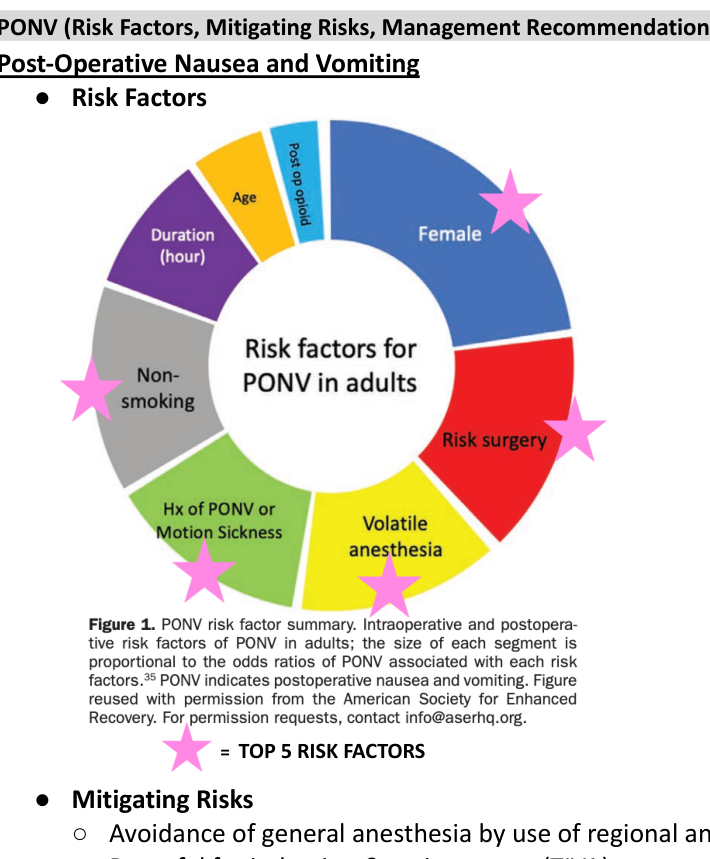
Which of the following is a recommended strategy to mitigate PONV?
Routine use of nitrous oxide
Avoidance of hydration
Increased use of volatile anesthetics
Use of regional anesthesia
For patients with _______ risk factors for PONV, give _______ agents; for patients with _______ risk factors, give _______ agents.
What is the recommended newer stress-dose steroid treatment for the first day of surgery?
Potential adverse effects of stress-dose steroid treatment include: - _______ - _______ - _______ - _______ - _______
What is the typical prophylactic combination used against allergic reactions?
Pretreatment with a combination of _______ is more effective than _______ alone.
What are the five major goals of general anesthesia?
During which stage of Guedel's anesthesia is 'Excitement' observed?
Stage 3
Stage 2
Stage 4
Stage 1
What are the pupil characteristics in Guedel's Stage 4 anesthesia?
In Guedel's classification, Stage 1 is also known as the _______ or _______.
What is the primary characteristic of Guedel's Stage 4 anesthesia?
What occurs during Plane 4 of Guedel's Stage 3 (Surgical Anesthesia)?
In Guedel's Stage 3, Plane 3, what happens to the light reflex?
What are the physiological signs associated with Guedel's Stage 2 (Excitement)?
What mnemonic is used for pre-induction anesthesia tasks?
What does each letter in the 'MS. MAIDS' mnemonic stand for in the context of pre-induction anesthesia tasks?
The components of the _______ mnemonic are: - _______ - _______ - _______ - _______ - _______ - _______ - _______
What is the primary goal of administering pre-induction medications?
What are two ways to achieve preoxygenation for anesthesia induction?
How is loss of consciousness (LOC) assessed during pre-induction?
List four methods to verify endotracheal tube (ETT) placement.
What is a standard component of pre-induction documentation?
Discharge summary
Informed consent obtained
Post-operative pain scale
Patient insurance verification
What is the primary goal of Rapid Sequence Induction (RSI)?
What is the clinical endpoint for preoxygenation in RSI?
When should cricoid pressure be applied and released during RSI?
The Cormack-Lehane Grade 1 view indicates a _______ view of the glottic opening.
Which of the following is a contraindication to the use of succinylcholine (SCh) for RSI?
Full stomach
Pregnancy
Malignant hyperthermia (MH) susceptibility
GERD
Based on the Cormack-Lehane scale, what is visible in a Grade 3 view?
What is the definition of fasciculations seen with succinylcholine induction?
Using the provided Cormack-Lehane grading scale illustration, which grade displays only the soft palate?
What are some clinical indications for using Total Intravenous Anesthesia (TIVA)?
What categories of drugs are commonly used in Balanced Anesthesia?
What are the minimum recording intervals for vital signs (BP, HR, RR) during maintenance of anesthesia?
What specific patient safety documentation must occur every 30 minutes regarding body position?
Intraoperative documentation of _______ (such as cardiac arrest, anaphylactic reaction, difficult airway, or EKG changes) usually requires a separate note in the patient's chart.
Which of the following monitoring parameters is required to be documented at a minimum interval of every 15 minutes?
BP, HR, RR
Rate, Vt, PIP, PEEP
O2, N2O, or air
SaO2, FiO2, ETCO2
Regarding the surgical time-out, what items are included in the verification checklist?
What clinical signs are associated with 'Light Anesthesia' when Neuromuscular Blocking Drugs (NMBD) are present?
What are the cardiovascular effects of excessive 'deep anesthesia'?
Which of the following is considered a patient group less suited for deep extubation?
Obese patients
Patients with no history of aspiration
Patients with low BMI
Patients with high tidal volume
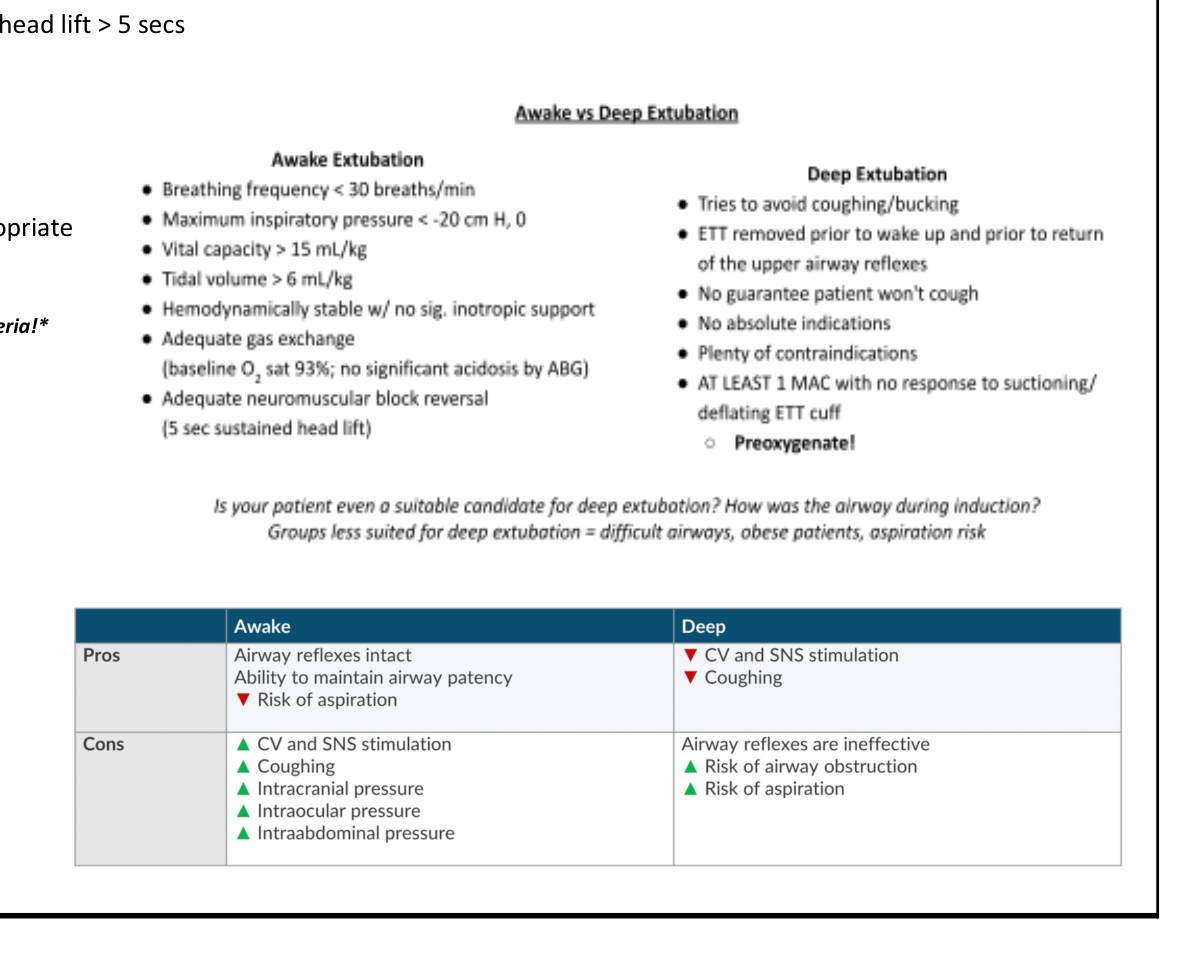
The requirements for awake extubation include: - Breathing frequency < _______ breaths/min - Maximum inspiratory pressure < _______ cm \(H_2O\) - Vital capacity > _______ mL/kg - Tidal volume > _______ mL/kg
According to the comparative table, what is a primary 'Con' of awake extubation?
What does a deep extubation attempt to avoid?
For deep extubation, the ETT is removed _______ and _______.
List the three items that must be verbally confirmed by the surgeon, anesthesia professional, and nurse before skin incision.
What is the Aldrete score required to meet discharge criteria?
According to the Aldrete Scoring system, what oxygen saturation value indicates a score of 2?
What blood pressure criteria is needed for a score of 2 in the circulation category of the Aldrete score?
For the consciousness category of the Aldrete score, a patient who is _______ receives a score of 2, while a patient who is _______ receives a score of 1.
What is the score for a patient who is apneic in the respiration category of the Aldrete scoring system?
0
3
2
1
When is the anesthesia end time documented?
In the context of follow-up post-op notes, how often should inpatients be seen after discharge from PACU?
What elements should be included in a PACU handoff?
What is the leading cause of anesthesia-related malpractice claims?
Name three causes of severe hypoxemia in the context of anesthesia. 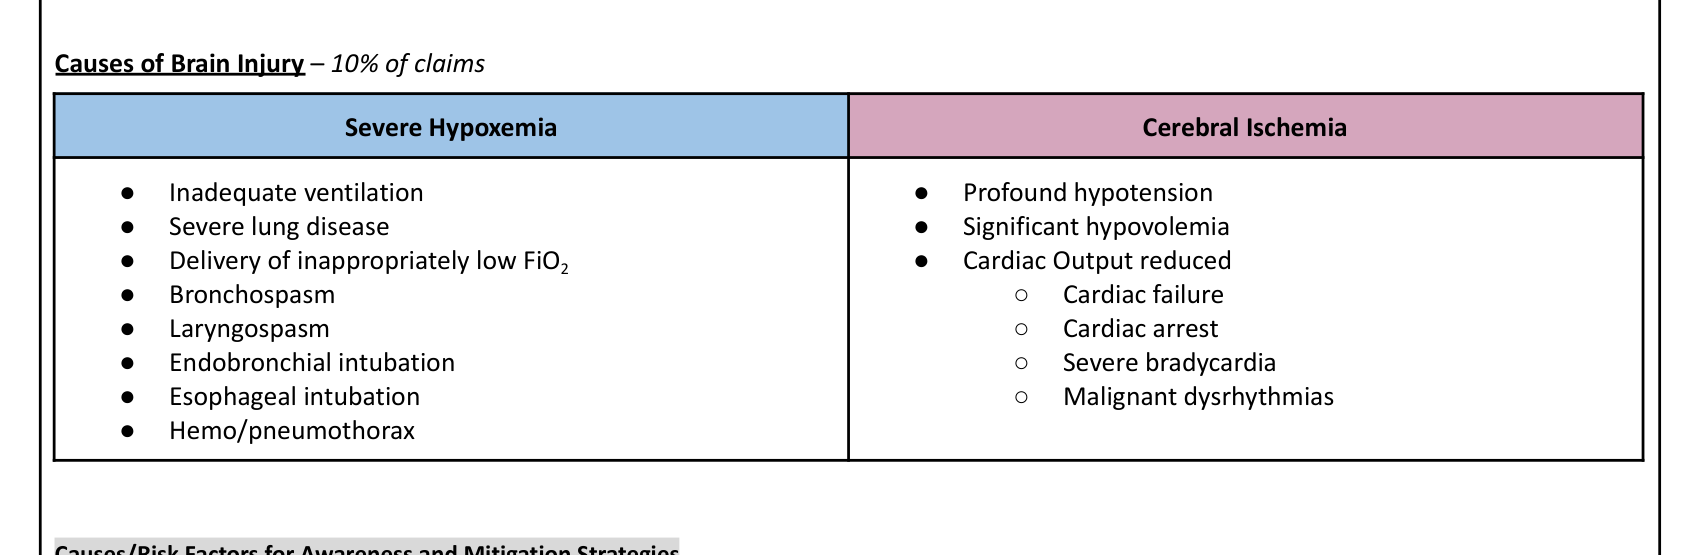
What are three common causes of reduced cardiac output leading to cerebral ischemia under anesthesia?
The psychological consequences of anesthesia awareness can include _______, _______, and _______.
List four risk factors associated with anesthesia awareness.
What are three pharmacological or monitoring strategies used to mitigate the risk of anesthesia awareness?
What is the most common reported eye injury related to anesthesia?
What are three causes of corneal abrasion during anesthesia?
Which surgical positions or procedures are risk factors for ischemic optic neuropathy?
What are the causes of central retinal artery occlusion?
Mendelson's syndrome is a type of chemical pneumonitis caused by the aspiration of gastric contents with a pH of less than _______ and a volume of _______ or greater.
What are the prevention strategies for Mendelson's syndrome?
What is the primary genetic defect associated with malignant hyperthermia?
What classes of agents are known to trigger malignant hyperthermia?
What are the earliest clinical signs of malignant hyperthermia?
Malignant hyperthermia is inherited in an _______ pattern, meaning that _______ defective gene is needed for the disease to manifest.
What is a major consequence of sustained hypermetabolism in malignant hyperthermia related to muscle cell breakdown?
Decrease in core temperature
Decreased \(ETCO_2\) levels
Release of myoglobin, \(K^+\), and CK
Improved muscle oxygenation
What physiological event occurs when triggering agents react with RYR1 receptors, initiating a hypermetabolic state?
What condition occurs if the body temperature reaches or exceeds \(41^{\circ} C\) during a malignant hyperthermia crisis?
What are two specific musculoskeletal complications resulting from rhabdomyolysis in malignant hyperthermia?
What is the mechanism of action of dantrolene?
What is the initial recommended dose of dantrolene for the treatment of malignant hyperthermia?
Which of the following is true regarding the new formulation of dantrolene (Ryanodex) compared to the original (Dantrium)?
It is 150 times more concentrated.
It takes 860 seconds to mix.
It requires 60 ml of sterile water.
It is less expensive than the original formulation.
Delays in treatment are associated with _______ rates of complications and death in MH-related cases.
What are the three main categories of causes for Neuroleptic Malignant Syndrome?
How do NMS and MH compare regarding inheritance and onset time?
Which drug is used as a dopaminergic agonist for the treatment of Neuroleptic Malignant Syndrome?
Which of the following is a symptom of Neuroleptic Malignant Syndrome?
Bradycardia
Muscle rigidity
Hypothermia
Increased dopamine activity
What three myopathic disorders are associated with susceptibility to malignant hyperthermia?
What percentage of patients with masseter muscle rigidity (MMR) test positive for malignant hyperthermia susceptibility (MHS)?
In the management of masseter muscle rigidity (MMR) during emergent surgery, _______ is not recommended.
What is the Gold Standard test for malignant hyperthermia susceptibility?
What are the sensitivity and specificity of the Caffeine-Halothane Contracture Test (CHCT)?
Which of these is a known disadvantage of genetic testing for malignant hyperthermia susceptibility?
It is always less accurate than the CHCT.
A negative test does not rule out susceptibility.
It is more expensive than the CHCT.
It requires a muscle biopsy.
What is the initial dose and repetition protocol for Dantrolene in the management of an MH crisis?
Which class of drugs is contraindicated in the management of MH-related dysrhythmias after the administration of Dantrolene?
What are the measures to prevent myoglobinuria-induced renal failure in the context of an MH crisis?
The earliest clinical sign of Malignant Hyperthermia (MH) is _______.
What is the recommended cleaning procedure for an anesthesia machine before a case involving an MH-susceptible patient?
Which medications may be used to treat dysrhythmias during an MH crisis?
Procainamide and lidocaine
Verapamil
Diltiazem
Amlodipine
What is the primary risk associated with arm abduction exceeding 90 degrees in a surgical patient? 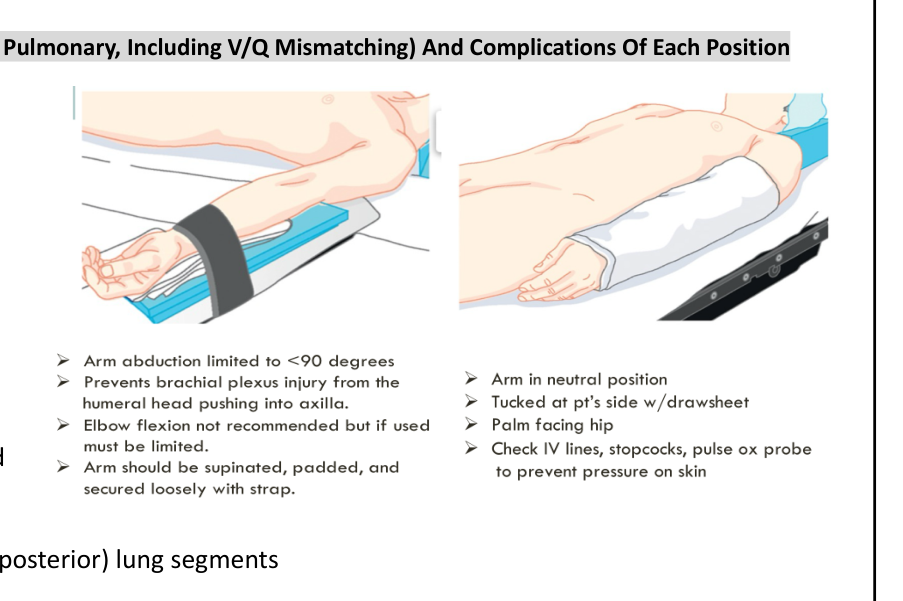
During the _______ position, arm abduction must be limited to less than _______ to prevent brachial plexus injury.
Which compensatory mechanism is attenuated by neuraxial anesthesia?
How does neck flexion affect the ETT position?
What sex is specifically associated with an increased risk of ulnar neuropathy during surgery?
What is the effect of increased intrathoracic pressure on venous return (VR)?
Which position is identified as the most common surgical position?
Prone
Lithotomy
Lateral decubitus
Supine
What is the recommended intervention to mitigate back pain caused by the loss of normal lumbar lordotic curvature in the supine position?
What is the primary cardiovascular effect of the Trendelenburg position?
What happens to functional residual capacity (FRC) in the Trendelenburg position?
What are the common potential complications associated with the Trendelenburg position?
How does the Reverse Trendelenburg position affect cardiovascular parameters?
The Reverse Trendelenburg position improves exposure for _______ and typically causes a _______ in cerebral perfusion.
What is the effect of the lithotomy position on pulmonary function?
What characterizes the 'Standard' lithotomy position?
Hips flexed at 90 degrees, knees bent with lower legs parallel to floor
Hips flexed at 30-45 degrees
Hips flexed at 90 degrees or more with greater knee extension
Hips flexed at 180 degrees
What is the effect of obesity on the pulmonary complications of the lithotomy position?
Which nerve is the most commonly injured in the lithotomy position?
Where should an axillary roll be placed in a patient in the lateral decubitus position?
What is the primary purpose of placing an axillary roll in the lateral decubitus position?
In the lateral decubitus position, which lung is favored by perfusion?
In the lateral decubitus position, which lung is favored by ventilation in an anesthetized patient?
Induction of anesthesia causes _______ FRC.
Lateral decubitus position complications include: - _______ - _______ - _______ - _______
Which nerve injury can be caused by the shoulder rolling forward onto the dependent arm in the lateral decubitus position?
Femoral nerve
Obturator nerve
Suprascapular nerve
Common peroneal nerve
What happens to venous return when the inferior vena cava is compressed in the prone position?
What effect does the prone position have on pulmonary compliance in obese patients?
List three potential ocular complications of the prone position.
When the head is rotated to the side for more than _______ in the prone position, there is a risk of _______.
When a patient is in the sitting position, where should arterial blood pressure be measured?
What happens to lung volumes and functional residual capacity (FRC) in the sitting position?
What is a potential risk of excessive neck flexion in the sitting position?
What serious complication can occur in the sitting position due to stretching of the spinal cord?
Which of the following is an effect of the sitting position on cerebral blood flow?
No change
Increased
Decreased
Unpredictable
What is the consequence of stretching a nerve to 5% greater than its normal resting length?
Which peripheral nerve is the most frequently injured?
What forearm position helps avoid external compression of the ulnar nerve in the cubital tunnel?
What motor manifestation is characteristic of an ulnar nerve injury?
Radial nerve injury results in loss of dorsiflexion, a condition known as _______.
What clinical deformity is associated with a median nerve injury when a patient attempts to make a fist?
According to the mnemonic 'DR CUMA', which nerve injury is associated with 'Claw Hand'?
Radial nerve
Femoral nerve
Ulnar nerve
Median nerve
What are two clinical manifestations of an Ulnar nerve injury?
What physical actions increase the risk of brachial plexus stretching injuries?
Common peroneal injury is the _______ nerve in the lower extremity.
What is a common mechanism for peroneal nerve compression damage?
What is the primary manifestation of an obturator nerve injury?
What is the cause of pudendal nerve injury during surgery?
What site is most susceptible to external pressure for a saphenous nerve injury?
Which of the following is a manifestation of radial nerve injury?
Foot drop
Claw Hand
Inability to flex forearm
Wrist drop
What preventative measures should be taken to avoid venous air embolism during surgery?
Which surgical positions are associated with the risk of alopecia?
How can corneal abrasion be prevented during surgery?
What is the recommended prevention for brachial plexus nerve palsy during surgery?
What surgical positions increase the risk of common peroneal nerve palsy?
What prevention strategy is recommended for radial nerve palsy during surgery?
What prevention strategy is recommended for ulnar nerve palsy during surgery?
What is the recommended prevention for retinal ischemia during surgery?
What is the recommended prevention for skin necrosis during surgery?
Flashcards neste deck (261)
-
What is the primary definition of the AANA Code of Ethics?
It outlines expected behaviors for individuals who are part of the CRNA profession.
ethics aana professionalism -
In the context of clinical practice, what are Standards of Care?
A set of rules or minimum requirements for clinical practice that ensures high quality patient care.
standards clinical nursing -
How are Standards of Care determined?
By individual hospital policies
By patient preference
By government decree only
By consensus and approval of recognized authoritative body
standards clinical -
When can Standards of Care be modified?
Only under unusual circumstances, such as extreme emergencies or unavailability of equipment.
standards practice legal -
What is the fundamental difference between Standards of Care and Practice Guidelines?

- Standards of Care: Must be adhered to, set of rules/requirements.
- Practice Guidelines: Should be adhered to, represent recommendations and evidence-based practice.
practice guidelines standards -
AANA Standard 1 focuses on Patient Rights, emphasizing the respect for the patient's autonomy, dignity, and privacy.
aana standards nursing -
AANA Standard 2 pertains to Pre-anesthesia Patient Assessment and Evaluation, which involves documenting the patient's general health, allergies, medication history, pre existing conditions, anesthesia history, and relevant diagnostic tests.
aana standards anesthesia -
What documentation is required under Standard 4 regarding informed consent?
Obtain and document or verify that the patient or legal representative has given informed consent for planned anesthesia care or related services.
standards consent -
What is the frequency for documenting blood pressure, heart rate, and respiration during all anesthetics?
At least every five minutes.
monitoring standards -
According to Standard 6, how should anesthesia equipment be managed prior to each use?
Verify the function of anesthesia equipment prior to each anesthetic.
equipment standards -
For patient ventilation, confirm intubation of the trachea or placement of airway devices by auscultation, chest excursion, and confirmation of expired carbon dioxide.
ventilation monitoring -
What safety measures should be taken regarding physiological monitoring device alarms?
Ensure variable pitch and threshold alarms are turned on and audible.
monitoring safety -
What is the primary responsibility of a CRNA when transitioning patient care to another professional?
Evaluate the patient's status and determine when it is appropriate to transfer responsibility, while communicating essential information for continuity of care.
transfer standards -
What is the main goal of operating anesthesia equipment as described in Standard 6?
To maximize anesthesia output
To minimize the risk of fire, explosion, electrical shock, and equipment malfunction
To expedite patient recovery time
To reduce equipment maintenance costs
equipment safety -
What is the ethical principle of Beneficence?
The obligation to do good.
ethics -
Define negligence in the context of professional practice.
Medical malpractice is a form of professional negligence.
 law negligence
-
What are the four required elements of proof for a plaintiff in a negligence case?
- Duty
- Breach of Duty
- Causation
- Damages
law negligence -
The Res ipsa loquitur doctrine translates to the thing speaks for itself, where the burden of proof of causation shifts from the plaintiff to the defendant.
law -
When should a patient be informed of a medical risk?
Only when the risk is low and severity is great
Only when the severity is minor
Only when the patient specifically asks for details
When the risk is statistically high
consent ethics -
What are the two types of Advanced Directives?
- Living Will
- Medical Durable Power of Attorney
medical directives -
What is the function of a Medical Durable Power of Attorney?
It designates another person to make health care decisions for a patient if they become incompetent or unable to make such decisions themselves.
medical directives -
-
What is the classification for a Level 5 surgical urgency?
Within 24 hours.
anesthesia surgery -
What is an elective surgical procedure?
A procedure planned and scheduled in advance with no urgency.
anesthesia surgery -
What does a patient's physical and history assessment allow for during anesthesia planning?
- Assignment of ASA status
- Formulation of patient-related and procedure-related problem list
- Assessment of risk
- Choosing patient-specific anesthetic agents and techniques
anesthesia assessment -
Which herbal supplement use is noted as often overlooked?
Herbal supplements, which are used by up to 30% of the US population.
anesthesia history -
What are three examples of patient-related anesthetic history complications?
- Difficult intubation
- Prolonged emergence
- Unplanned admission
anesthesia history -
What condition might explain a prolonged duration of muscle relaxant effect in a patient?
Pseudocholinesterase deficiency.
anesthesia complications -
For NPO status, it is important to document the last solid food, content and time and the last liquid intake.
anesthesia npo -
When assessing airway requirements, what does the airway assessment allow for?
Planning for masking, intubation, or alternate airway modalities
Determining the patient's ASA physical status
Calculating the required dosage of muscle relaxants
Scheduling the procedure urgency level
anesthesia airway -
What is the minimum fasting period required before surgery for clear liquids, such as water, black coffee, or pulp-free fruit juice?
2 hours
preoperative fasting -
How long should a patient fast before surgery after consuming breast milk?
4 hours
preoperative fasting -
What is the required minimum fasting period for nonhuman milk, such as infant formula?
6 hours
preoperative fasting -
What is the required minimum fasting period for a light meal containing toast and clear liquids?
6 hours
preoperative fasting -
What is the minimum fasting period for a regular or heavy meal, including fried or fatty food?
8 hours
preoperative fasting -
In the ASA Physical Status Classification system, what does the addition of an 'E' denote?
Emergency surgery
asa surgery -
According to the ASA Physical Status Classification, how is an 'ASA 1' patient described?
Healthy patients
Declared brain-dead patient
Severe disease process
Moribund patient
asa classification -
Which ASA classification level describes a patient who is moribund and not expected to survive 24 hours with or without an operation?
ASA 6
ASA 5
ASA 3
ASA 4
asa classification -
An emergency surgery is defined as existing when delay in treatment would lead to a significant increase in the threat to life or body part.
surgery definitions -
What is the clinical significance of an inability to achieve 4 METs?
It is associated with increased perioperative risk.
cardiology surgery risk -
What is the formal definition of 1 MET?
It is defined as the energy used when resting or sitting still, equal to \(3.5 \text{ mL O}_2 / \text{kg} / \text{min}\).
cardiology metabolism -
Which six independent risk factors are included in the Revised Cardiac Risk Index (RCRI)?
The RCRI uses the following six independent predictors: - Ischemic heart disease - Congestive heart failure - Cerebrovascular disease - Diabetes mellitus treated with insulin - Serum creatinine \(> 2 \text{ mg/dL}\) - High-risk surgery (intraperitoneal, intrathoracic, or suprainguinal vascular)
cardiology risk surgery -
What is the Revised Cardiac Risk Index (RCRI) primarily used for?
To assess metabolic equivalents
To measure long-term mortality
To assign perioperative cardiac risk
To diagnose coronary artery disease
cardiology risk surgery -
Chronic hypertension affects autoregulation curves by causing a shift to the right and a narrowing of the plateau.
cardiology hypertension -
What are the common symptoms of unstable cardiac disease that require further evaluation?
- Dyspnea
- Chest pain
- Syncope
- CHF
- Decreased or poor exercise tolerance
cardiology symptoms -
What activities require an energy expenditure of 4 METs according to the estimation table?
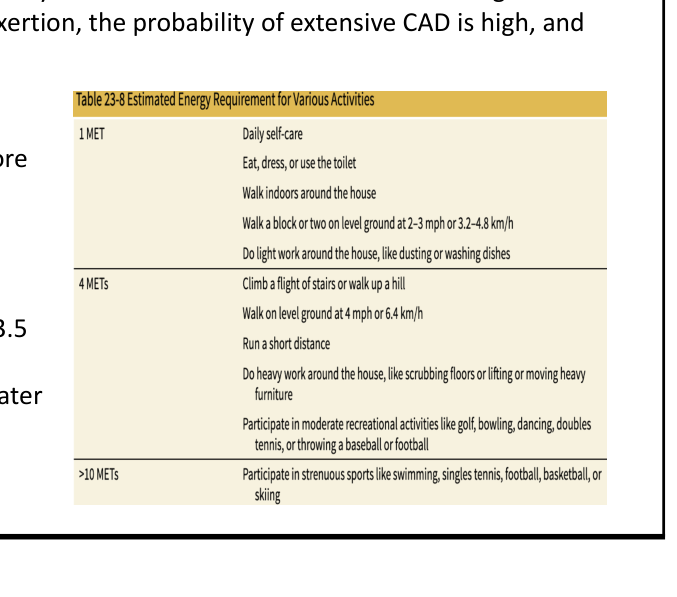
- Climbing a flight of stairs or walking up a hill
- Walking on level ground at 4 mph or 6.4 km/h
- Running a short distance
- Performing heavy work around the house (e.g., scrubbing floors or lifting heavy furniture)
- Participating in moderate recreational activities (e.g., golf, bowling, dancing, doubles tennis, throwing a baseball or football)
cardiology exercise -
What are the common symptoms of aortic stenosis (AS) or its disease progression?
- Angina
- Heart failure
- Syncope
cardiology aortic_stenosis -
What is the recommended interval for interrogating a patient's pacemaker?
Every 12 months
cardiology pacemaker -
What is the recommended interval for interrogating a patient's ICD?
Every 6 months
cardiology icd -
For patients with coronary artery stents, the delay for elective surgery should be 30 days for bare metal stents (BMS) and 365 days for drug-eluting stents (DES).
cardiology surgery -
What happens when a magnet is placed over an implanted cardioverter-defibrillator (ICD)?
It inhibits arrhythmia detection.
cardiology icd -
How many risk factors for CAD indicate an intermediate risk level for pre-operative testing?
0-1
2
3
4
cardiology risk_stratification -
What does a systolic murmur in the right second intercostal space indicate?
Aortic stenosis
cardiology aortic_stenosis -
According to AHA/ACC guidelines, preoperative echocardiography is required for moderate to severe valvular stenosis or regurgitation if no studies have been performed within 1 year or if there is worsening clinical status.
cardiology echocardiography -
What are the components of the STOP-Bang screening tool for obstructive sleep apnea?
- Snoring
- Tiredness
- Observed apnea
- High blood pressure
- Body mass index \(>35\) \(kg/m^2\)
- Age \(>50\) years
- Neck circumference \(>40\) cm
- Male gender
pulmonary apnea screening -
What is considered a high-risk score on the STOP-Bang screening tool?
4+
2+
0-3
5+
pulmonary apnea screening -
What happens to the body 24-48 hours after smoking cessation?
 - Decrease in nicotine levels
- Decrease in CV (cardiovascular) effects
- Decrease in carbon monoxide levelssmoking cessation pulmonary
-
What improvements occur 6-8 weeks after smoking cessation?
- Improvement in ciliary function
- Decrease in mucus productionsmoking cessation pulmonary -
Long-term benefits of smoking cessation include an addition of 6 to 8 years life expectancy and a reduced risk of lung cancer and heart disease.
smoking cessation health -
What are three common GI and hepatic conditions assessed in a preoperative history?
- GERD
- Gastroparesis
- Bowel obstruction
gi hepatic assessment -
What conditions are commonly noted in a renal assessment?
- Renal insufficiency
- Nephrotic syndrome
- Congenital malformations or absence
- Chronic renal disease
- ESRD
renal assessment -
What are three blood-related conditions relevant to a hematologic assessment?
- Anemia
- Thrombocytopenia
- Sickle Cell Disease
hematology assessment -
What is the normal measurement for the interincisor gap (IIG) during a preoperative airway exam?
Normal = 3 finger breadths or 5 cm
airway preoperative -
What is the normal thyromental distance (TMD) measurement?
Normal = 3 finger breadths or 6.5 cm
airway preoperative -
For the airway exam, c-spine extension is necessary to align the axes and visualize the vocal cords.
airway preoperative -
During an airway exam, the presence of ridges from the patient's teeth on the tongue is a sign that the tongue does not have much room.
airway preoperative -
What does the upper lip bite test signify during an airway exam?
Difficult intubation
Macroglossia
Reduced neck extension
Good mobility
airway preoperative -
Why is macroglossia problematic during intubation?
The tongue has to be displaced, and the larger the tongue, the more difficult it is to gain control of it.
airway preoperative -
The preoperative physical exam includes assessing vital signs, height/weight/BMI, general appearance, and breath sounds.
preoperative exam -
What structures are visible in a Mallampati Class 1 airway?
Full view of the soft palate, uvula, and tonsillar pillars.
airway mallampati -
Which Mallampati class is characterized by the soft palate and upper portion of the uvula being visible?
Class 2.
airway mallampati -
What is the visibility expectation for a Mallampati Class 3 airway?
Just the soft palate is visible; the uvula is not.
airway mallampati -
What structure is visible in a Mallampati Class 4 airway?
Only the hard palate.
airway mallampati -
Predictors of difficult intubation include an interincisor distance of less than 3 cm.
intubation airway -
A patient with a 'thick neck' is a predictor of difficult intubation if the circumference is greater than 17 in in males or 16 in in females.
intubation airway -
Which of the following is considered a predictor of difficult mask ventilation?
Long neck
Young age
Obesity
High range of motion of C-spine
ventilation airway -
Besides obesity and male gender, what is another anatomical predictor of difficult mask ventilation related to the face?
Beard.
ventilation airway -
According to the 2012 ASA Practice Advisory, how should pre-op tests be ordered for asymptomatic patients?
They should only be ordered after considering information obtained from the medical record, H&P, and the type or invasiveness of the planned procedure and anesthesia.
preoperative guidelines -
What are the clinical indications for ordering a preoperative CBC?
- Extremes of age
- Liver or kidney disease
- Anticoagulant use
- Bleeding/hematologic disorder
- Malignancy
- Type and invasiveness of procedure
preoperative cbc -
What factors should the decision to order T&S (Type and Screen) or T&C (Type and Crossmatch) be based on?
- Patient condition
- Baseline Hct
- Expected blood loss
blood surgery -
For preoperative blood conservation, strategies should be considered to minimize the use of allogeneic blood.
blood surgery -
How long prior to the date of surgery (DOS) should NSAIDs be held?
2-7 days prior to DOS.
medications surgery -
How long prior to the date of surgery (DOS) should Coumadin be held?
5 days prior to DOS.
medications surgery -
Which of the following medications should be continued before surgery?
GLP-1 Agonists
Statins
Diuretics
NSAIDs
medications surgery -
What is the recommended pre-operative hold time for St. John's Wort?
At least 5 days prior to the date of surgery.
medications surgery -
What is the recommended pre-operative hold time for Enbrel?
2 weeks prior to surgery.
medications surgery -
How should high-risk antiplatelet therapy be managed before surgery?
Hold clopidogrel and continue ASA.
medications surgery -
What is the upper limit for glucose control in Type 1 diabetic patients undergoing surgery?
Less than 200 mg/dL
diabetes surgery -
When should antibiotics be administered in relation to the incision?
Within 1 hour prior to incision
antibiotics surgery -
What is the recommended antibiotic strategy if a procedure is prolonged beyond two half-lives?
Redose the antibiotic
antibiotics surgery -
What dosage adjustment is required for morbidly obese patients receiving antibiotic prophylaxis?
Twice the dose of normal weight patients
antibiotics obesity -
Which antibiotics should be used for surgical prophylaxis in patients with a penicillin allergy?
Vancomycin or clindamycin
antibiotics allergy -
What criteria define Mendelson's syndrome?
Volume > 25 mL and pH < 2.5
aspiration pulmonary -
What is the most significant ranked risk factor for pulmonary aspiration?
Obesity
Emergency surgery
GERD
Opioid use
aspiration risk -
Routine pharmacologic prophylaxis for aspiration is not recommended in otherwise healthy patients with no risk factors undergoing elective procedures.
aspiration prevention -
What is the primary clinical benefit of administering Sodium Citrate prior to anesthesia?
It minimizes the risk of lung injury by increasing the pH of gastric fluid.
pharmacology anesthesia -
Why should Metoclopramide be avoided in patients with a suspected bowel obstruction?
Because it increases gastric motility, which could precipitate complications like bowel perforation.
pharmacology metoclopramide -
Which type of antacid is contraindicated for use due to the risk of serious pulmonary sequelae if aspirated?
Nonparticulate antacids (e.g., Sodium Citrate)
Histamine-2 receptor antagonists
Proton pump inhibitors
Particulate antacids (e.g., Tums, Rolaids)
pharmacology anesthesia -
How do Histamine-2 receptor antagonists affect gastric secretions?
They decrease gastric volume and acidity by blocking the ability of histamine to induce secretion of gastric fluid with a high \(H^+\) concentration.
pharmacology gastroenterology -
Among H2 receptor antagonists, Famotidine has the longest duration of action, typically lasting 10-12 hours.
pharmacology medication -
What is the primary mechanism of action for Proton Pump Inhibitors (PPIs)?
They suppress gastric acid secretion by binding to the proton pump of the parietal cells.
pharmacology medication -
List three primary goals of administering pre-operative medication.
- Decrease risk of aspiration
- Relief of anxiety
- Sedation
anesthesia pre-op -
Extreme caution should be used with pre-op sedation in patients with intracranial pathology, severe pulmonary disease, or hypovolemia.
safety anesthesia -
What is the primary action of Dexmedetomidine as an alpha-2 agonist?
It produces sedation and attenuates the sympathetic nervous system response to stimulation.
pharmacology anesthesia -
What is a characteristic side effect of opioid administration regarding gastrointestinal function?
Delayed gastric emptying.
pharmacology analgesics -
Which anticholinergic medication listed is known to be more potent than Atropine for antisialagogue effects?
Glycopyrrolate.
pharmacology anticholinergics -
Which drug is categorized as a Quaternary Amine anticholinergic that does not easily cross the blood-brain barrier?
Glycopyrrolate
Atropine
Midazolam
Scopolamine
pharmacology anticholinergics -
According to the table comparing anticholinergics, which agent has the strongest sedative and amnesic effects?
Scopolamine
pharmacology anticholinergics -
The most common benzodiazepine used in anesthetic practice is Midazolam, which is valued for its rapid onset and recovery.
pharmacology benzodiazepines -
Why is the routine use of anticholinergics considered uncommon?
Due to side effects such as CNS toxicity, tachycardia, pupil dilation, relaxation of the lower esophageal sphincter, inhibition of sweating, and thickened secretions.
pharmacology anticholinergics -
What are the five main risk factors for PONV in adults?
- Female sex
- Risk surgery
- Volatile anesthesia
- History of PONV or Motion Sickness
- Non-smoking
ponv anesthesia -
Which of the following is a recommended strategy to mitigate PONV?
Routine use of nitrous oxide
Avoidance of hydration
Increased use of volatile anesthetics
Use of regional anesthesia
ponv anesthesia -
For patients with 1-2 risk factors for PONV, give 2 agents; for patients with > 2 risk factors, give 3-4 agents.
ponv stratification -
What is the recommended newer stress-dose steroid treatment for the first day of surgery?
100 mg hydrocortisone IV followed by 50 mg IV q8 hours.
steroids surgery -
Potential adverse effects of stress-dose steroid treatment include: - Hypertension - Hyperglycemia - Increased risk of infection - Delayed wound healing - Electrolyte disturbance/Fluid retention
steroids side-effects -
What is the typical prophylactic combination used against allergic reactions?
H1 (Benadryl) + H2 (Zantac/Pepcid) + Steroid (hydrocortisone)
allergies prophylaxis -
Pretreatment with a combination of H1 and H2 antagonists is more effective than H1 antagonists alone.
allergies prophylaxis -
What are the five major goals of general anesthesia?
- Amnesia
- Analgesia
- Loss of consciousness
- Muscle relaxation/immobility
- Suppression of the ANS
anesthesia goals -
During which stage of Guedel's anesthesia is 'Excitement' observed?
Stage 3
Stage 2
Stage 4
Stage 1
anesthesia stages -
What are the pupil characteristics in Guedel's Stage 4 anesthesia?
Dilated and unreactive
anesthesia stages -
In Guedel's classification, Stage 1 is also known as the Induction Period or Analgesia.
anesthesia stages -
What is the primary characteristic of Guedel's Stage 4 anesthesia?
Anesthetic Crisis (breathing stops to death)
anesthesia stages -
What occurs during Plane 4 of Guedel's Stage 3 (Surgical Anesthesia)?
Complete intercostal paralysis to diaphragmatic paralysis, apnea, and loss of respiratory effort.
anesthesia stages -
In Guedel's Stage 3, Plane 3, what happens to the light reflex?
It is abolished.
anesthesia stages -
What are the physiological signs associated with Guedel's Stage 2 (Excitement)?
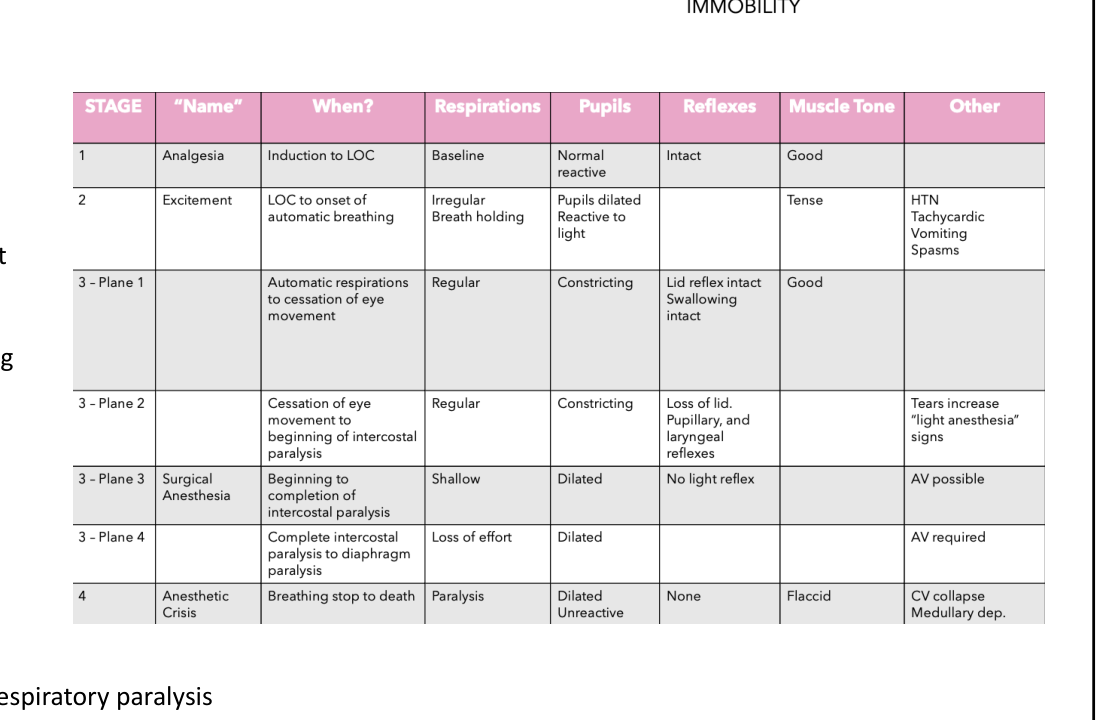 - Irregular respiration
- Breath holding
- Pupillary dilationanesthesia stages
-
What mnemonic is used for pre-induction anesthesia tasks?
MS. MAIDS
anesthesia mnemonic -
What does each letter in the 'MS. MAIDS' mnemonic stand for in the context of pre-induction anesthesia tasks?
- M: Machine
- S: Suction
- M: Monitors
- A: Airway
- I: IV access
- D: Drugs
- S: Special
anesthesia mnemonic -
The components of the MS. MAIDS mnemonic are: - Machine - Suction - Monitors - Airway - IV access - Drugs - Special
anesthesia mnemonic -
What is the primary goal of administering pre-induction medications?
Blunt hemodynamic (HD) response to direct laryngoscopy (DL).
anesthesia medication -
What are two ways to achieve preoxygenation for anesthesia induction?
- Tidal breathing for 3 minutes via oxygen facemask
- 4 vital capacity (VC) breaths over 30 seconds
- 8 vital capacity (VC) breaths over 60 seconds
anesthesia preoxygenation -
How is loss of consciousness (LOC) assessed during pre-induction?
By checking the lash reflex, then taping the eyes.
anesthesia assessment -
List four methods to verify endotracheal tube (ETT) placement.
- Visualization of ETT through vocal cords (VC)
- Fogging
- Equal bilateral (BL) chest rise
- Bilateral breath sounds (BBS)
- Positive end-tidal CO2 ((+) ETCO2)
- No breath sounds over the stomach
anesthesia intubation -
What is a standard component of pre-induction documentation?
Discharge summary
Informed consent obtained
Post-operative pain scale
Patient insurance verification
anesthesia documentation -
What is the primary goal of Rapid Sequence Induction (RSI)?
To minimize aspiration risk.
rsi anesthesia -
What is the clinical endpoint for preoxygenation in RSI?
\(ETO_2 > 90\%\)
rsi preoxygenation -
When should cricoid pressure be applied and released during RSI?
- Applied: Just prior to induction
- Released: After placement of the endotracheal tube (ETT) is confirmed
rsi airway -
The Cormack-Lehane Grade 1 view indicates a complete or nearly complete view of the glottic opening.
laryngoscopy cormack-lehane -
Which of the following is a contraindication to the use of succinylcholine (SCh) for RSI?
Full stomach
Pregnancy
Malignant hyperthermia (MH) susceptibility
GERD
rsi contraindications -
Based on the Cormack-Lehane scale, what is visible in a Grade 3 view?
Epiglottis only.
laryngoscopy cormack-lehane -
What is the definition of fasciculations seen with succinylcholine induction?
SCh-induced involuntary muscle contractions.
rsi pharmacology -
Using the provided Cormack-Lehane grading scale illustration, which grade displays only the soft palate?
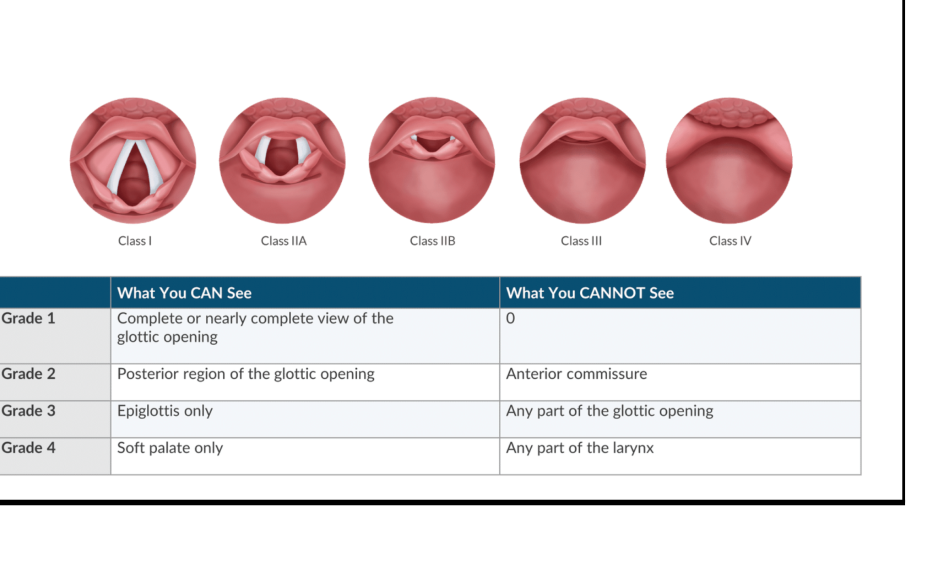 Grade 4laryngoscopy cormack-lehane
-
What are some clinical indications for using Total Intravenous Anesthesia (TIVA)?
- Procedures requiring neuro monitoring
- Severe Postoperative Nausea and Vomiting (PONV)
- Airway procedures where agents cannot be reliably delivered
- Malignant Hyperthermia (MH) susceptible patients
anesthesia tiva -
What categories of drugs are commonly used in Balanced Anesthesia?
- INH agents
- IV anesthetics (propofol, ketamine, precedex)
- Narcotics (short-acting and long-acting)
- Benzodiazepines
- NMBDs
- Vasoactives (beta blockers, pressors)
anesthesia pharmacology -
What are the minimum recording intervals for vital signs (BP, HR, RR) during maintenance of anesthesia?
Every 5 minutes
monitoring anesthesia -
What specific patient safety documentation must occur every 30 minutes regarding body position?
Documentation of the assessment of position changes.
monitoring safety -
Intraoperative documentation of critical events (such as cardiac arrest, anaphylactic reaction, difficult airway, or EKG changes) usually requires a separate note in the patient's chart.
documentation anesthesia -
Which of the following monitoring parameters is required to be documented at a minimum interval of every 15 minutes?
BP, HR, RR
Rate, Vt, PIP, PEEP
O2, N2O, or air
SaO2, FiO2, ETCO2
monitoring anesthesia -
Regarding the surgical time-out, what items are included in the verification checklist?
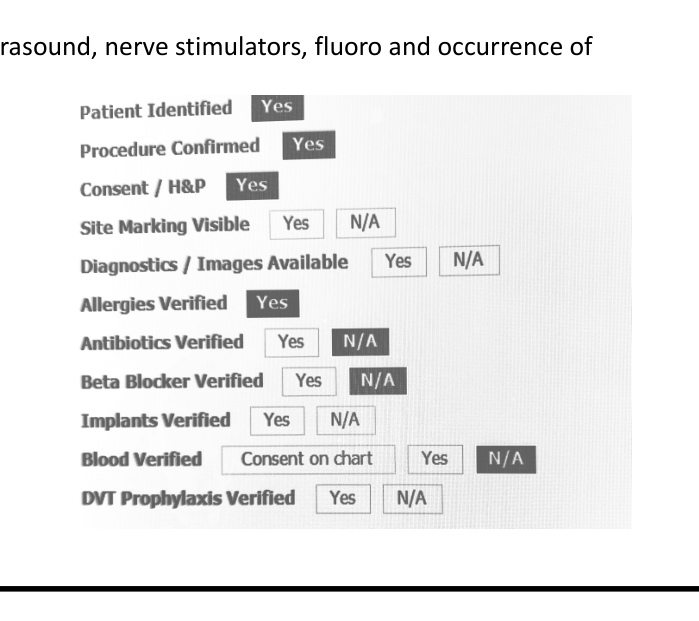 - Patient identified
- Procedure confirmed
- Consent / H&P
- Site marking visible
- Diagnostics / images available
- Allergies verified
- Antibiotics verified
- Beta blocker verified
- Implants verified
- Blood verified
- DVT prophylaxis verifiedsafety surgery
-
What clinical signs are associated with 'Light Anesthesia' when Neuromuscular Blocking Drugs (NMBD) are present?
- Tachycardia
- Hypertension
- Sweating
- \(BIS > 60\)
anesthesia depth -
What are the cardiovascular effects of excessive 'deep anesthesia'?
- Bradycardia
- Hypotension
anesthesia depth -
Which of the following is considered a patient group less suited for deep extubation?
Obese patients
Patients with no history of aspiration
Patients with low BMI
Patients with high tidal volume
anesthesia extubation -
The requirements for awake extubation include: - Breathing frequency < 30 breaths/min - Maximum inspiratory pressure < -20 cm \(H_2O\) - Vital capacity > 15 mL/kg - Tidal volume > 6 mL/kg
anesthesia extubation -
According to the comparative table, what is a primary 'Con' of awake extubation?
Increased coughing risk.
 anesthesia extubation
-
What does a deep extubation attempt to avoid?
Coughing and bucking.
anesthesia extubation -
For deep extubation, the ETT is removed prior to wake up and prior to return of upper airway reflexes.
anesthesia extubation -
List the three items that must be verbally confirmed by the surgeon, anesthesia professional, and nurse before skin incision.
- Patient
- Site
- Procedure
safety surgery -
What is the Aldrete score required to meet discharge criteria?
9-10
anesthesia post-op -
According to the Aldrete Scoring system, what oxygen saturation value indicates a score of 2?
\(SpO_2 > 92\%\) on RA
anesthesia monitoring -
What blood pressure criteria is needed for a score of 2 in the circulation category of the Aldrete score?
BP within \(20\text{ mmHg}\) of preanesthetic value (min SBP = \(90\text{ mmHg}\))
anesthesia monitoring -
For the consciousness category of the Aldrete score, a patient who is fully awake receives a score of 2, while a patient who is arousable to voice receives a score of 1.
anesthesia monitoring -
What is the score for a patient who is apneic in the respiration category of the Aldrete scoring system?
0
3
2
1
anesthesia monitoring -
When is the anesthesia end time documented?
When care is transferred to PACU/ICU
anesthesia documentation -
In the context of follow-up post-op notes, how often should inpatients be seen after discharge from PACU?
At least once within 48 hours
anesthesia post-op -
What elements should be included in a PACU handoff?
- Patient name and age
- Allergies and medications
- Medical history
- Procedure
- Anesthetic technique and medications given
- Labs
- Fluids given and output
- Immediate post-op concerns and recommendations
anesthesia handoff -
What is the leading cause of anesthesia-related malpractice claims?
Death (30%)
anesthesia malpractice -
Name three causes of severe hypoxemia in the context of anesthesia.
- Inadequate ventilation
- Severe lung disease
- Delivery of inappropriately low \(FiO_2\)
hypoxemia anesthesia -
What are three common causes of reduced cardiac output leading to cerebral ischemia under anesthesia?
- Cardiac failure
- Cardiac arrest
- Severe bradycardia
ischemia anesthesia -
The psychological consequences of anesthesia awareness can include sleep disturbances, work & social impairment, and PTSD.
anesthesia psychology -
List four risk factors associated with anesthesia awareness.
- Cardiac surgery
- OB/GYN surgery
- Trauma
- Difficult airway
anesthesia risks -
What are three pharmacological or monitoring strategies used to mitigate the risk of anesthesia awareness?
- Benzodiazepines
- Scopolamine
- Ketamine
anesthesia mitigation -
What is the most common reported eye injury related to anesthesia?
Corneal abrasion.
anesthesia complications -
What are three causes of corneal abrasion during anesthesia?
- Drying of eyes
- Decreased tear production from general anesthesia
- Chemical injury from prep solutions
anesthesia corneal injury -
Which surgical positions or procedures are risk factors for ischemic optic neuropathy?
- Prone position
- Trendelenburg position
- Spine surgery
anesthesia neuropathy -
What are the causes of central retinal artery occlusion?
- Direct pressure to the globe (from a face mask)
- Increased intraocular pressure (IOP)
- Increased central venous pressure (CVP)
- Poor venous drainage
- Nitrous oxide (\(N_2O\)) use with a gas bubble
anesthesia retinal occlusion -
Mendelson's syndrome is a type of chemical pneumonitis caused by the aspiration of gastric contents with a pH of less than 2.5 and a volume of 0.3 ml/kg or greater.
anesthesia mendelson aspiration -
What are the prevention strategies for Mendelson's syndrome?
- Strict adherence to NPO guidelines
- Pharmacological agents (Non-particulate Antacids, H2 antagonists, PPIs, Gastrokinetics)
- Regional anesthesia vs general endotracheal anesthesia (GETA)
- Rapid sequence induction (RSI) with cricoid pressure
- Awake intubation for difficult airways
- Awake extubation with airway reflexes intact
anesthesia prevention mendelson -
What is the primary genetic defect associated with malignant hyperthermia?
A defect in the genes coding for ryanodine receptors (RYR1).
pathophysiology genetics -
What classes of agents are known to trigger malignant hyperthermia?
- Inhaled anesthetics (halothane, sevo, des, iso)
- Depolarizing muscle relaxants (succinylcholine)
anesthesia pharmacology -
What are the earliest clinical signs of malignant hyperthermia?
- Rise in \(ETCO_2\)
- Tachycardia
- Tachypnea
clinical symptoms -
Malignant hyperthermia is inherited in an autosomal dominant pattern, meaning that one defective gene is needed for the disease to manifest.
genetics inheritance -
What is a major consequence of sustained hypermetabolism in malignant hyperthermia related to muscle cell breakdown?
Decrease in core temperature
Decreased \(ETCO_2\) levels
Release of myoglobin, \(K^+\), and CK
Improved muscle oxygenation
pathophysiology complications -
What physiological event occurs when triggering agents react with RYR1 receptors, initiating a hypermetabolic state?
Uncontrolled \(Ca^{2+}\) release from the sarcoplasmic reticulum into the myoplasm.
pathophysiology mechanism -
What condition occurs if the body temperature reaches or exceeds \(41^{\circ} C\) during a malignant hyperthermia crisis?
Death usually due to DIC (disseminated intravascular coagulation).
pathophysiology complications -
What are two specific musculoskeletal complications resulting from rhabdomyolysis in malignant hyperthermia?
- Muscular weakness
- Compartment syndrome
complications musculoskeletal -
What is the mechanism of action of dantrolene?
It is a specific RYR1 receptor antagonist that prevents \(Ca^{2+}\) release from the SR and RYR1/DHP receptor coupling.
pharmacology dantrolene -
What is the initial recommended dose of dantrolene for the treatment of malignant hyperthermia?
\(2.5\text{ mg/kg}\)
pharmacology dantrolene -
Which of the following is true regarding the new formulation of dantrolene (Ryanodex) compared to the original (Dantrium)?
It is 150 times more concentrated.
It takes 860 seconds to mix.
It requires 60 ml of sterile water.
It is less expensive than the original formulation.
pharmacology dantrolene -
Delays in treatment are associated with high rates of complications and death in MH-related cases.
mh safety -
What are the three main categories of causes for Neuroleptic Malignant Syndrome?
- Antipsychotic (neuroleptic) drugs
- Abrupt withdrawal of dopaminergic agonists in patients with Parkinson's
- Dopamine antagonists
neurology nms -
How do NMS and MH compare regarding inheritance and onset time?
NMS is not inherited and takes 24-72 hours or several weeks to develop. MH is inherited and has early onset within minutes.
nms mh comparison -
Which drug is used as a dopaminergic agonist for the treatment of Neuroleptic Malignant Syndrome?
Bromocriptine
neurology nms treatment -
Which of the following is a symptom of Neuroleptic Malignant Syndrome?
Bradycardia
Muscle rigidity
Hypothermia
Increased dopamine activity
neurology nms -
What three myopathic disorders are associated with susceptibility to malignant hyperthermia?
- King Denborough Syndrome
- Central Core Disease
- Multi-Minicore Disease
medicine anesthesia -
What percentage of patients with masseter muscle rigidity (MMR) test positive for malignant hyperthermia susceptibility (MHS)?
50%
medicine anesthesia -
In the management of masseter muscle rigidity (MMR) during emergent surgery, prophylactic dantrolene is not recommended.
medicine anesthesia -
What is the Gold Standard test for malignant hyperthermia susceptibility?
Caffeine-Halothane Contracture Test (CHCT)
medicine diagnosis -
What are the sensitivity and specificity of the Caffeine-Halothane Contracture Test (CHCT)?
- Sensitivity: 100%
- Specificity: 78-94%
medicine diagnosis -
Which of these is a known disadvantage of genetic testing for malignant hyperthermia susceptibility?
It is always less accurate than the CHCT.
A negative test does not rule out susceptibility.
It is more expensive than the CHCT.
It requires a muscle biopsy.
medicine genetics -
What is the initial dose and repetition protocol for Dantrolene in the management of an MH crisis?
Administer 2.5 mg/kg, repeating until symptoms are reversed up to 10 mg/kg.
emergency pharmacology mh -
Which class of drugs is contraindicated in the management of MH-related dysrhythmias after the administration of Dantrolene?
Calcium Channel Blockers.
emergency pharmacology mh -
What are the measures to prevent myoglobinuria-induced renal failure in the context of an MH crisis?
- Initiate diuresis
- Maintain urine output > 1 mL/kg/hr
- Administer Lasix
- Alkalinize urine
- Administration of mannitol (as part of Dantrolene protocol)
emergency mh renal -
The earliest clinical sign of Malignant Hyperthermia (MH) is increased ETCO2.
monitoring mh -
What is the recommended cleaning procedure for an anesthesia machine before a case involving an MH-susceptible patient?
- Ideally schedule as the first case of the day
- Remove vaporizers and succinylcholine from the room
- Change CO2 absorbent and disposable components
- Place charcoal filters on inspiratory and expiratory limbs of the circuit
- Flush system at flows of 10L/min for at least 20 minutes
pre-op mh anesthesia -
Which medications may be used to treat dysrhythmias during an MH crisis?
Procainamide and lidocaine
Verapamil
Diltiazem
Amlodipine
emergency pharmacology -
What is the primary risk associated with arm abduction exceeding 90 degrees in a surgical patient?
Brachial plexus injury caused by the humeral head pushing into the axilla.
anesthesia positioning safety -
During the supine position, arm abduction must be limited to less than 90 degrees to prevent brachial plexus injury.
anesthesia positioning -
Which compensatory mechanism is attenuated by neuraxial anesthesia?
Sympathectomy
anesthesia physiology -
How does neck flexion affect the ETT position?
It increases the risk of endobronchial intubation.
anesthesia intubation -
What sex is specifically associated with an increased risk of ulnar neuropathy during surgery?
Male
anesthesia risk -
What is the effect of increased intrathoracic pressure on venous return (VR)?
Decreased venous return ($ o ext{VR}$)
anesthesia physiology -
Which position is identified as the most common surgical position?
Prone
Lithotomy
Lateral decubitus
Supine
anesthesia positioning -
What is the recommended intervention to mitigate back pain caused by the loss of normal lumbar lordotic curvature in the supine position?
Use a pillow under the knees.
anesthesia positioning -
What is the primary cardiovascular effect of the Trendelenburg position?
Increased venous return and central venous pressure, leading to increased cardiac output.
cardiology trendelenburg -
What happens to functional residual capacity (FRC) in the Trendelenburg position?
FRC decreases due to abdominal contents being displaced toward the diaphragm.
respiratory trendelenburg -
What are the common potential complications associated with the Trendelenburg position?
- Increased airway pressure
- V/Q mismatch
- Edema of face, eyes, and airway
- Aspiration
- Sliding
- Brachial plexus injury from shoulder braces
- Visual disturbances
- Masking signs of hypovolemia
complications trendelenburg -
How does the Reverse Trendelenburg position affect cardiovascular parameters?
It decreases venous return, preload, cardiac output, and arterial blood pressure.
cardiology reverse-trendelenburg -
The Reverse Trendelenburg position improves exposure for abdominal procedures and typically causes a decrease in cerebral perfusion.
surgery reverse-trendelenburg -
What is the effect of the lithotomy position on pulmonary function?
- Cephalad shift of diaphragm
- Decreased lung compliance
- Decreased FRC
- Decreased tidal volume (Vt)
- High peak airway pressures
- V/Q mismatching
respiratory lithotomy -
What characterizes the 'Standard' lithotomy position?
Hips flexed at 90 degrees, knees bent with lower legs parallel to floor
Hips flexed at 30-45 degrees
Hips flexed at 90 degrees or more with greater knee extension
Hips flexed at 180 degrees
positioning lithotomy -
What is the effect of obesity on the pulmonary complications of the lithotomy position?
Obesity and Trendelenburg exacerbate these effects.
respiratory lithotomy obesity -
Which nerve is the most commonly injured in the lithotomy position?
Common peroneal nerve
anesthesia complications lithotomy -
Where should an axillary roll be placed in a patient in the lateral decubitus position?
Just caudal to the axilla, not in the axilla itself.
positioning lateral-decubitus -
What is the primary purpose of placing an axillary roll in the lateral decubitus position?
To prevent compression injury to the dependent brachial plexus and dependent axillary vascular structures.
positioning lateral-decubitus -
In the lateral decubitus position, which lung is favored by perfusion?
The dependent lung.
physiology lateral-decubitus -
In the lateral decubitus position, which lung is favored by ventilation in an anesthetized patient?
The non-dependent lung.
physiology lateral-decubitus -
Induction of anesthesia causes decreased FRC.
physiology anesthesia -
Lateral decubitus position complications include: - impaired venous return - brachial plexus injury - pressure injuries - neck pain
complications lateral-decubitus -
Which nerve injury can be caused by the shoulder rolling forward onto the dependent arm in the lateral decubitus position?
Femoral nerve
Obturator nerve
Suprascapular nerve
Common peroneal nerve
complications lateral-decubitus -
What happens to venous return when the inferior vena cava is compressed in the prone position?
It becomes impaired.
prone physiology -
What effect does the prone position have on pulmonary compliance in obese patients?
It is improved, particularly when the abdomen is hanging freely.
prone respiratory -
List three potential ocular complications of the prone position.
- Ischemic optic neuropathy
- Central retinal artery occlusion
- Conjunctival edema
prone complications -
When the head is rotated to the side for more than 3 hours in the prone position, there is a risk of cervical neuropathy.
prone complications -
When a patient is in the sitting position, where should arterial blood pressure be measured?
At the level of the tragus.
sitting monitoring -
What happens to lung volumes and functional residual capacity (FRC) in the sitting position?
They increase.
sitting respiratory -
What is a potential risk of excessive neck flexion in the sitting position?
Edema of the face, tongue, and neck due to impaired venous drainage.
sitting complications -
What serious complication can occur in the sitting position due to stretching of the spinal cord?
Mid-cervical tetraplegia.
sitting complications -
Which of the following is an effect of the sitting position on cerebral blood flow?
No change
Increased
Decreased
Unpredictable
sitting physiology -
What is the consequence of stretching a nerve to 5% greater than its normal resting length?
It leads to ischemia due to the kinking of the arterioles and venules.
neurology injury -
Which peripheral nerve is the most frequently injured?
Ulnar nerve
neurology ulnar -
What forearm position helps avoid external compression of the ulnar nerve in the cubital tunnel?
Forearm supination
neurology ulnar -
What motor manifestation is characteristic of an ulnar nerve injury?
Loss of abduction, extension, or opposition of 4th and 5th fingers (claw hand).
neurology ulnar -
Radial nerve injury results in loss of dorsiflexion, a condition known as wrist drop.
neurology radial -
What clinical deformity is associated with a median nerve injury when a patient attempts to make a fist?
Hand of benediction or ape hand.
neurology median -
According to the mnemonic 'DR CUMA', which nerve injury is associated with 'Claw Hand'?
Radial nerve
Femoral nerve
Ulnar nerve
Median nerve
neurology mnemonic -
What are two clinical manifestations of an Ulnar nerve injury?
- Claw Hand
neurology injury -
What physical actions increase the risk of brachial plexus stretching injuries?
- Arm abduction > 90°
- Excessive lateral rotation of the head
brachial injury -
Common peroneal injury is the most frequently damaged nerve in the lower extremity.
peroneal injury -
What is a common mechanism for peroneal nerve compression damage?
When the lateral aspect of the leg leans against a stirrup bar or candy canes, typically in the lithotomy position.
peroneal injury -
What is the primary manifestation of an obturator nerve injury?
Inability to ADDUCT the leg.
obturator injury -
What is the cause of pudendal nerve injury during surgery?
Pressure from the perineal post of an orthopedic fracture table.
pudendal injury -
What site is most susceptible to external pressure for a saphenous nerve injury?
The medial aspect of the leg.
saphenous injury -
Which of the following is a manifestation of radial nerve injury?
Foot drop
Claw Hand
Inability to flex forearm
Wrist drop
neurology radial -
What preventative measures should be taken to avoid venous air embolism during surgery?
Maintain adequate venous pressure and ligate 'open' veins.
surgery complications -
Which surgical positions are associated with the risk of alopecia?
- Supine
- Lithotomy
- Trendelenburg
surgery complications -
How can corneal abrasion be prevented during surgery?
Taping or lubricating the eye.
surgery complications -
What is the recommended prevention for brachial plexus nerve palsy during surgery?
Avoid stretching or direct compression at the neck, shoulder, or axilla.
surgery nerve complications -
What surgical positions increase the risk of common peroneal nerve palsy?
- Lithotomy
- Lateral decubitus
surgery nerve complications -
What prevention strategy is recommended for radial nerve palsy during surgery?
Avoid compression of the lateral humerus.
surgery nerve complications -
What prevention strategy is recommended for ulnar nerve palsy during surgery?
Avoid sustained pressure on the ulnar groove.
surgery nerve complications -
What is the recommended prevention for retinal ischemia during surgery?
Avoid pressure on the globe.
surgery complications -
What is the recommended prevention for skin necrosis during surgery?
Avoid sustained pressure over bony prominences.
surgery complications